Related Experiment Video
Updated: May 9, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
[Individualized treatment of the atlantoaxial dislocation in craniovertebral junction abnormalities]
Yi-heng Yin1, Xin-guang Yu, Ding-biao Zhou
1Department of Neurosurgery, People's Liberation Army General Hospital, Beijing 100853, China.

Objectives:
To analyze the clinical characteristics of the atlantoaxial dislocation (AAD) in craniovertebral junction (CVJ) abnormalities and to study the setup of its surgery strategy.
Methods:
From April 2009 to November 2011, 56 patients of AAD and CVJ abnormalities including 22 male and 34 female patients who had received surgery were analyzed. There were 2 cases of reducible AAD and 54 cases of irreducible AAD. The age of the patients ranged from 9 to 56 years (mean 34 years). Among them, 14 cases achieved reduction/partial reduction via direct posterior fixation, 41 cases had transoral anterior deconpression and occipito-cervical/C₁-C₂ fusion and 1 case had the posterior odontoidectomy and spinal fusion.
Results:
Fifty-three cases had a follow-up between 6 months and 36 months (mean 20 months) and 3 cases lost follow-up (had improvement at discharge). Seven cases had complications as follows: 1 case had irreversible spinal cord injury and muscle weakness of extremities, 2 cases had cerebrospinal leak, 2 cases had pulmonary infection, 1 case had local granuloma hyperplasia and 1 case had delayed healing of the incision. The later 6 cases all got recovery after reasonable treatments. The grades of Nurick at last follow-up were as follows: 6 cases (11.3%) improved by 3 grades, 30 cases (56.6%) improved by 2 grades, 13 cases (24.5%) improved by 1 grade, 3 cases (5.7%) without change, 1 case (1.9%) get worse.
Conclusions:
Reducible AAD could achieve direct reduction and fixation via posterior pathways. Irreducible AAD needs individualized treatment. To choose the direct reduction and fixation or transoral odontoidectomy and posterior fixation and fusion should consider the pathogenetic condition, the image data and personal clinical experience.
Related Concept Videos
 01:28
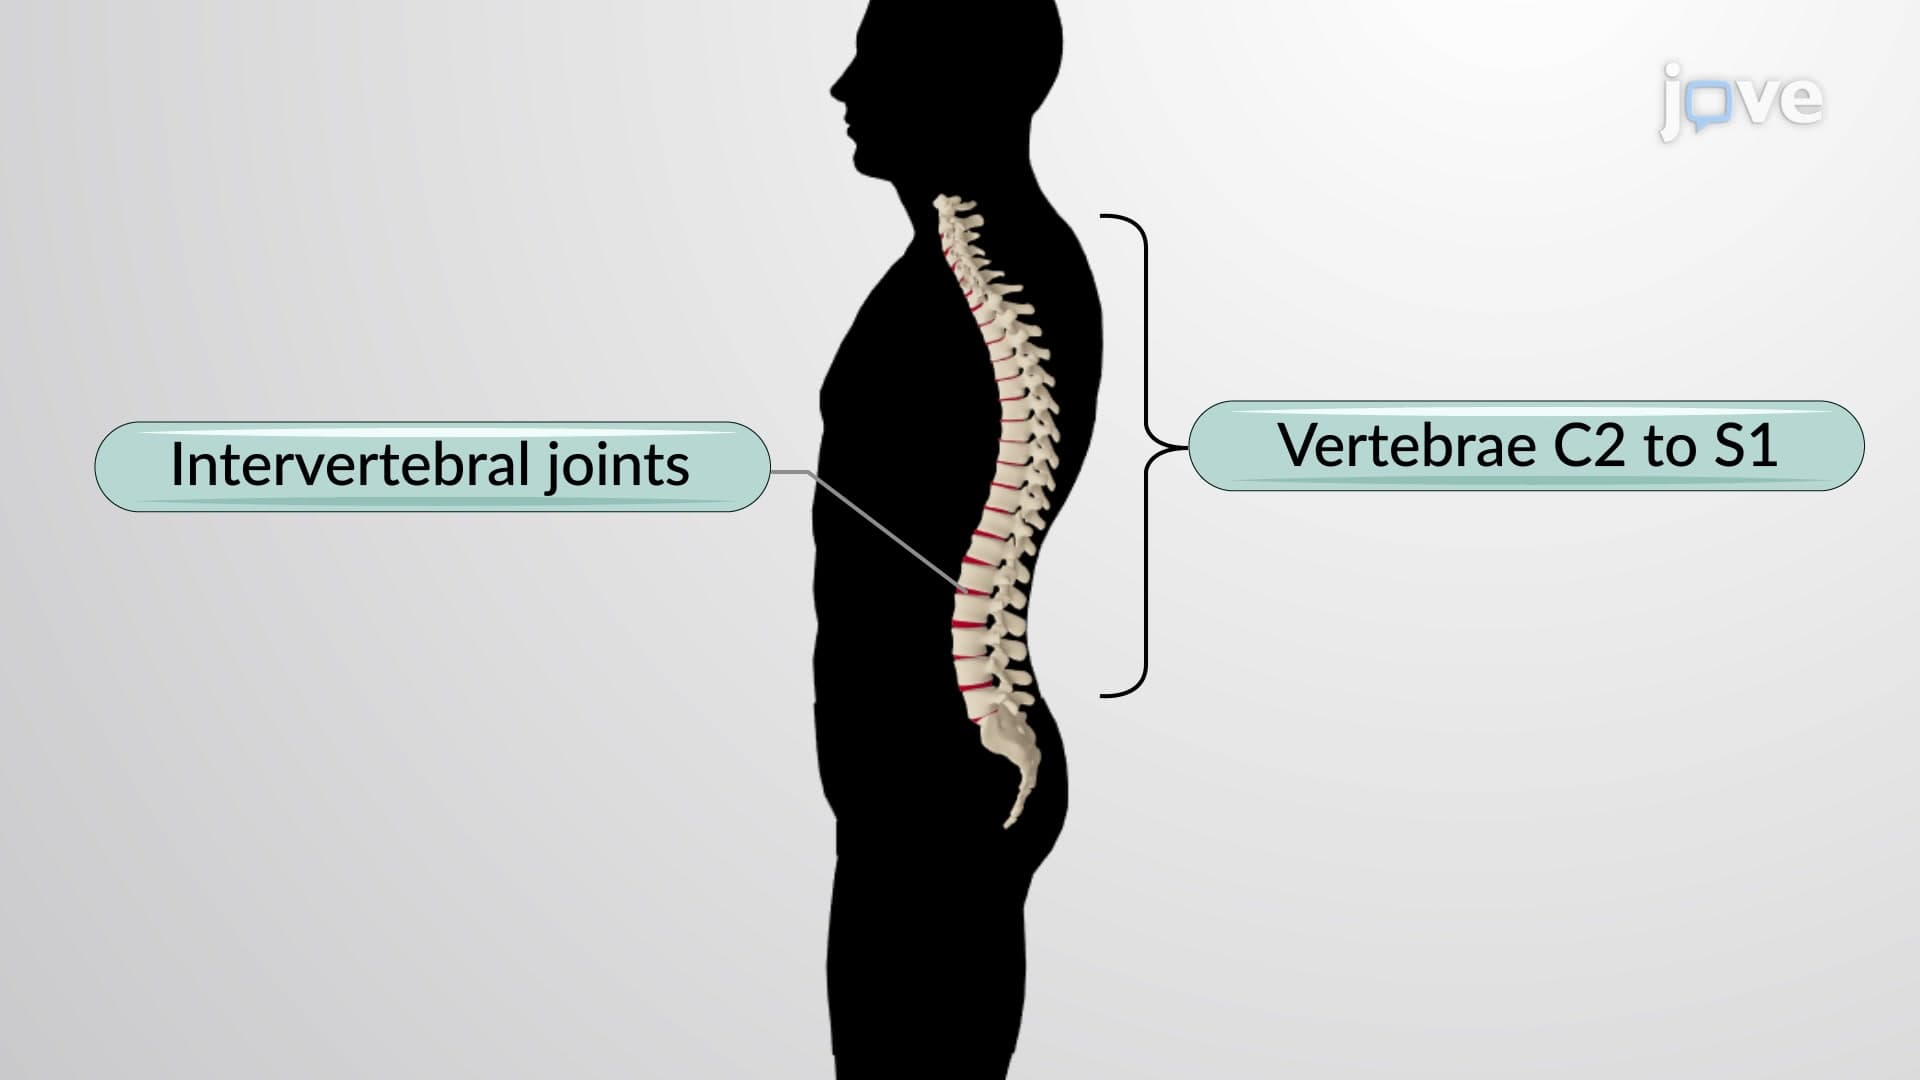
Articulations of the Vertebral Column
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:29
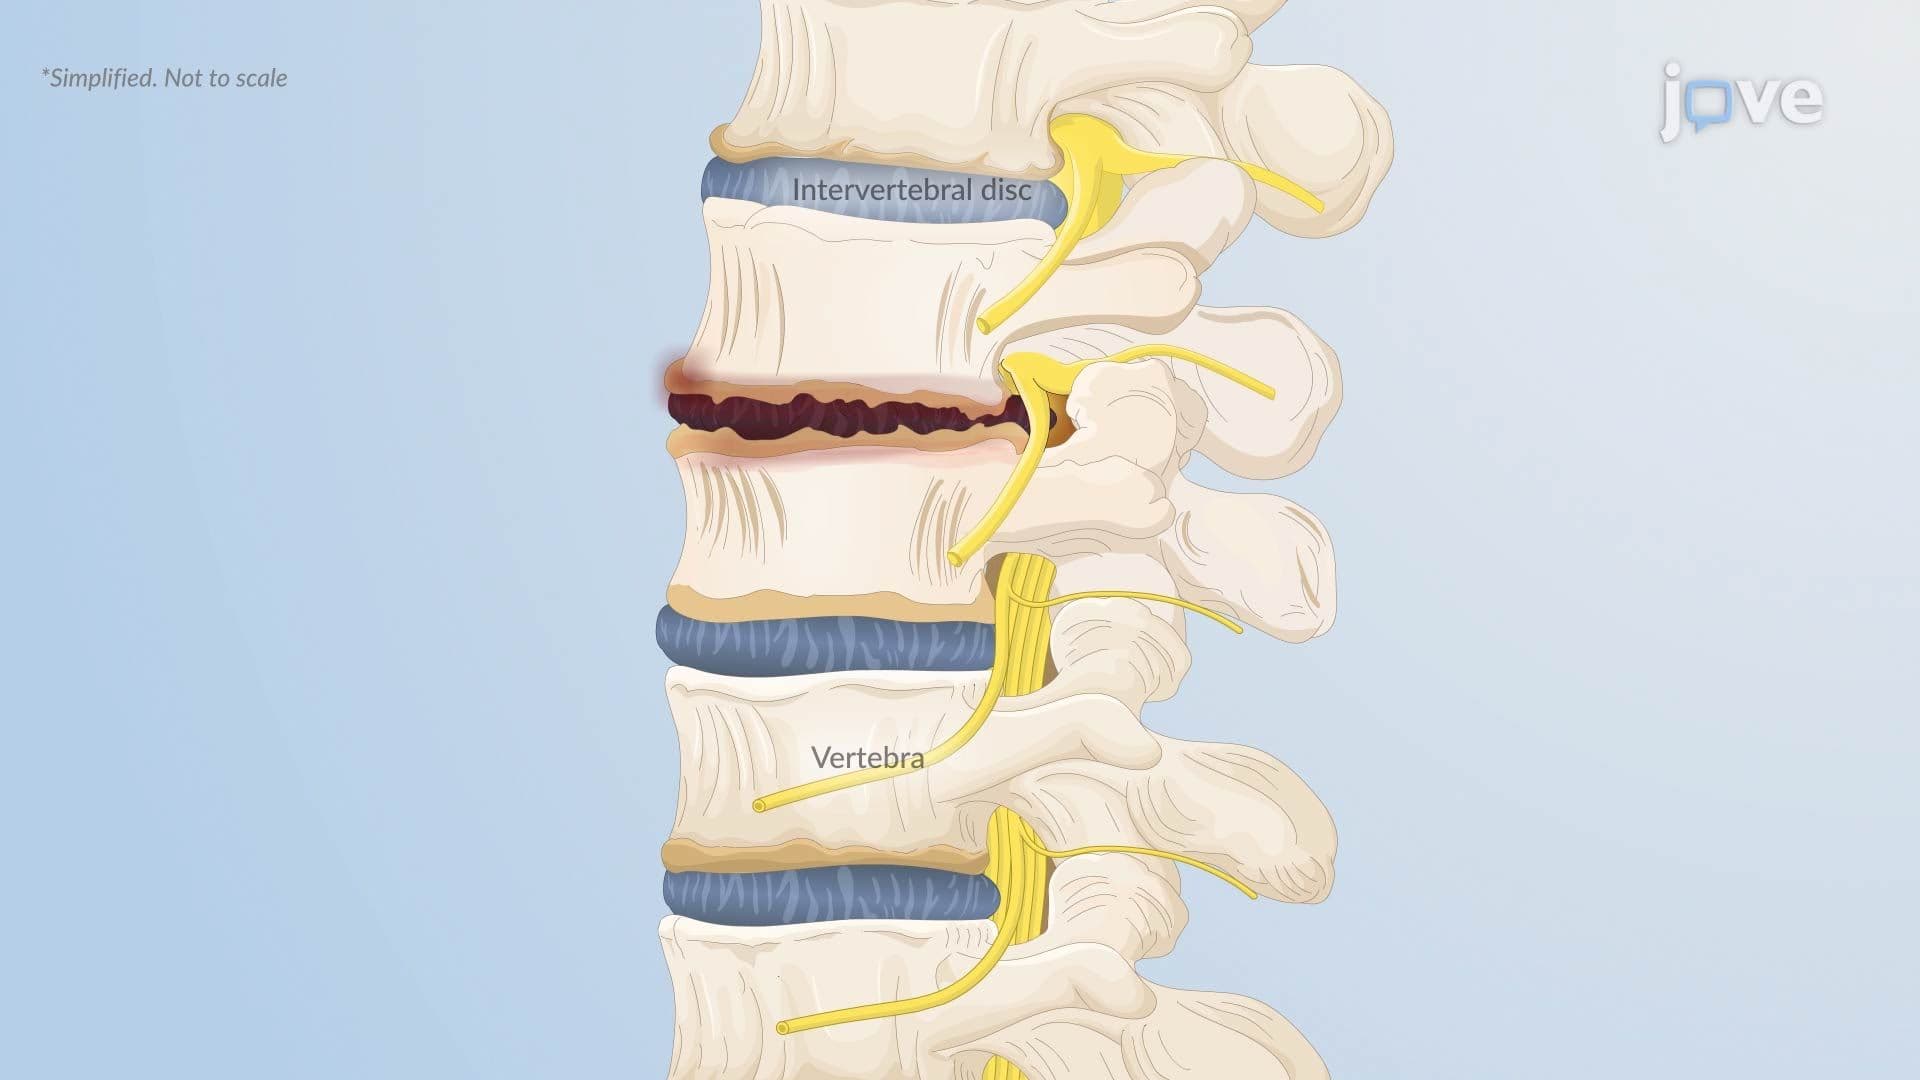
Herniated Intervertebral Disc l: Introduction
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...