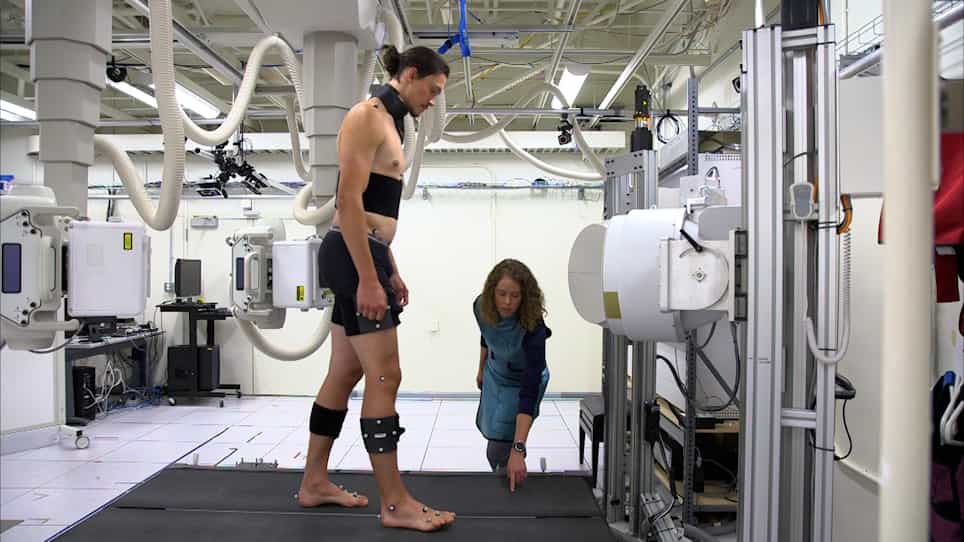
Related Experiment Video
Updated: May 9, 2026

The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
Bony impingement depends on the bone morphology of the hip after total hip arthroplasty
Takeshi Shoji1, Yuji Yasunaga, Takuma Yamasaki
1Department of Orthopaedic Surgery, Graduate School of Biomedical Sciences, Hiroshima University, 1-2-3 Kasumi, Minami-ku, Hiroshima, 734-8551, Japan, readymade_jpn@yahoo.co.jp.

Insights
Hip bone morphology significantly impacts range of motion (ROM) after total hip arthroplasty (THA). Larger bone anatomy in patients may lead to bony impingement, reducing flexion and internal rotation ROM.
Area of Science:
- Orthopedic Surgery
- Biomedical Engineering
- Radiology
Background:
- Total hip arthroplasty (THA) aims to restore hip function.
- Understanding factors influencing post-operative range of motion (ROM) is crucial for patient outcomes.
- Pre-operative bone morphology may play a role in limiting ROM after THA.
Purpose of the Study:
- To investigate the relationship between hip bone morphology and ROM after THA.
- To determine if specific anatomical parameters correlate with restricted flexion and rotation.
Main Methods:
- Utilized CT data from 63 patients who underwent THA.
- Calculated ROM (flexion, internal/external rotation) using 3D dynamic analysis software.
- Measured femur (GTa length) and pelvis (AIIS length) parameters to assess bone anatomy.
Main Results:
- A significant inverse relationship was found between GTa/AIIS length and ROM (flexion, internal rotation).
- Larger bone anatomy correlated with decreased flexion and internal rotation.
- Anterior intertrochanteric impingement on the AIIS was observed in patients with larger bone structures.
Conclusions:
- Hip bone morphology substantially influences ROM, particularly flexion and internal rotation, in THA patients.
- Patients with larger bone anatomy are at higher risk for bony impingement.
- Consideration of bony impingement is essential during THA planning for patients with large bone morphology.
Purpose:
The purpose of this study was to evaluate whether the bone morphology of the hip affects the range of motion (ROM) in total hip arthroplasty (THA).
Methods:
Using the CT data of 63 patients who underwent THA, we calculated the ROM of flexion (Flex), internal rotation (Int-R) and external rotation (Ext-R) using 3D dynamic analysis software. We measured the distance between the anterior surface of the stem and anterior aspect of the greater trochanter (GTa length) at the cutting point and between the tip of the antero-inferior iliac spine (AIIS) and coronal plane of both femoral heads (AIIS length), as a parameter of the femur and pelvis, respectively. The relationship between the ROM, bone anatomy and impingement site was evaluated.
Results:
We found a significant decrease in the ROM of Flex and the Int-R to be inversely proportional to the GTa and AIIS length. In Flex and Int-R, the anterior intertrochanteric region often impinges on the AIIS in patients with larger bone anatomy.
Conclusions:
We demonstrated that the bone morphology of the hip substantially affects the ROM of Flex and Int-R, especially in patients with large bone anatomy. For these patients we should consider bony impingement in THA.