Related Experiment Video
Updated: May 9, 2026


Measurement of the Hepatic Venous Pressure Gradient and Transjugular Liver Biopsy
Published on: June 18, 2020
Value and limitations of transpulmonary pressure calculations during intra-abdominal hypertension
Gustavo A Cortes-Puentes1, Kenneth E Gard, Alexander B Adams
1Department of Medicine, Department of Pulmonary and Critical Care Research, University of Minnesota, Regions Hospital, Minneapolis/St Paul, MN, USA.

Objective:
To clarify the effect of progressively increasing intra-abdominal pressure on esophageal pressure, transpulmonary pressure, and functional residual capacity.
Design:
Controlled application of increased intra-abdominal pressure at two positive end-expiratory pressure levels (1 and 10 cm H2O) in an anesthetized porcine model of controlled ventilation.
Setting:
Large animal laboratory of a university-affiliated hospital.
Subjects:
Eleven deeply anesthetized swine (weight 46.2 ± 6.2 kg).
Interventions:
Air-regulated intra-abdominal hypertension (0-25 mm Hg).
Measurements:
Esophageal pressure, tidal compliance, bladder pressure, and end-expiratory lung aeration by gas dilution.
Main Results:
Functional residual capacity was significantly reduced by increasing intra-abdominal pressure at both positive end-expiratory pressure levels (p ≤ 0.0001) without corresponding changes of end-expiratory esophageal pressure. Above intra-abdominal pressure 5 mm Hg, plateau airway pressure increased linearly by ~ 50% of the applied intra-abdominal pressure value, associated with commensurate changes of esophageal pressure. With tidal volume held constant, negligible changes occurred in transpulmonary pressure due to intra-abdominal pressure. Driving pressures calculated from airway pressures alone (plateau airway pressure--positive end-expiratory pressure) did not equate to those computed from transpulmonary pressure (tidal changes in transpulmonary pressure). Increasing positive end-expiratory pressure shifted the predominantly negative end-expiratory transpulmonary pressure at positive end-expiratory pressure 1 cm H2O (mean -3.5 ± 0.4 cm H2O) into the positive range at positive end-expiratory pressure 10 cm H2O (mean 0.58 ± 1.2 cm H2O).
Conclusions:
Despite its insensitivity to changes in functional residual capacity, measuring transpulmonary pressure may be helpful in explaining how different levels of positive end-expiratory pressure influence recruitment and collapse during tidal ventilation in the presence of increased intra-abdominal pressure and in calculating true transpulmonary driving pressure (tidal changes of transpulmonary pressure). Traditional interpretations of respiratory mechanics based on unmodified airway pressure were misleading regarding lung behavior in this setting.

Related Concept Videos
 01:24
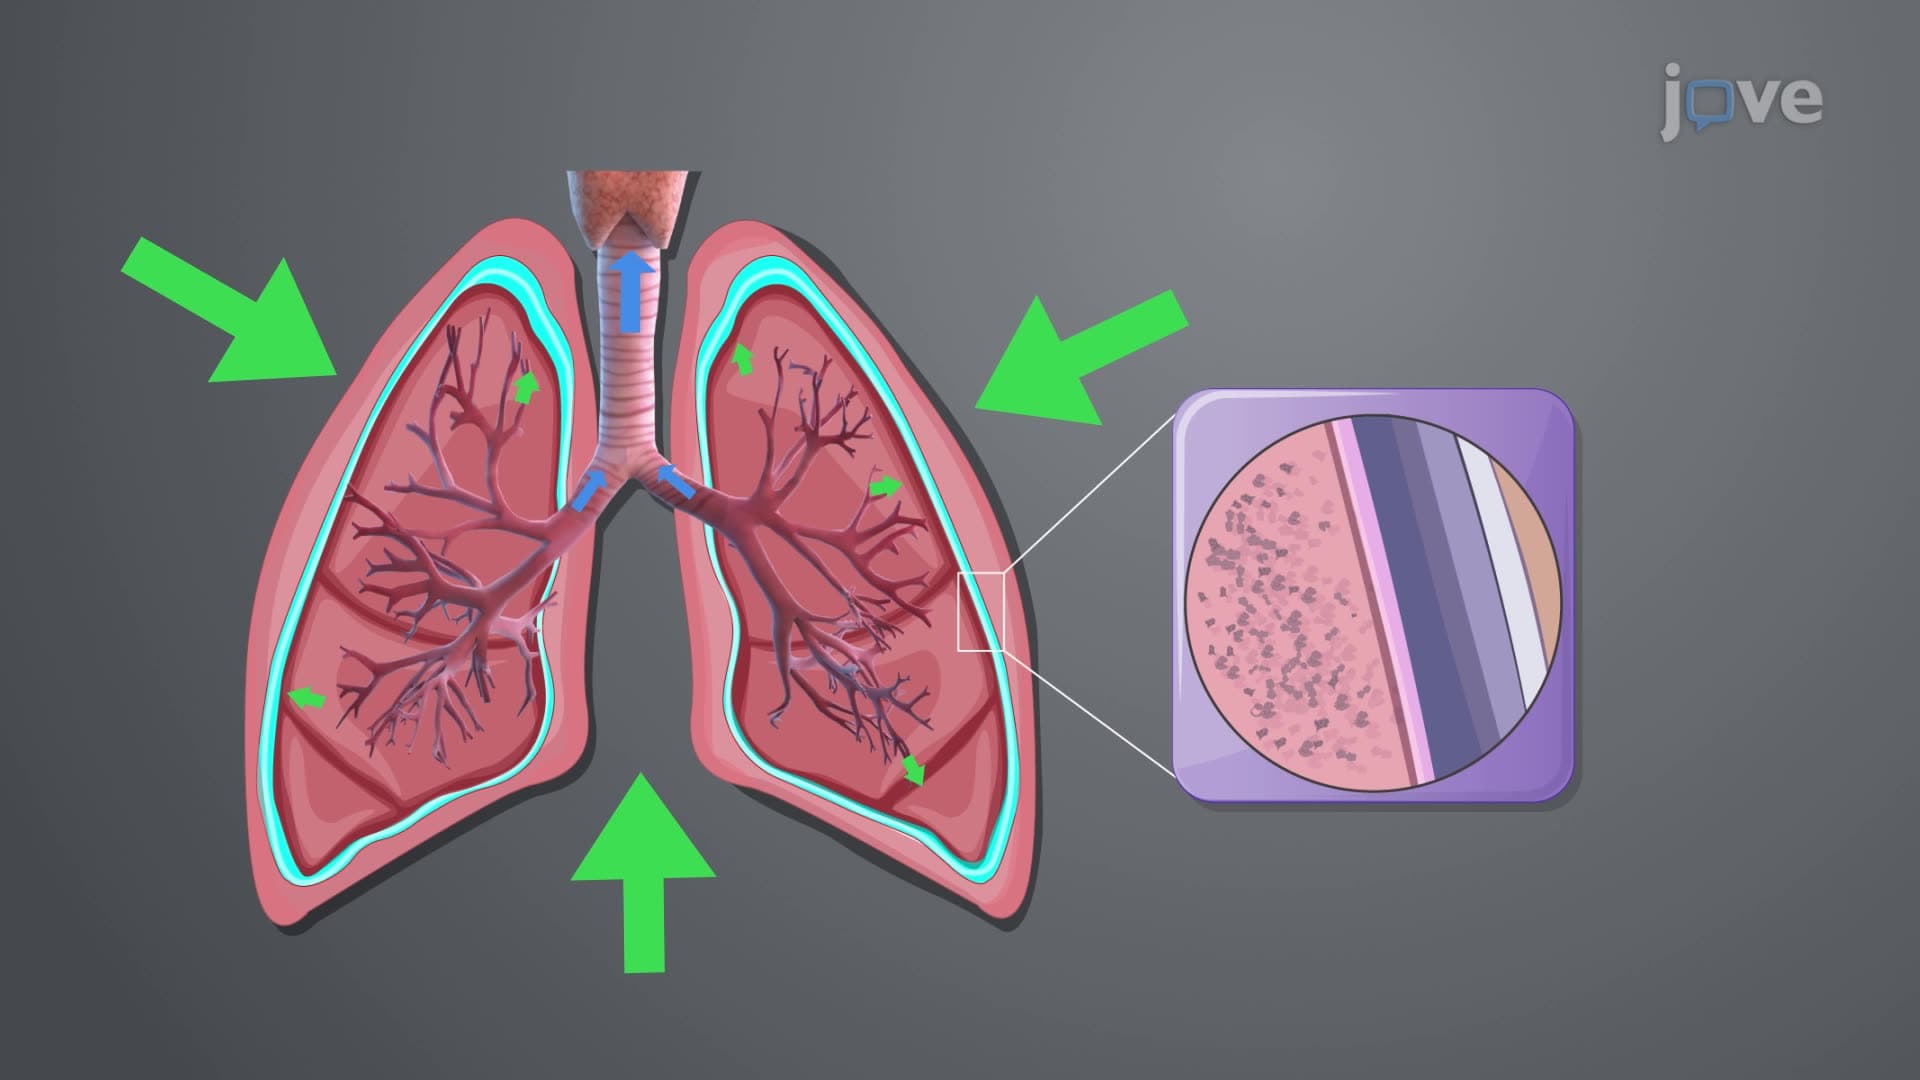
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:24
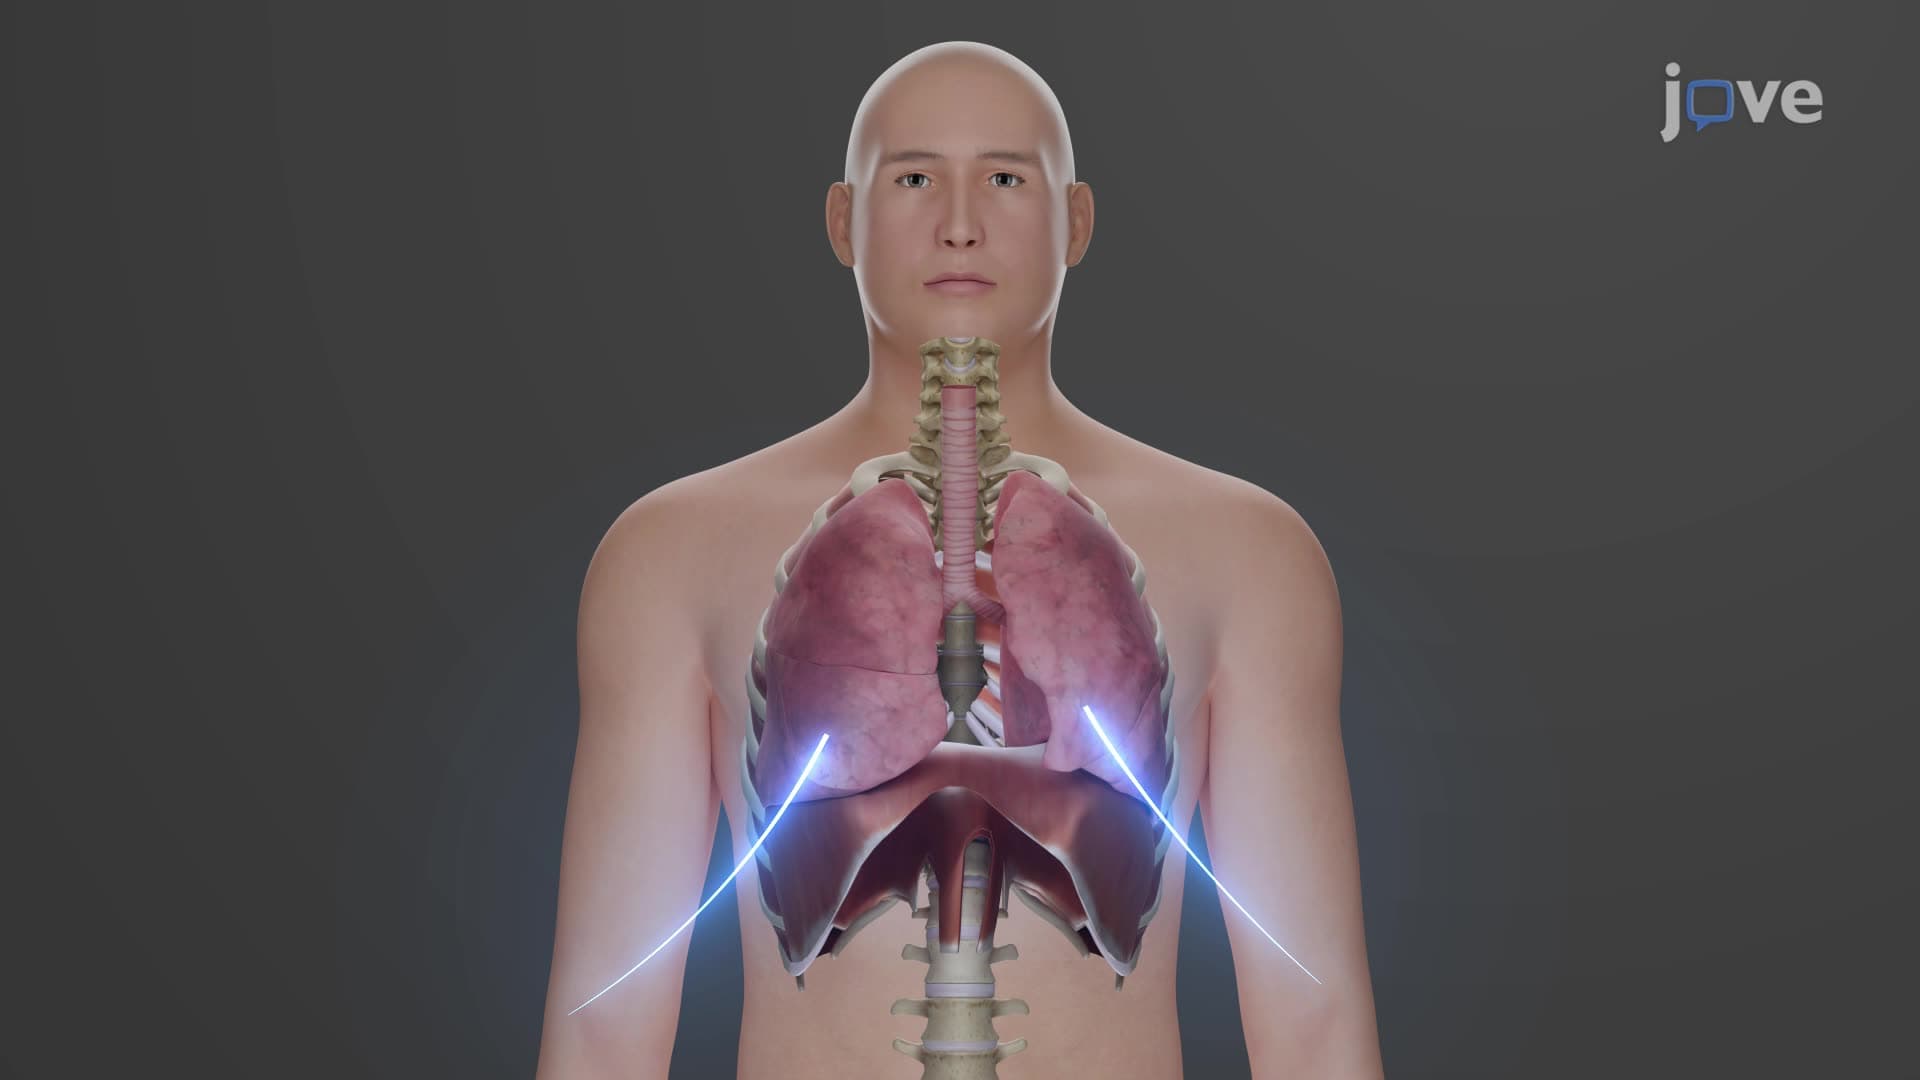
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:14
Increased Intracranial Pressure l: Introduction
 01:17
Measurement of Blood Pressure
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.