Related Experiment Video
Updated: May 9, 2026


Development of a Neonatal Piglet Acute Lung Injury Model Recreating the Early Environment of Preterm Infant Lungs
Published on: October 31, 2025
Pulmonary outcome and its correlates in school-aged children born with a gestational age ≤ 32 weeks
Marie-Luce Choukroun1, Hala Feghali, Sandrine Vautrat
1Univ. Bordeaux, Centre Cardio Thoracique, U1045, F-33000 Bordeaux, France; INSERM, Centre Cardio Thoracique, U1045, F-33000 Bordeaux, France; CHU de Bordeaux, Exploration Respiratoire, F-33000 Bordeaux, France.

Insights
Children born prematurely (≤ 32 weeks gestation) face ongoing respiratory issues. Surfactant therapy reduces lung abnormalities, while bronchopulmonary dysplasia increases restrictive defects, impacting school-aged lung function.
Area of Science:
- Pediatric Pulmonology
- Neonatal Medicine
- Respiratory Medicine
Background:
- Limited data exists on long-term respiratory outcomes for ex-preterm infants born after modern neonatal care advancements.
- Understanding factors influencing school-age respiratory health in extremely preterm infants is crucial.
Purpose of the Study:
- To identify antenatal, neonatal, and early childhood factors associated with respiratory status in school-aged children born at or before 32 weeks of gestation.
- To investigate the long-term respiratory correlates of extremely preterm birth.
Main Methods:
- A cohort of ex-preterm children (≤ 32 weeks gestation) born between 1997-2001 were assessed at school age.
- Evaluations included respiratory questionnaires and comprehensive lung function tests (spirometry, plethysmography, exercise challenge, DLCO).
- Polynomial regression analyses identified factors associated with lung function outcomes.
Main Results:
- Nearly half of the ex-preterm children exhibited obstructive lung abnormalities; 11% had restrictive/mixed abnormalities.
- Exercise-induced bronchoconstriction affected 41%, and 15.5% had reduced diffusing capacity for carbon monoxide (DLCO).
- Surfactant therapy was linked to a lower risk of lung abnormalities, while prior bronchopulmonary dysplasia (BPD) increased the risk of restrictive/mixed defects.
Conclusions:
- Extremely preterm infants remain at significant risk for impaired lung function in school age, especially if they did not receive surfactant therapy.
- Prior history of bronchopulmonary dysplasia is a key predictor of restrictive or mixed lung defects.
- Early childhood respiratory events did not show a significant association with later lung abnormalities.
Background:
There is limited data regarding factors influencing the respiratory outcome at school age of ex-preterms born since the introduction of antenatal steroids, surfactant replacement together with less aggressive ventilation.
Objectives:
To establish the main antenatal, neonatal and early childhood respiratory correlates of respiratory status in school-aged children born at ≤ 32 weeks of gestation.
Methods:
Ex-preterm children born at ≤ 32 weeks of gestation between 1997 and 2001 at Bordeaux University Hospital were evaluated at school age, using a respiratory questionnaire and lung function tests (spirometry, plethysmography, exercise challenge test and CO lung diffusing capacity DLCO measurements). Factors associated with lung function were investigated using polynomial regression analyses.
Results:
Of the 151 included children [mean age: 8.6 ± 0.8 years; mean gestational age, 30.1 ± 1.7 weeks; mean birth weight = 1310 ± 380 g; 68.2% ventilated at birth; 46.4% treated with surfactant; 36.4% with prior bronchopulmonary dysplasia (BPD)], 47% presented obstructive lung abnormalities, 11% restrictive or mixed lung abnormalities, 41% exercise-induced bronchoconstriction, and 15.5% reduced DLCO. Surfactant therapy was independently associated with a lower risk of lung abnormalities (p < 0.05). The association between BPD and lung abnormalities at school age was not significant, but prior BPD increased the risk of restrictive or mixed abnormalities (odds ratio: 6.11, confidence interval [1.1; 33.99]). Early childhood respiratory events were not associated with the occurrence of lung abnormalities.
Conclusion:
Children born at ≤ 32 weeks of gestation remain at risk for impaired lung function at school age in particular when they did not receive surfactant. Restrictive or mixed lung defects are mainly associated with prior BPD.
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:17
Pulmonary Cycle: Exhalation
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:10
Atelectasis II: Pathophysiology
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
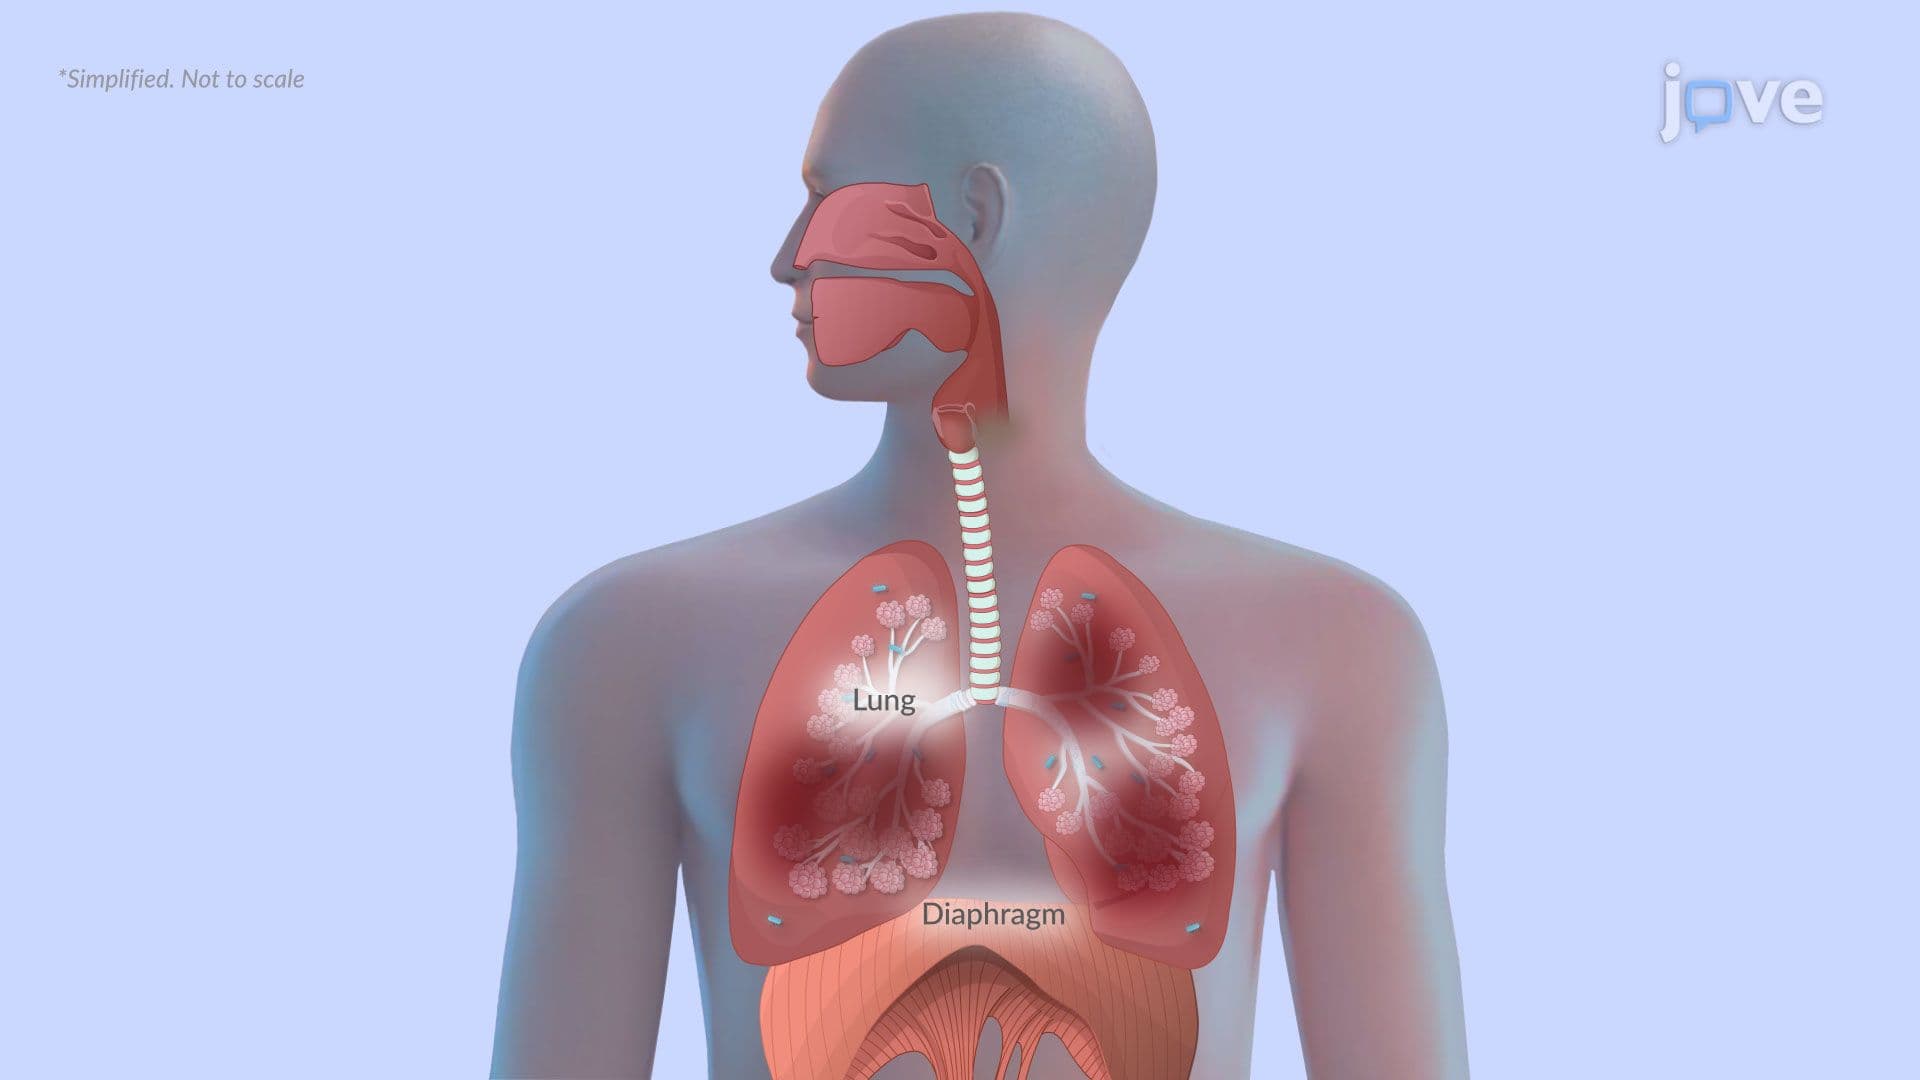 01:23
Chronic Obstructive Pulmonary Disease I: Introduction