Related Experiment Video
Updated: May 9, 2026

Ovariectomy and 17β-estradiol Replacement in Rats and Mice: A Visual Demonstration
Published on: June 7, 2012
20 µg versus >20 µg estrogen combined oral contraceptives for contraception
Maria F Gallo1, Kavita Nanda, David A Grimes
1Division of Epidemiology, The Ohio State University, Room 324 Cunz Hall, 1841 Neil Avenue, Columbus, Ohio, USA, 43210-1351.

Background:
Concern about estrogen-related adverse effects has led to progressive reductions in the estrogen dose in combination oral contraceptives (COCs). However, reducing the amount of estrogen to improve safety could result in decreased contraceptive effectiveness and unacceptable changes in bleeding patterns.
Objectives:
To test the hypothesis that COCs containing ≤ 20 μg ethinyl estradiol (EE) perform similarly as those containing > 20 μg in terms of contraceptive effectiveness, bleeding patterns, discontinuation, and side effects.
Search Methods:
In July 2013, we searched CENTRAL, MEDLINE, and POPLINE, and examined references of potentially eligible trials. We also searched for recent clinical trials using ClinicalTrials.gov and ICTRP. No new trials met the inclusion criteria. Previous searches included EMBASE. For the initial review, we wrote to oral contraceptive manufacturers to identify trials.
Selection Criteria:
English-language reports of randomized controlled trials were eligible that compare a COC containing ≤ 20 μg EE with a COC containing > 20 μg EE. We excluded studies where the interventions were designed to be administered for less than three consecutive cycles or to be used primarily as treatment for non-contraceptive conditions. Trials had to report on contraceptive effectiveness, bleeding patterns, trial discontinuation due to bleeding-related reasons or other side effects, or side effects to be included in the review.
Data Collection And Analysis:
One author evaluated all titles and abstracts from literature searches to determine whether they met the inclusion criteria. Two authors independently extracted data from studies identified for inclusion. We wrote to the researchers when additional information was needed. Data were entered and analyzed with RevMan.
Main Results:
No differences were found in contraceptive effectiveness for the 13 COC pairs for which this outcome was reported. Compared to the higher-estrogen pills, several COCs containing 20 μg EE resulted in higher rates of early trial discontinuation (overall and due to adverse events such as irregular bleeding) as well as increased risk of bleeding disturbances (both amenorrhea or infrequent bleeding and irregular, prolonged, frequent bleeding, or breakthrough bleeding or spotting).
Authors' Conclusions:
While COCs containing 20 μg EE may be theoretically safer, this review did not focus on the rare events required to assess this hypothesis. Data from existing randomized controlled trials are inadequate to detect possible differences in contraceptive effectiveness. Low-dose estrogen COCs resulted in higher rates of bleeding pattern disruptions. However, most trials compared COCs containing different progestin types, and changes in bleeding patterns could be related to progestin type as well as estrogen dose. Higher follow-up rates are essential for meaningful interpretation of results.
More Related Videos
 06:18
An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
 14:13
Detecting Estrogenic Ligands in Personal Care Products using a Yeast Estrogen Screen Optimized for the Undergraduate Teaching Laboratory
Published on: January 1, 2018
Related Concept Videos
 01:22
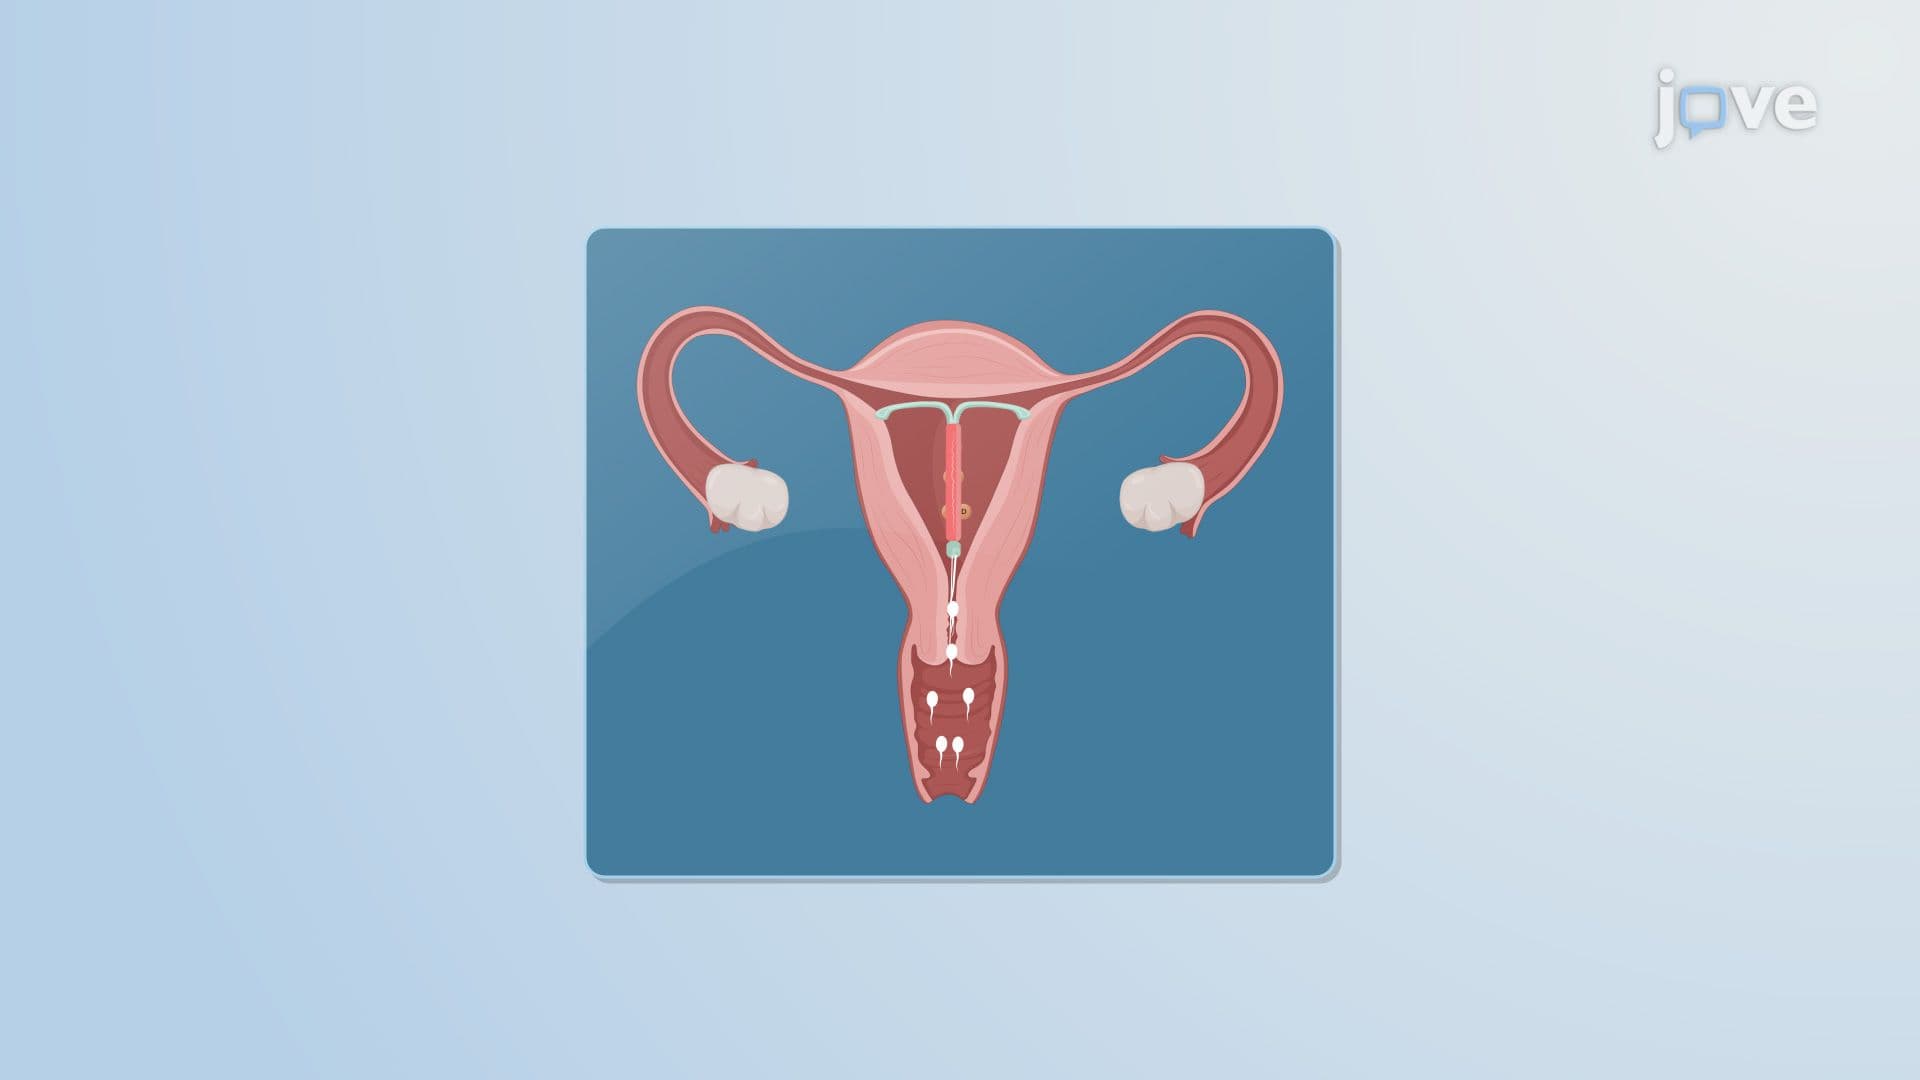
Birth Control Methods
 01:21
Intrauterine Drug Delivery Systems
 01:25
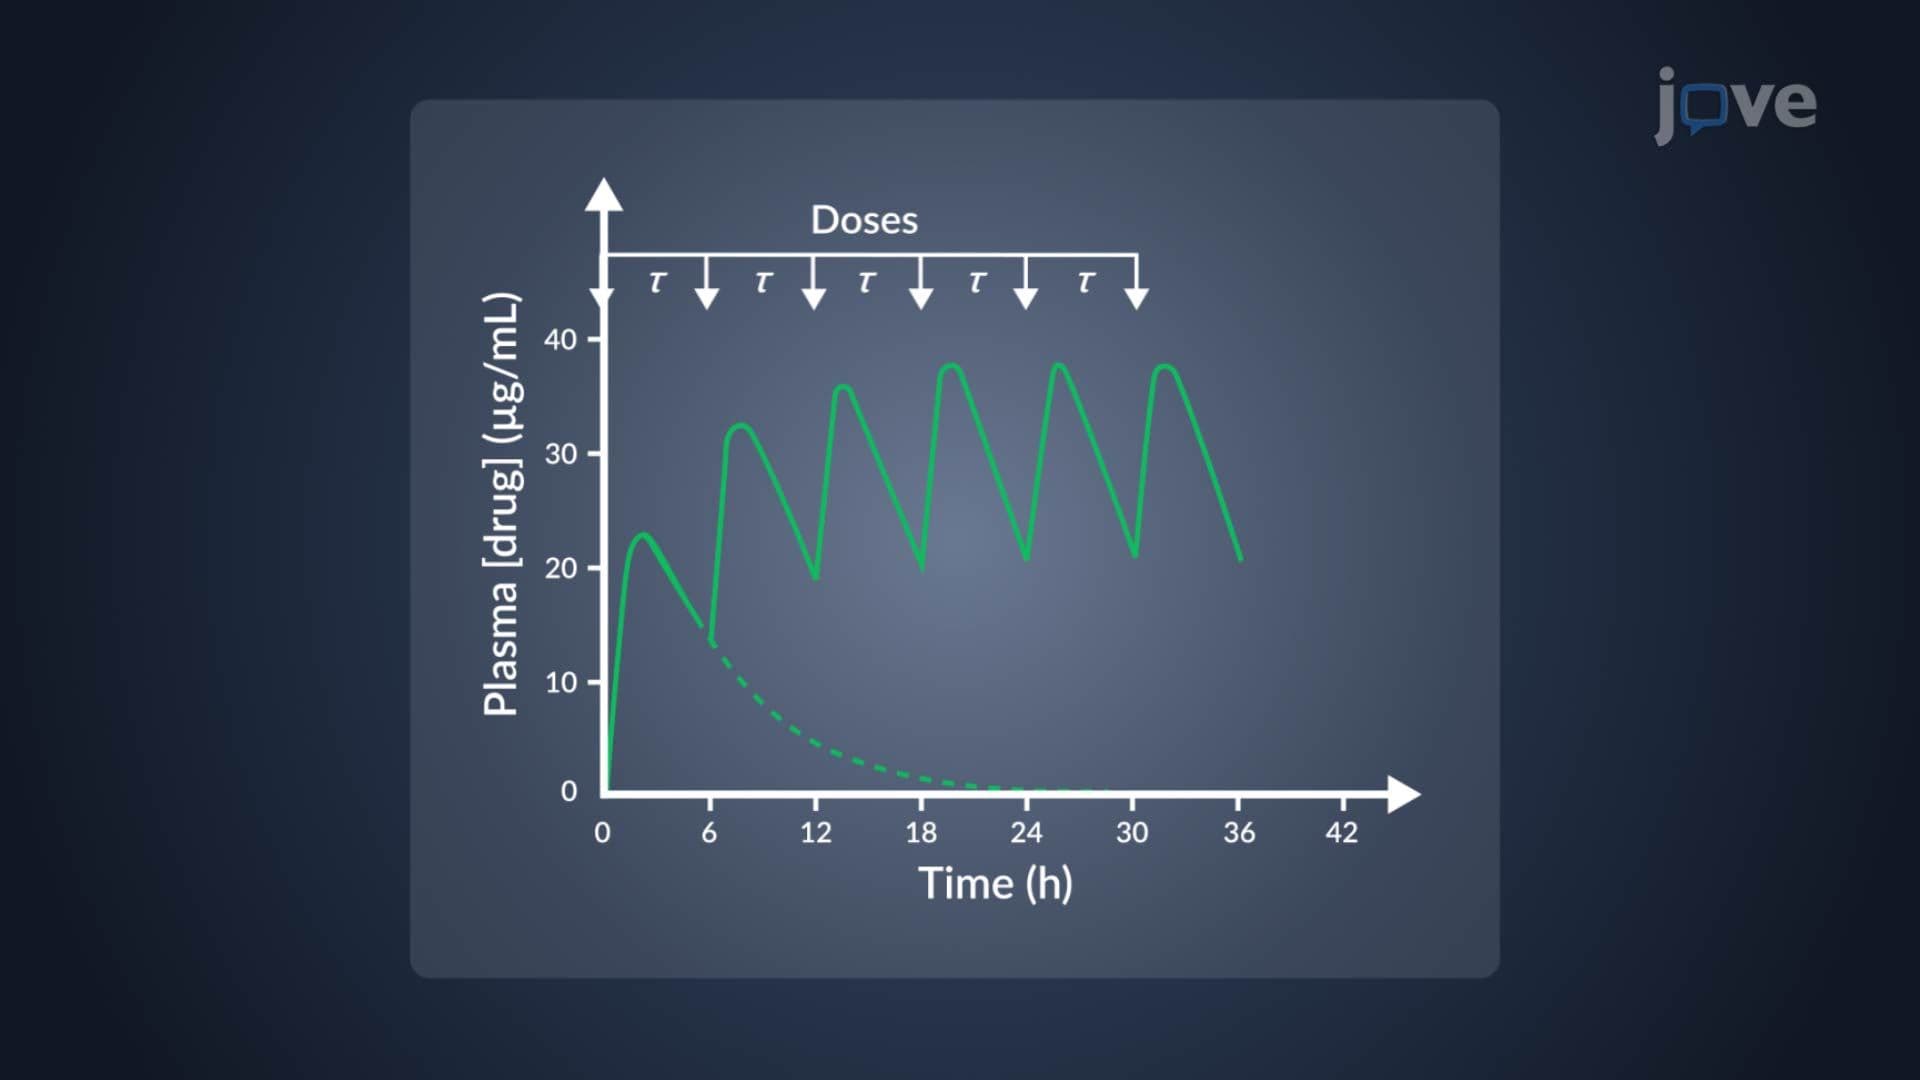
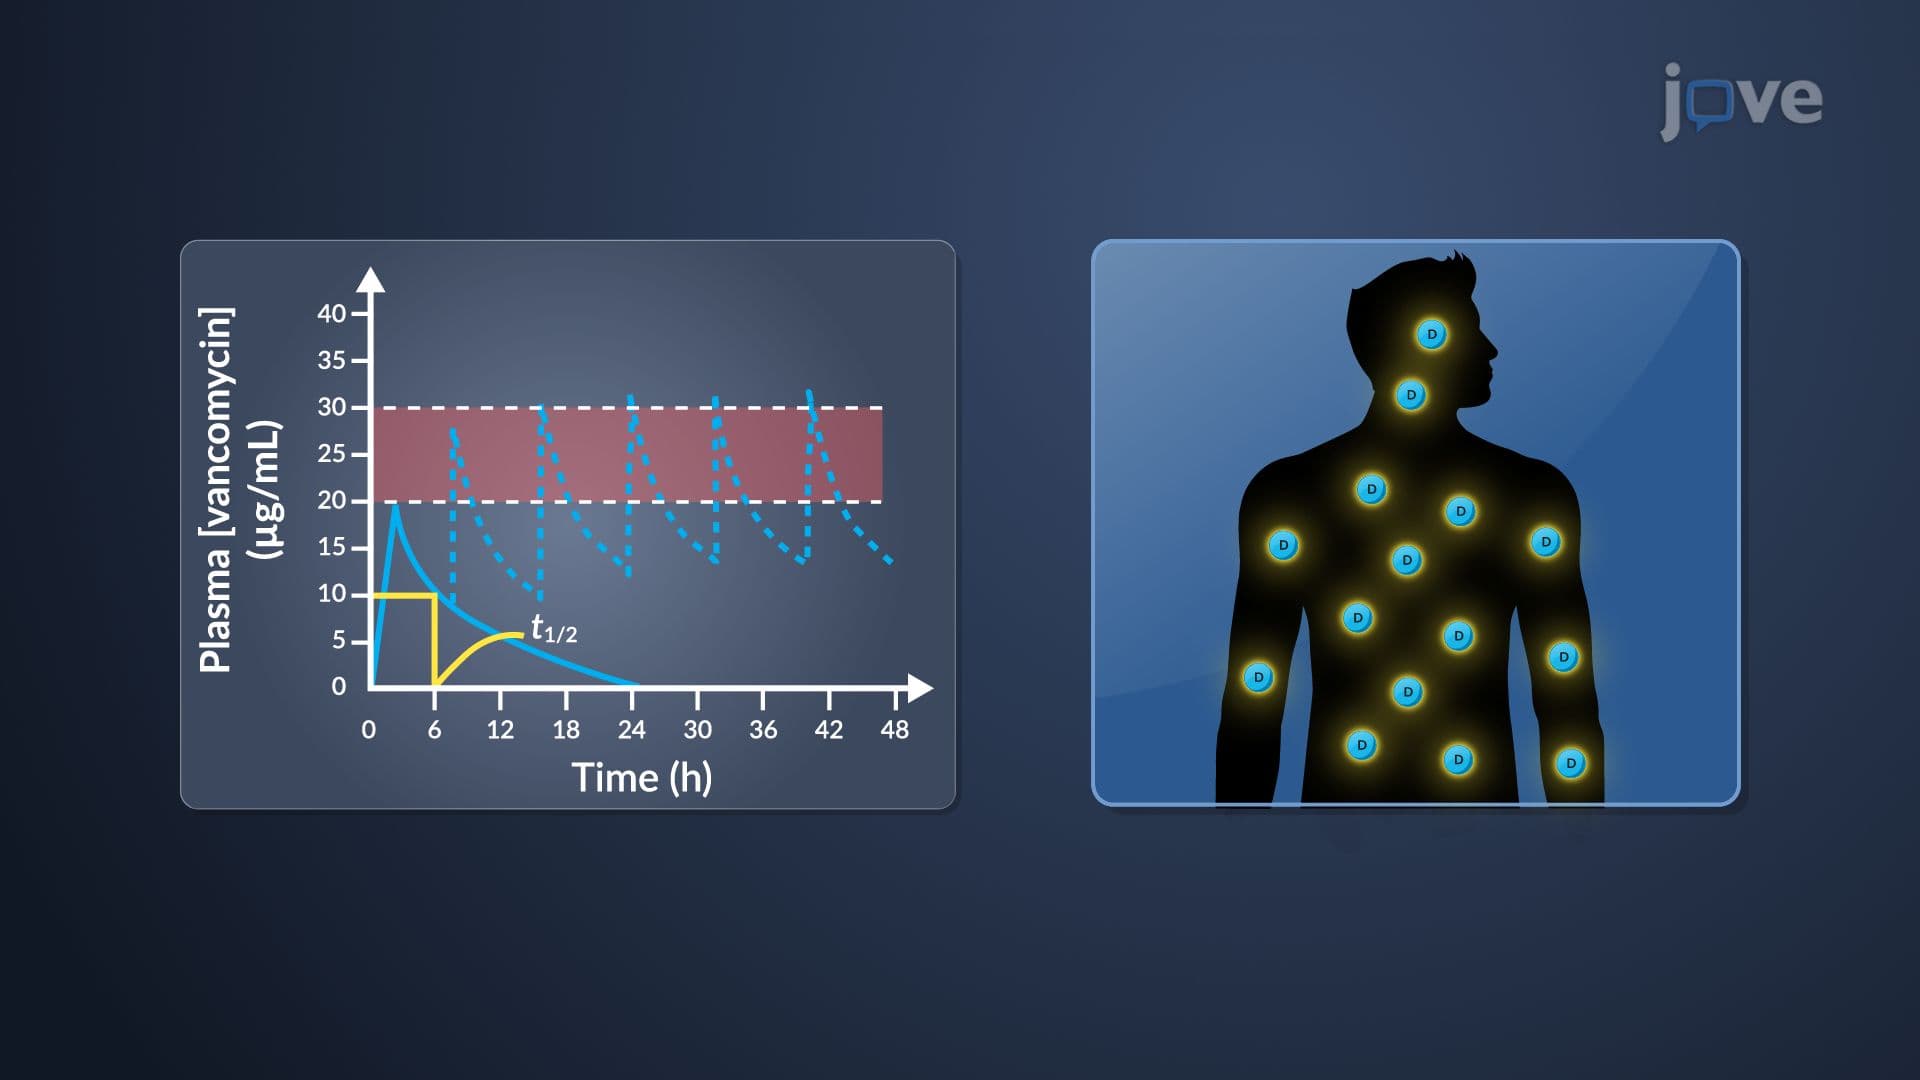
Dosage Regimen: Multiple Oral Dosage
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:19
Dosage Interval and Administration Route: Determination Methods