Related Experiment Video
Updated: May 9, 2026
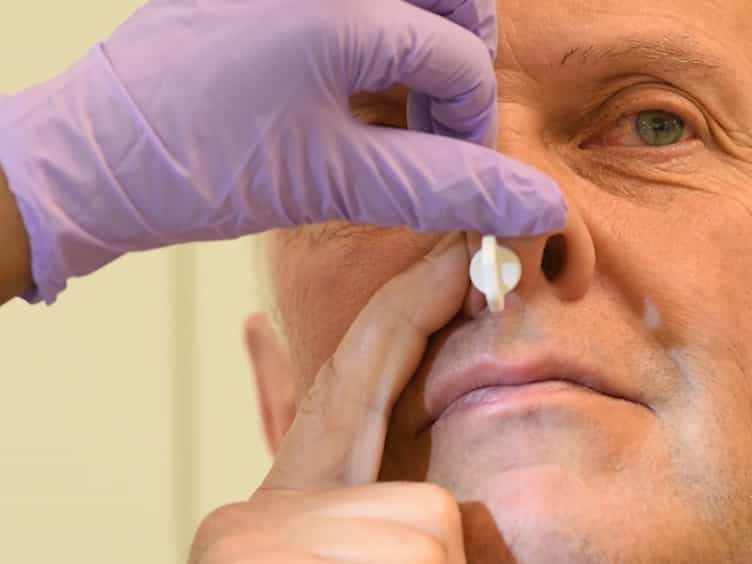

Absorption of Nasal and Bronchial Fluids: Precision Sampling of the Human Respiratory Mucosa and Laboratory Processing of Samples
Published on: January 21, 2018
Modulation of allergen-induced bronchoconstriction by fluticasone furoate and vilanterol alone or in combination
1GlaxoSmithKline Respiratory and Immuno-Inflammation Medicines Development Centre, Stockley Park, UK.

Background:
This placebo-controlled study assessed the effects of the once-daily inhaled corticosteroid (ICS) fluticasone furoate (FF) and long-acting beta(2) -agonist (LABA) vilanterol (VI) on early and late asthmatic responses (EAR/LAR) and airway hyper-responsiveness (AHR).
Methods:
Patients (n = 27) were randomized to FF (100 μg), VI (25 μg), FF/VI (100/25 μg), and placebo for 21 days (four periods). Allergen challenge was performed 1 h post-dose on day 21. AHR was assessed on day 22 using methacholine.
Results:
Allergen challenge caused an early change (0-2 h) in minimum forced expiratory volume in 1 s (FEV(1)) of -1.091 l (95% CI: -1.344; -0.837) following placebo therapy; changes were -0.955 l (-1.209; -0.702), -0.826 l (-1.070; -0.581), and -0.614 l (-0.858; -0.370) following VI, FF, or FF/VI therapy, respectively. Treatment differences were significant for all comparisons between therapies. Mean changes in 0-2 h %FEV(1) were as follows: -28.05 (placebo), -23.10 (VI), -22.33 (FF), and -16.10 (FF/VI). Following placebo, the late change (4-10 h) in weighted mean FEV(1) was -0.466 l (-0.589; -0.343) and -0.298 l (-0.415; -0.181) after VI, and was +0.018 l with both FF/VI (-0.089; 0.124) and FF (-0.089; 0.125). Treatment differences were significant for all comparisons between therapies except FF/VI vs FF. Mean changes in 4-10 h %FEV(1) were as follows: -21.08 (placebo), -14.30 (VI), -5.02 (FF), and -5.83 (FF/VI). AHR 24 h after allergen challenge was significantly reduced with FF/VI and FF vs placebo, and FF/VI was superior to either component.
Conclusion:
Combined treatment with FF/VI provides additive protection from the EAR relative to its components, significant protection over VI alone from the LAR, and confers sustained protection from hyper-responsiveness 24 h post-dose.


Related Concept Videos
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:20
Antiasthma Drugs: Muscarinic Receptor Antagonists
Antimuscarinic agents compete with ACh for the same binding site on the muscarinic receptors. By binding to these receptors, they inhibit the downstream effects of ACh and block the parasympathetic...