Related Experiment Video
Updated: May 9, 2026

Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Prolonged Intracranial Hypertension after Recombinant Growth Hormone Therapy due to Impaired CSF Absorption
Kaoru Obinata1, Ayako Kamata, Keiji Kinoshita
1Department of Pediatrics, Koshigaya Municipal Hospital, Saitama, Japan ; Department of Pediatrics, Juntendo University Urayasu Hospital, Chiba, Japan.

Insights
Idiopathic intracranial hypertension (IIH) is a rare side effect of growth hormone (GH) therapy. This case highlights the importance of considering GH treatment as a potential cause of IIH in children.
Area of Science:
- Pediatric Endocrinology
- Neuro-Ophthalmology
Background:
- Growth hormone (GH) deficiency is treated with recombinant human GH (rhGH).
- Idiopathic intracranial hypertension (IIH) is a condition of elevated intracranial pressure without a clear cause.
Observation:
- A 4-year-old boy with idiopathic GH deficiency developed intractable IIH during rhGH therapy.
- Symptoms included persistent headache, esotropia, and papilledema, with markedly elevated cerebrospinal fluid (CSF) pressure.
- Imaging studies were normal, but CSF absorption was impaired.
Findings:
- IIH developed 9-10 months after initiating GH therapy.
- Discontinuation of GH therapy did not immediately resolve the IIH.
- Treatment with diuretics and prednisolone showed limited efficacy, requiring repeated lumbar punctures for over 2 years.
Implications:
- Growth hormone therapy may be associated with the development of IIH in susceptible individuals.
- IIH is an uncommon but serious adverse event that requires careful consideration during GH treatment.
- This case underscores the need for vigilant monitoring for neurological symptoms in children receiving GH therapy.
Abstract:
We experienced a case of a Japanese boy who developed intractable idiopathic intracranial hypertension (IIH) during growth hormone (GH) treatment. At the age of 4 yr, the boy was diagnosed with idiopathic growth hormone deficiency, and recombinant human GH replacement was initiated. Nine months after initiation of the GH therapy, he began to complain of headache, but papilledema was not observed. His headache persisted thereafter, and right esotropia occurred 10 mo after the initiation of GH therapy, at which time papilledema was detected. No other neurological abnormalities were detected, and the findings of computed tomography and magnetic resonance imaging were normal. In a cerebrospinal fluid (CSF) examination, the pressure was markedly elevated to 450 mmH2O, but no other abnormality was recognized. Impaired CSF absorption was detected using the pressure-volume index technique. The CSF levels of GH and insulin-like growth factor I were not increased. GH therapy was withdrawn after it was suggested that the IIH was associated with the GH therapy, but the headache persisted. The intracranial hypertension did not respond to diuretics, and prednisolone was only transiently effective. Although the funduscopic findings were normalized, increased CSF pressure was still observed. For over 2 yr, repeated lumbar puncture was necessary to protect against visual defect. IIH is an uncommon adverse event during GH therapy, but it must be considered carefully.

Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology
 01:21
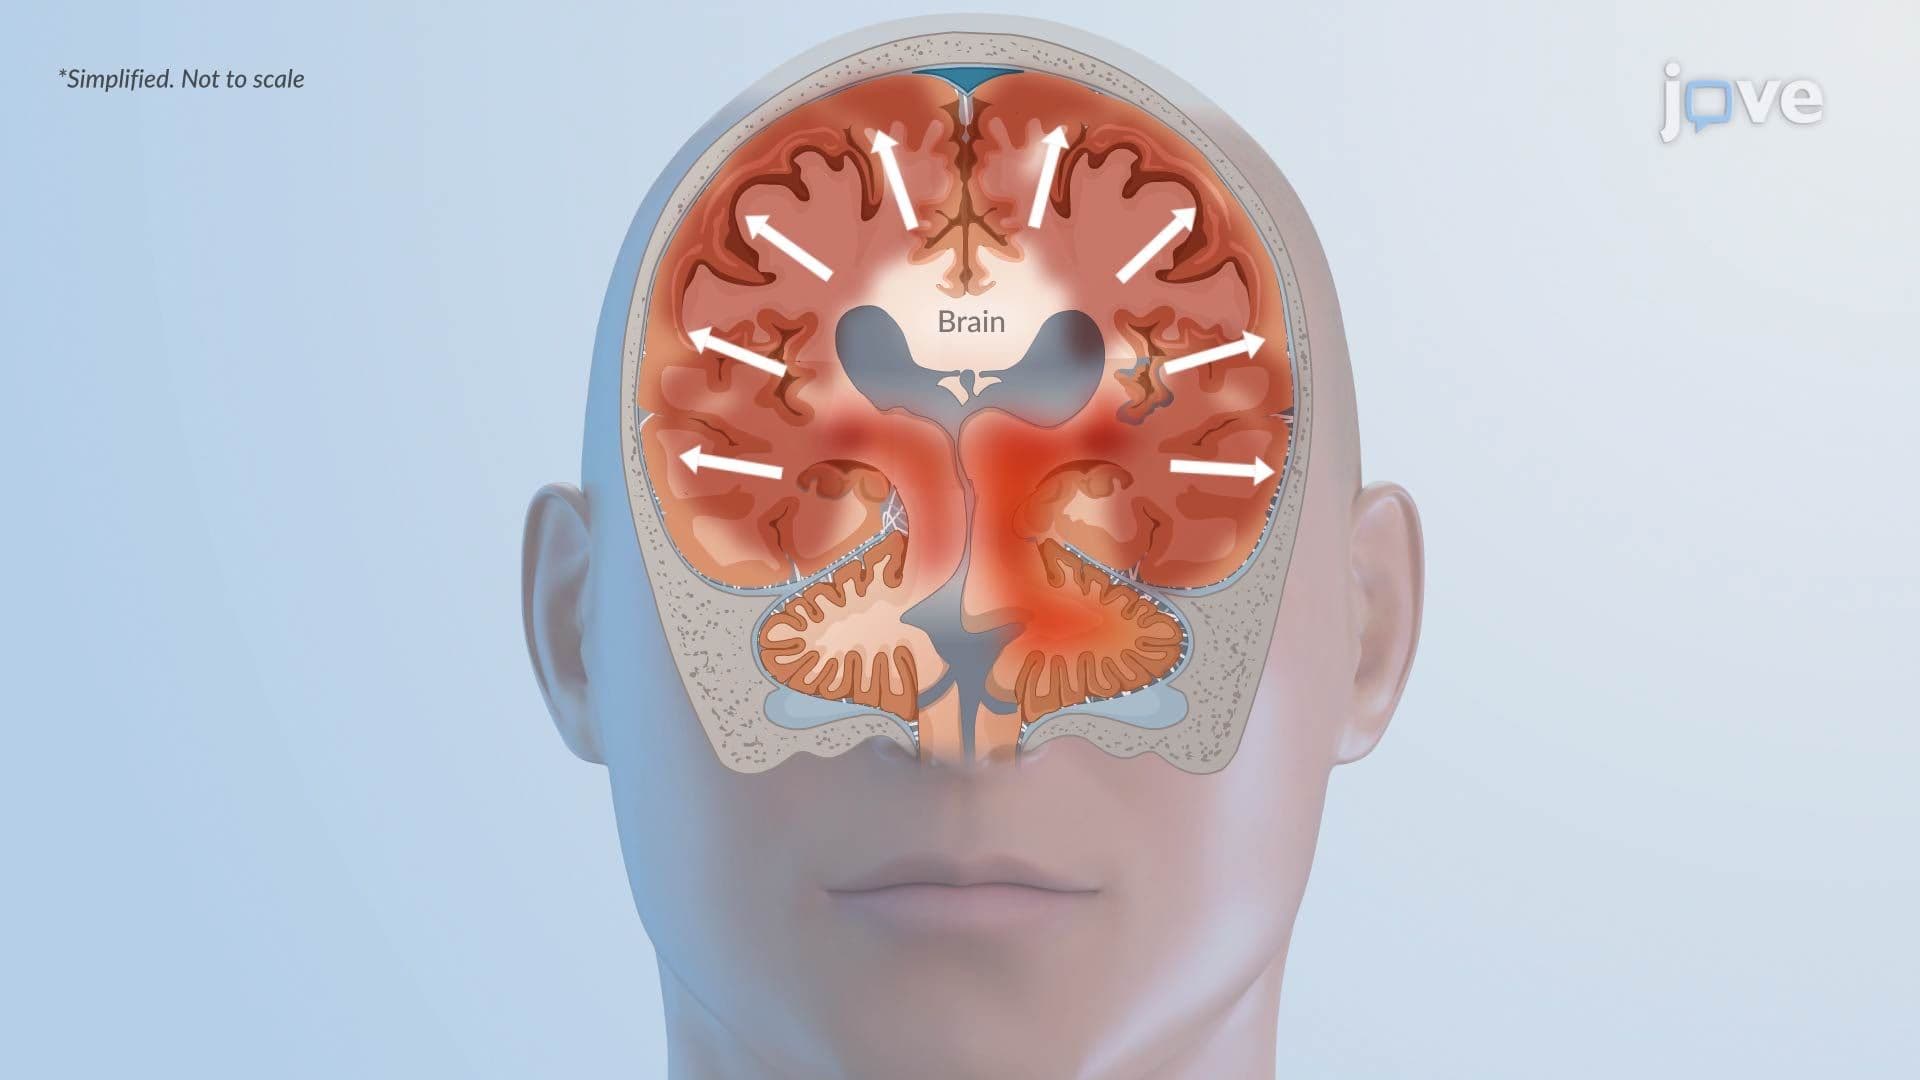
Cytotoxic Edema: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology