Related Experiment Video
Updated: May 8, 2026


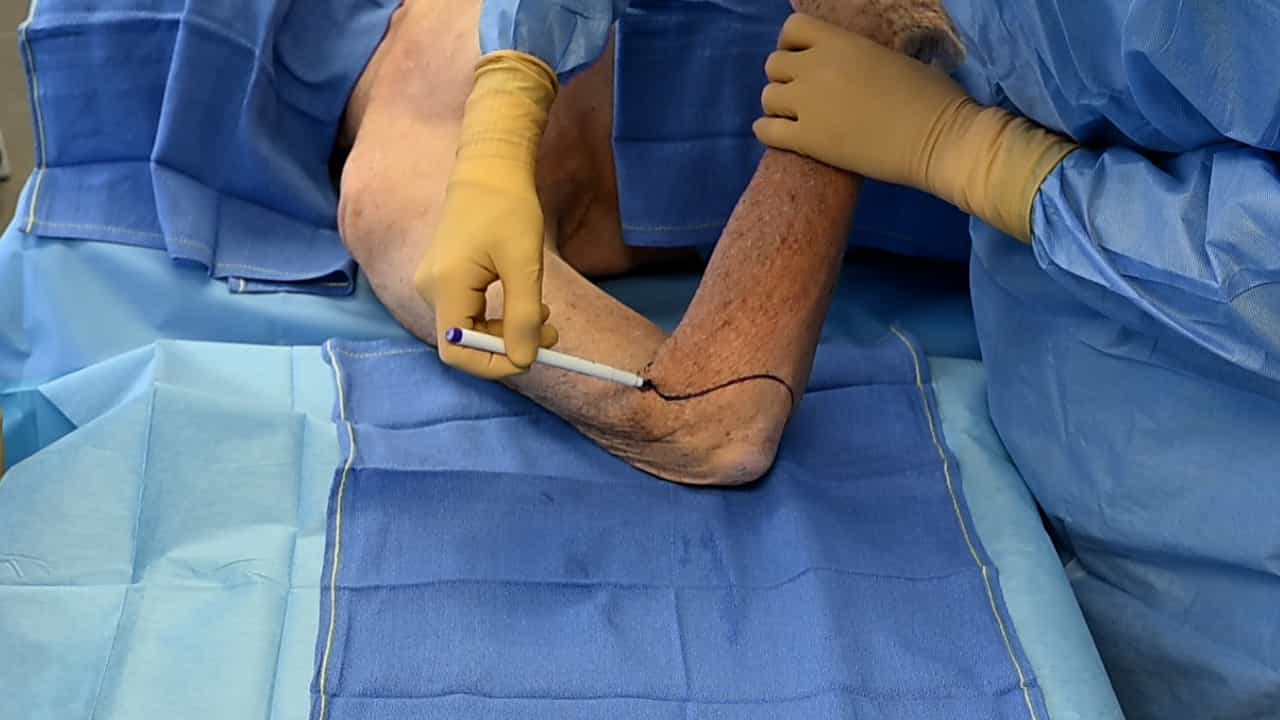
Ultrasound-Guided Needle Release Combined with Corticosteroid Injection for the Treatment of Supinator Syndrome
Published on: May 26, 2023
[Brachioradialis rerouting for restoration of forearm supination or pronation]
Y Gugger1, K-H Kalb, K-J Prommersberger
1Klinik für Handchirurgie, Herz- und Gefäß-Klinik GmbH, Salzburger Leite 1, 97616, Bad Neustadt/Saale, Deutschland. yoko.gugger@handchirurgie.de

Objective:
Improvement of active forearm supination or pronation. Reduction of paralytic pronation or supination posture.
Indications:
Disability or impairment of active supination or pronation due to cerebral palsy, obstetric palsy or traumatic brachial plexus palsy, quadriplegia or paralysis from other causes.
Contraindications:
Inadequate passive range of motion of forearm supination or pronation. Insufficient power of brachioradialis muscle < M4. Insufficient rehabilitation after conservative treatment or neurosurgical intervention with possible improvement of supination or pronation. Lack of patient's cooperation and compliance.
Surgical Technique:
Exposure and mobilisation of brachioradialis muscle. Division of brachioradialis tendon distally with Z-plasty. Passing distal tendon through the interosseus space in dorsal to palmar direction for restoration of supination respectively in palmar to dorsal direction for restoration of pronation. Suturing both tendon ends.
Postoperative Management:
Management includes an above elbow cast with the elbow in 70° flexion for 4 weeks. Then active physiotherapy to learn new brachioradialis muscle function for supination or pronation over 1-1.5 years. If needed dynamic orthesis.
Results:
Özkan et al. performed brachioradialis rerouting to restore supination in 5 children between 4 and 14 years with pronation deformity and to restore pronation in 4 children aged 5-9 years with supination deformity. Mean active gain for supination was 81° (40-140°). Active pronation improved from 28 to 49° (30-75°; Özkan et al., J Hand Surg Br 29:263-268, 2004; Özkan et al., J Hand Surg Am 29:22-27, 2004). Between April 2006 and January 2011 we used this technique in 4 patients aged 7-26 years (mean 14 years). Three patients could be followed up. One patient had preoperative a fixed pronation deformity of the forearm in 80° pronation. In this case active range of motion could be improved to 80/30/0° pronation/supination. One patient improved from preoperative 0/0/90° pronation/supination to 30/0/90° postoperatively. In one case no functional improvement of forearm rotation could be achieved in long-term follow-up. No functional loss in forearm rotation to the opposite direction or of the elbow function was observed. Mean follow-up time was 51 months (21-77 months).
Related Concept Videos
 01:16
Muscles that Move the Forearm
Forearm Flexors
The biceps brachii, brachialis, and brachioradialis are forearm flexors. The biceps brachii is made up of two heads. Its long head originates at the supraglenoid tubercle of the scapula, whereas that of the short head is...
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a short...
 01:15
Bones of the Upper Limb: Ulna
 01:12
Arteries of the Upper Limbs
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:16
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi radialis,...