Related Experiment Video
Updated: May 8, 2026
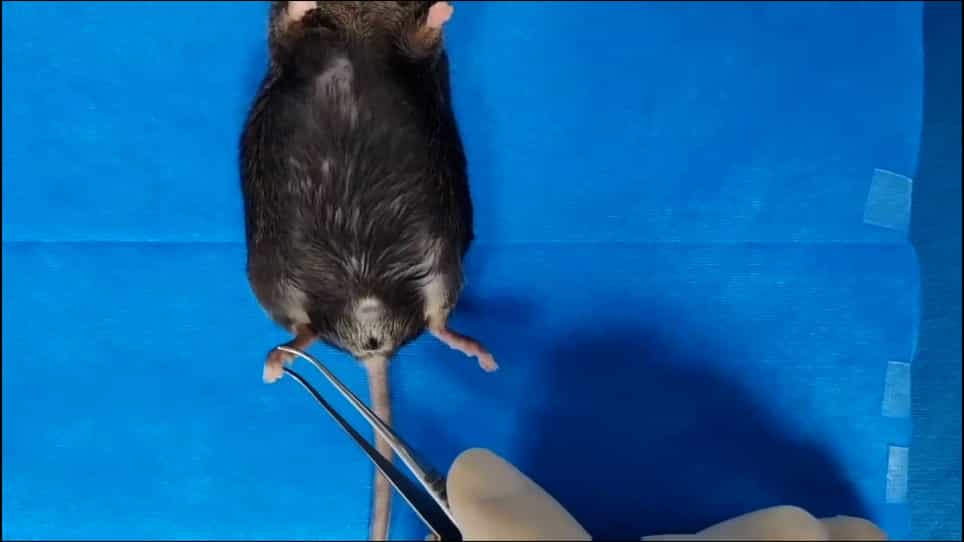

Duodenal-Jejunal Bypass Surgery in Diet-Induced Obese Diabetic Mice
Published on: October 18, 2024
Diabetes remission following metabolic surgery: is GLP-1 the culprit?
1Obesity Unit, Endocrinology and Diabetes Department, Hospital Clínic Universitari, Villarroel 170, 08036 Barcelona, Spain. jovidal@clinic.ub.es

Abstract:
The parallel occurrence of improved glucose tolerance and increased glucagon-like peptide 1 (GLP-1) response to meal intake following metabolic surgery (MS) demonstrated in several studies has led to the notion that GLP-1 is the culprit for the impressive rates of remission of type 2 diabetes mellitus (T2DM) following MS. In this article, we critically review current evidence supporting this view. Recent studies specifically designed to elucidate a causative role of GLP-1 in the antidiabetic effects of MS call into question GLP-1 as a key player for T2DM outcome following MS procedures such as Roux-en-Y gastric bypass and sleeve gastrectomy in morbidly obese subjects. Whether GLP-1 plays a more prominent role in the remission of T2DM following MS in subjects with moderate obesity warrants further studies. Appraisal of the mechanisms involved in the amelioration of hyperglycemia following MS is a priority, as it could help in the battle against the current combined epidemics of obesity and T2DM.

Related Concept Videos
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
 01:15
Hypoglycemia and Glucagon
 01:24
Type II Diabetes II: Pathophysiology
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...