Related Experiment Video
Updated: May 8, 2026

Full-Circle Cauterization of Limbal Vascular Plexus for Surgically Induced Glaucoma in Rodents
Published on: February 15, 2022
Transient unilateral ophthalmoplegia without papilledema in a child with intracranial hypertension
Yusuf Izci1, Alpaslan Kırık, Fatih Mehmet Mutlu
1Department of Neurosurgery, Gulhane Military Medical Academy, Ankara, Turkey.

Insights
Intracranial hypertension can cause complete ophthalmoplegia in children, even without papilledema. Prompt diagnosis and treatment, like shunt insertion, can resolve this rare condition and save lives.
Area of Science:
- Pediatric Neurology
- Ophthalmology
- Neurosurgery
Background:
- Intracranial hypertension typically presents with papilledema and headache.
- Complete ophthalmoplegia is an exceptionally rare sign of increased intracranial pressure in pediatric cases.
- This case highlights a deviation from typical presentations.
Purpose of the Study:
- To report a rare case of pediatric intracranial hypertension presenting with ophthalmoplegia without papilledema.
- To emphasize the importance of considering unusual symptoms in diagnosing intracranial hypertension.
- To illustrate the successful management and resolution of this condition.
Main Methods:
- Case report of a 5-year-old male with unilateral ophthalmoplegia.
- Diagnostic workup included fundoscopic examination and brain MRI, which were normal.
- Treatment involved lumboperitoneal shunt insertion for intracranial hypertension.
Main Results:
- The patient presented with unilateral ophthalmoplegia attributed to increased intracranial pressure.
- Despite normal initial findings (fundoscopy, MRI), intracranial hypertension was confirmed.
- Following lumboperitoneal shunt insertion, ophthalmoplegia resolved within one month.
Conclusions:
- Complete ophthalmoplegia without papilledema can be a manifestation of intracranial hypertension in children.
- Early and precise diagnosis is crucial for effective management.
- Timely intervention to reduce intracranial pressure is vital for patient survival and recovery.
Abstract:
Intracranial hypertension is usually presented with papilledema and headache. Complete ophthalmoplegia without papilledema is a very rare finding of intracranial hypertension in children. A 5-year-old male patient with unilateral ophthalmoplegia due to increased intracranial pressure is presented. The fundoscopic examination and the magnetic resonance imaging of the brain were normal. He underwent lumboperitoneal shunt insertion for intracranial hypertension and the ophthalmoplegia was resolved one month later. Complete ophthalmoplegia without papilledema may occur following intracranial hypertension. Prompt and accurate diagnosis should be done and appropriate treatment to reduce the pressure should be performed to save the life of the children.

Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:25
Glaucoma: Overview
 01:26
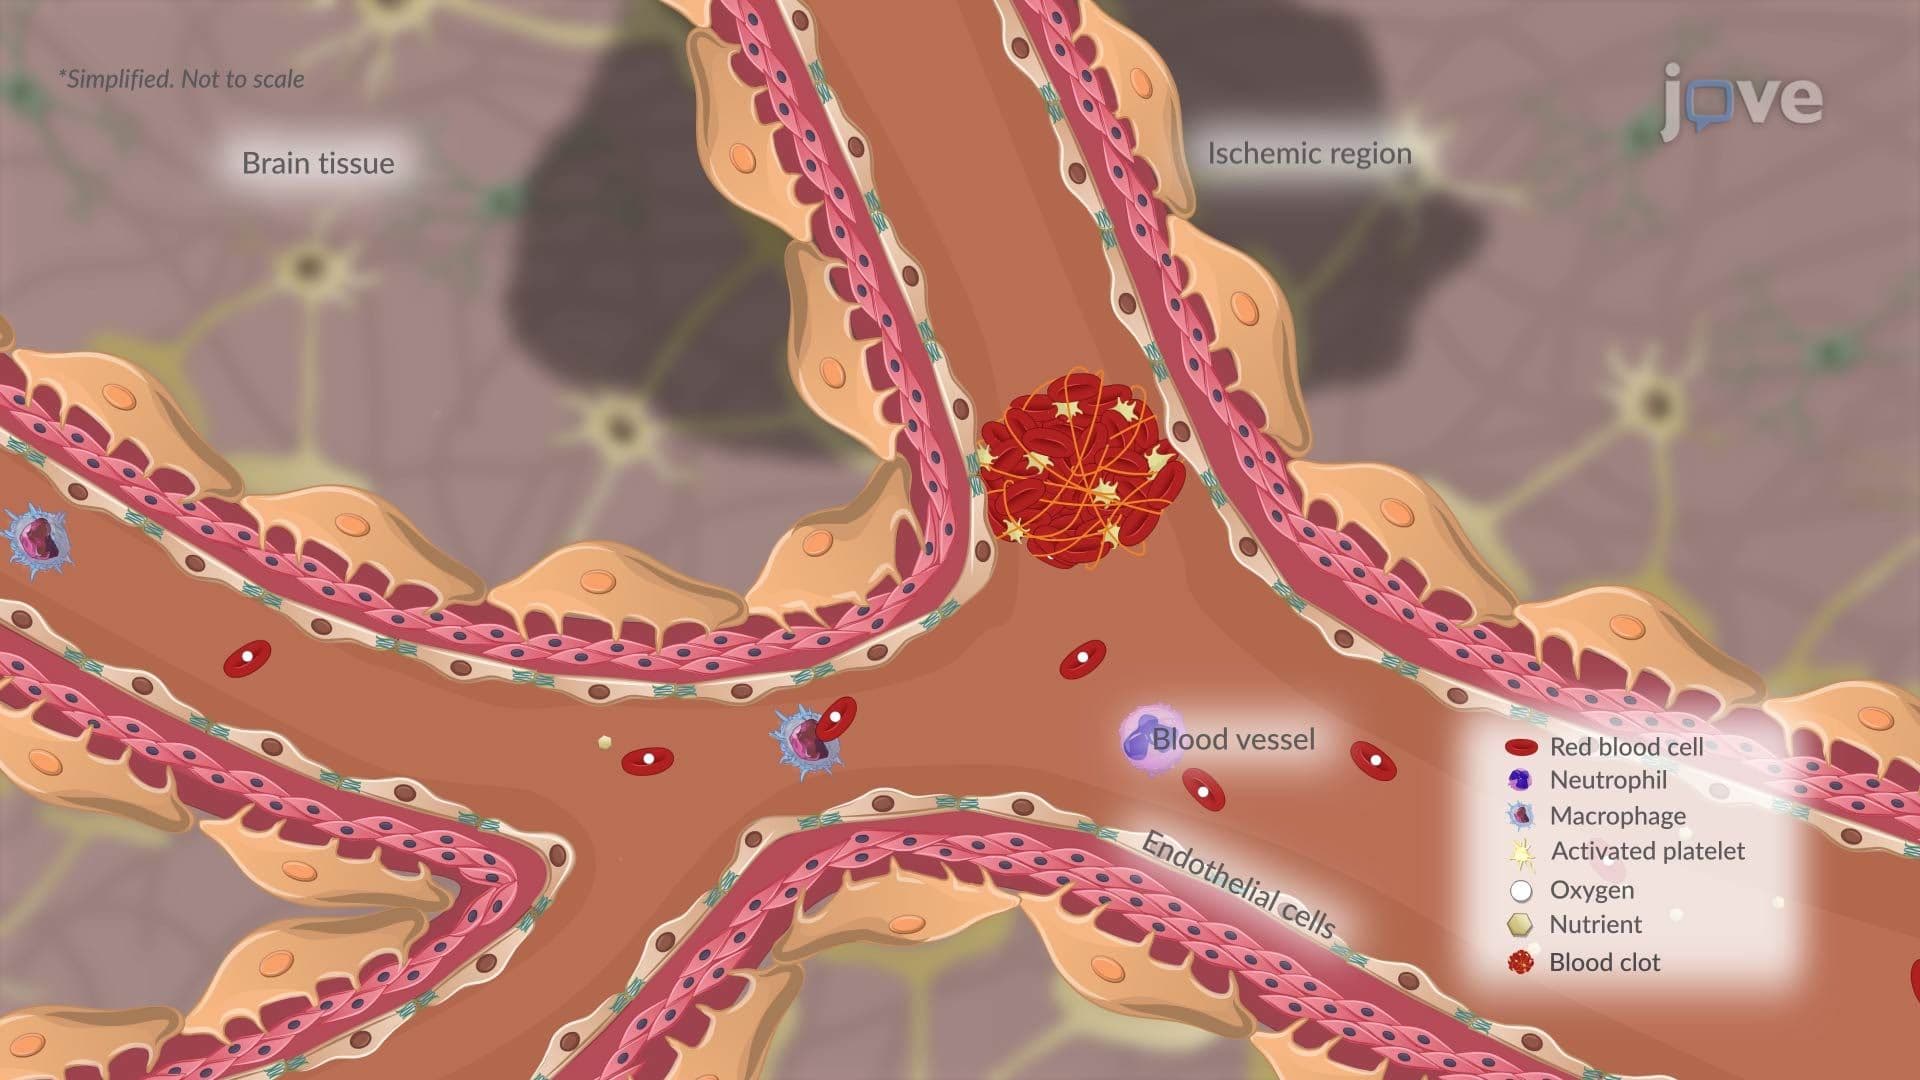
Transient Ischemic Attack l: Introduction
 01:28
Angle Closure Glaucoma: Treatment
 01:22
Cerebral Edema ll: Pathophysiology