Related Experiment Video
Updated: May 8, 2026
Transaxillary First Rib Resection for Treatment of the Thoracic Outlet Syndrome
Published on: September 13, 2020
Long thoracic nerve release for scapular winging: clinical study of a continuous series of eight patients
1Service de chirurgie du membre supérieur, centre de chirurgie orthopédique et de la main, hôpitaux universitaires de Strasbourg, 10, avenue Achille-Baumann, 67403 Illkirch cedex, France.

Unlabelled:
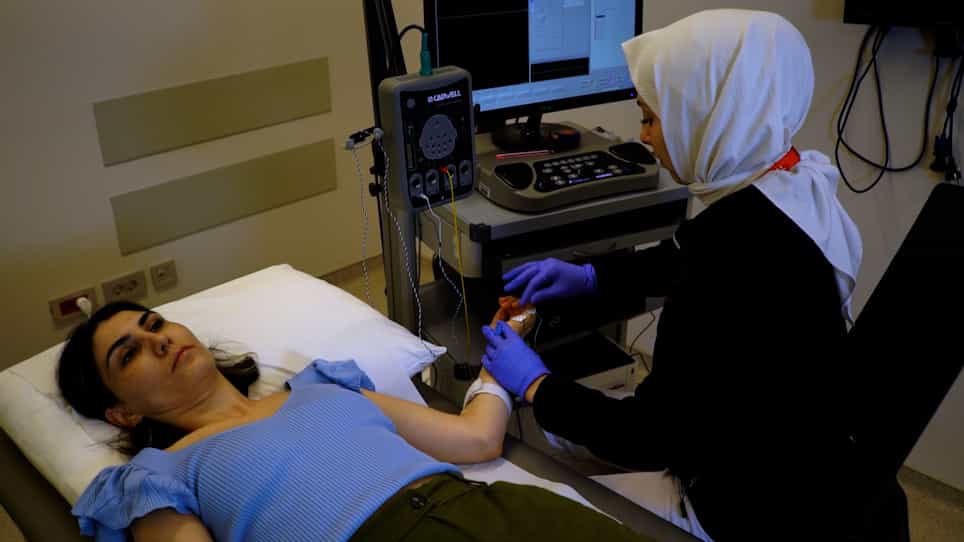
Scapular winging secondary to serratus anterior muscle palsy is a rare pathology. It is usually due to a lesion in the thoracic part of the long thoracic nerve following violent upper-limb stretching with compression on the nerve by the anterior branch of thoracodorsal artery at the "crow's foot landmark" where the artery crosses in front of the nerve. Scapular winging causes upper-limb pain, fatigability or impotence. Diagnosis is clinical and management initially conservative. When functional treatment by physiotherapy fails to bring recovery within 6 months and electromyography (EMG) shows increased distal latencies, neurolysis may be suggested. Muscle transfer and scapula-thoracic arthrodesis are considered as palliative treatments. We report a single-surgeon experience of nine open neurolyses of the thoracic part of the long thoracic nerve in eight patients. At 6 months' follow-up, no patients showed continuing signs of winged scapula. Control EMG showed significant reduction in distal latency; Constant scores showed improvement, and VAS-assessed pain was considerably reduced. Neurolysis would thus seem to be the first-line surgical attitude of choice in case of compression confirmed on EMG. The present results would need to be confirmed in larger studies with longer follow-up, but this is made difficult by the rarity of this pathology.
Level Of Evidence:
III.