Related Experiment Video
Updated: May 8, 2026

Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
AKR1B10 is induced by hyperglycaemia and lipopolysaccharide in patients with diabetic nephropathy
Nicholas Shaw1, Bingmei Yang, Ann Millward
1Department of Molecular Medicine, Institute of Translational and Stratified Medicine, Plymouth University Peninsula Schools of Medicine and Dentistry, John Bull Building, Research Way, Plymouth, PL6 8BU, UK.

Abstract:
Aldose reductase family member B10 (AKR1B10) belongs to the aldo-keto reductase gene superfamily and is closely related to aldose reductase (AKR1B1). It has been shown that AKR1B10 is present in many of the same human tissues as AKR1B1. The objective of this study was to investigate whether AKR1B10 has a role in diabetic nephropathy (DN) by investigating its response to high glucose and inflammation, both of which have been associated with the development and progression of DN. Expression levels of AKR1B10 were determined in peripheral blood mononuclear cells (PBMCs) obtained from 25 patients with type 1 diabetes and nephropathy, 25 without DN and 25 normal healthy controls that were exposed to high glucose (25 mM D-glucose) and also the inflammatory stressor lipopolysaccharide (LPS, 10 μm). Under high glucose and LPS conditions, there was a significant increase in the expression of AKR1B10 in the PBMCs from patients with DN compared to those without DN and the normal controls. In conclusion, these results suggest that AKR1B10 may have an important role in the development and progression of DN.
Related Concept Videos
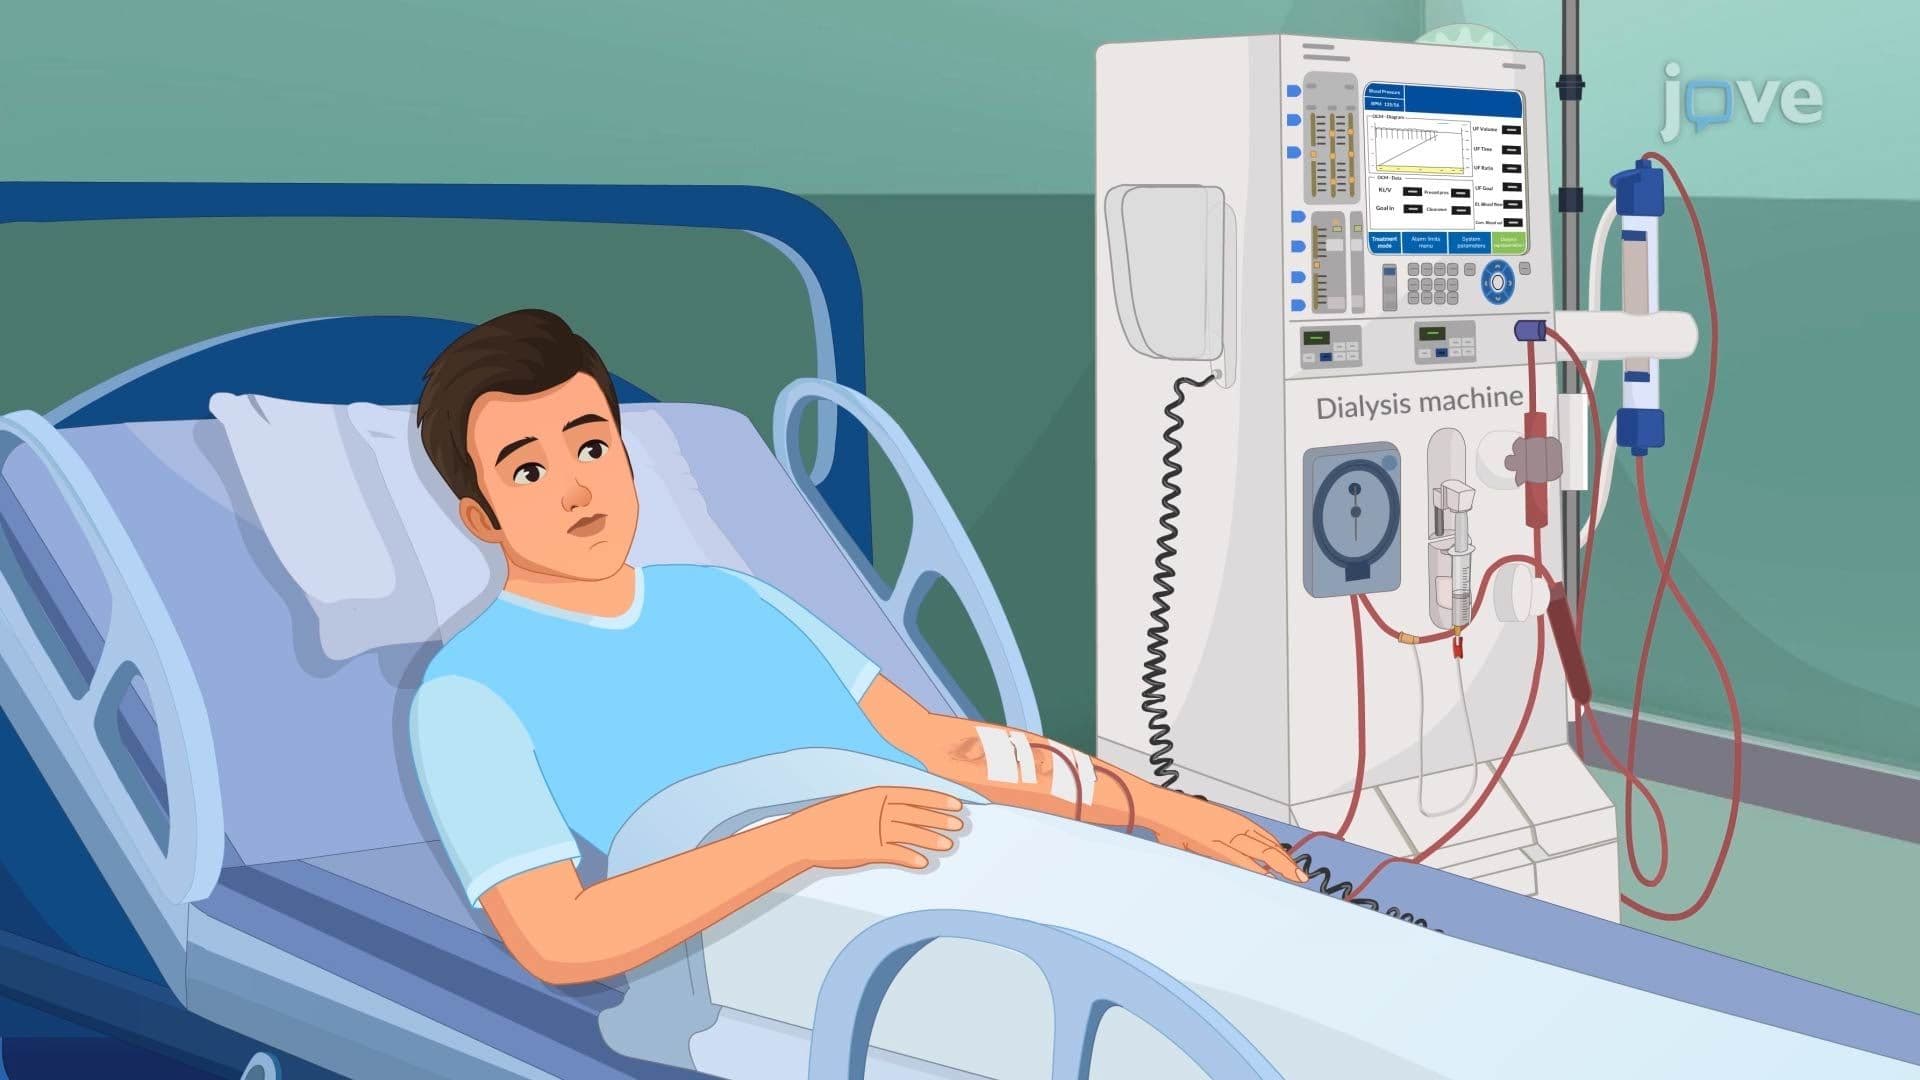 01:28
Diabetic Nephropathy
 01:26
Type I Diabetes II: Pathophysiology
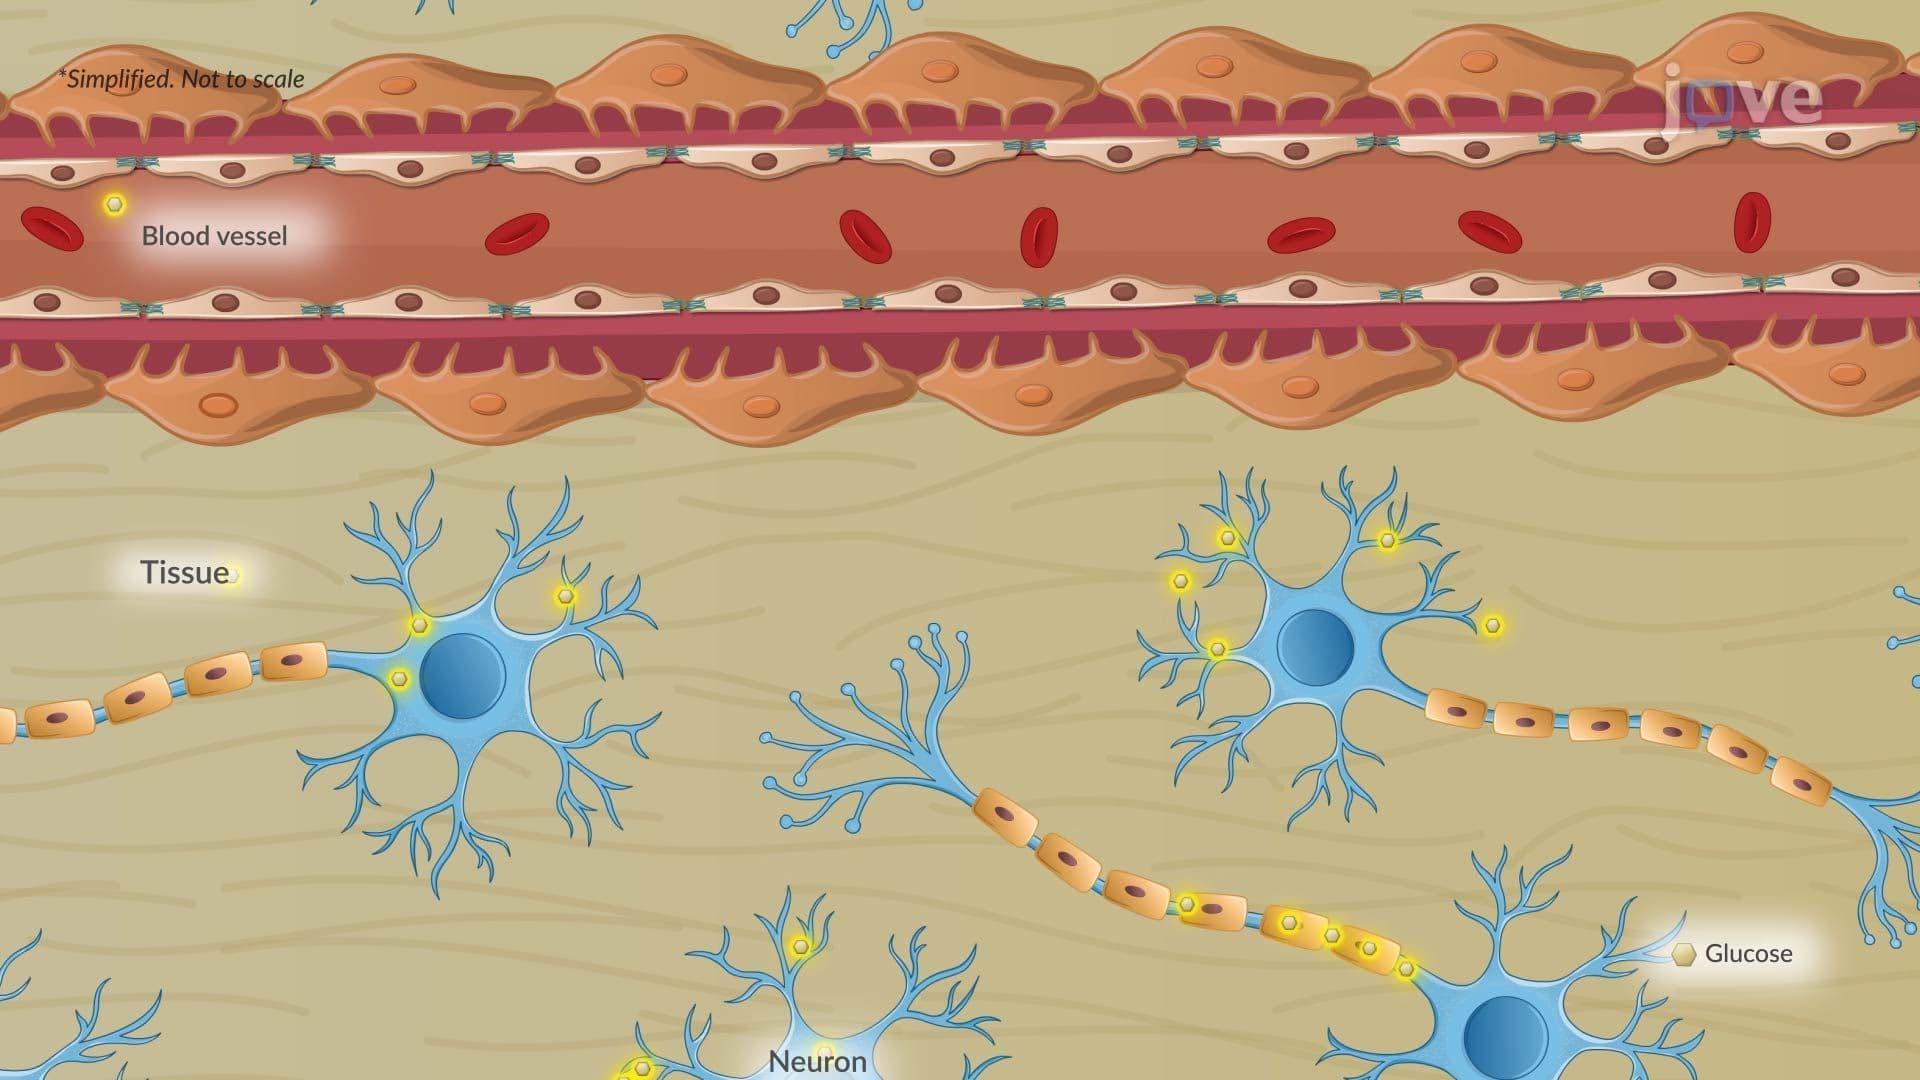 01:22
Diabetic Neuropathy
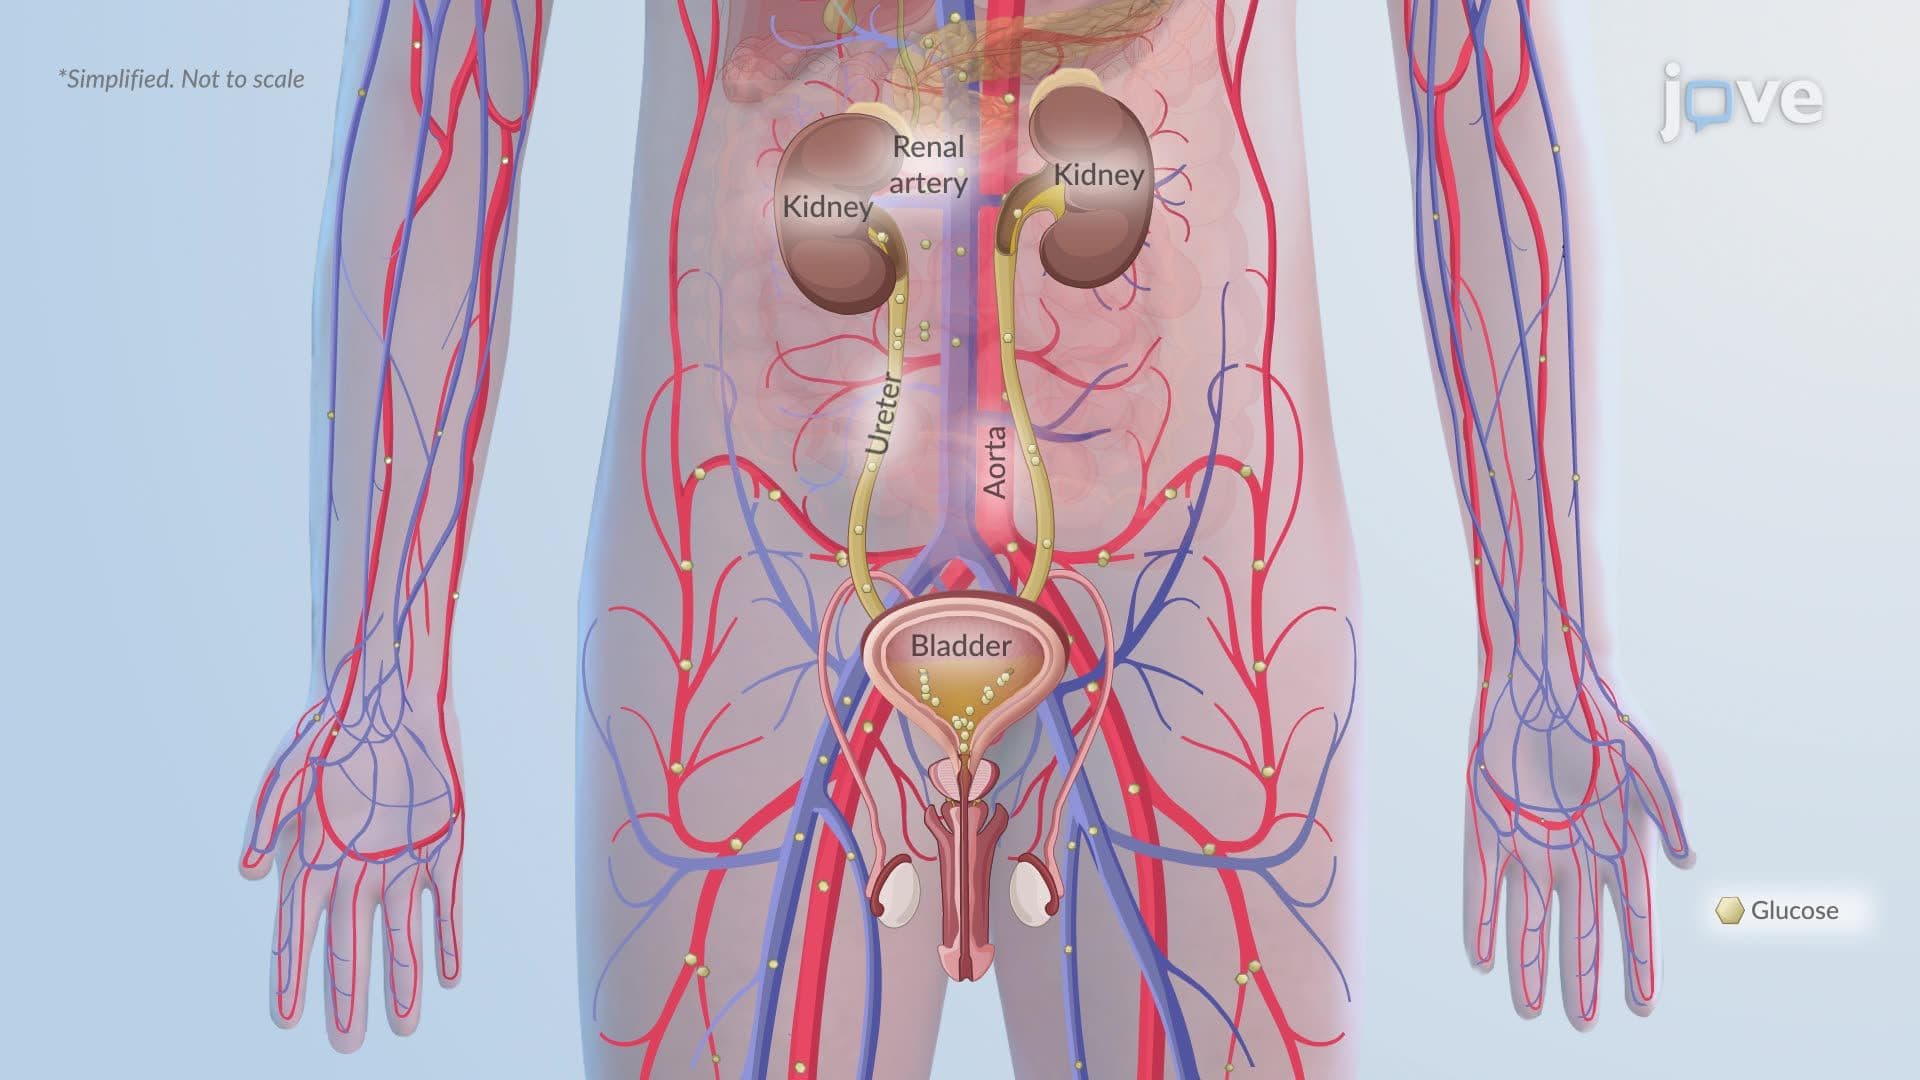 01:22
Diabetic Ketoacidosis ll: Pathophysiology
 01:29
Hyperglycemia
 01:19
Type I Diabetes III: Clinical Manifestations