Related Experiment Video
Updated: May 8, 2026
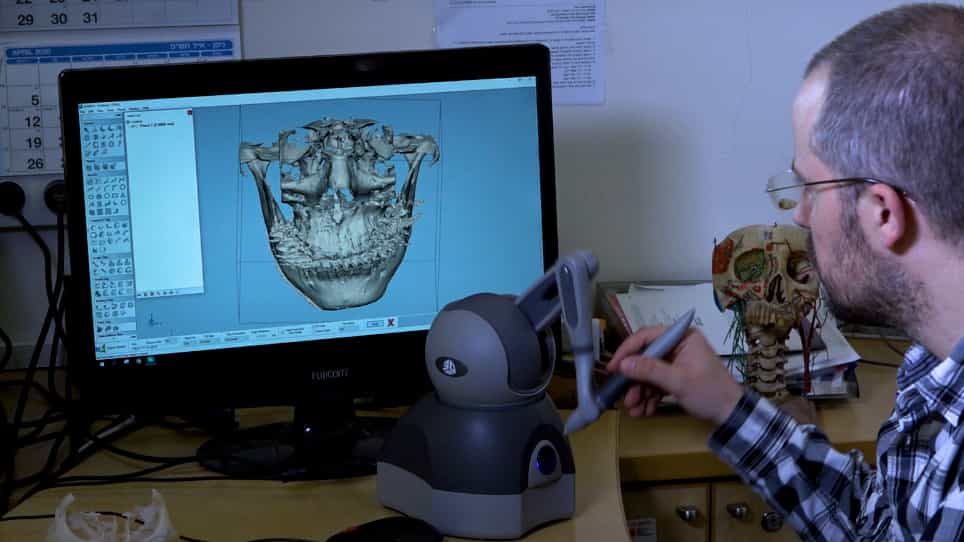

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Outcomes after tongue-lip adhesion or mandibular distraction osteogenesis in infants with Pierre Robin sequence and
P Papoff1, G Guelfi, R Cicchetti
1Pediatric Emergency and Intensive Care, Sapienza University of Rome, Umberto I Policlinico, Rome, Italy.

Insights
Tongue-lip adhesion (TLA) and mandibular distraction osteogenesis (MDO) both help infants with Pierre Robin sequence (PRS) breathing issues. MDO offers faster oral feeding and better airway stability, despite a longer hospital stay.
Area of Science:
- Craniofacial Surgery
- Pediatric Airway Management
- Congenital Anomalies
Background:
- Pierre Robin sequence (PRS) is a congenital condition characterized by micrognathia, glossoptosis, and airway obstruction.
- Severe breathing difficulties in infants with PRS often necessitate surgical intervention when conservative treatments fail.
Purpose of the Study:
- To compare the outcomes of tongue-lip adhesion (TLA) and mandibular distraction osteogenesis (MDO) in infants with severe PRS-related breathing difficulties.
- To evaluate the efficacy of TLA versus MDO in terms of respiratory support weaning and oral feeding resumption.
Main Methods:
- A retrospective, single-centre study (2002-2012) included 18 infants with severe PRS-related airway obstruction.
- Patients underwent either TLA (n=9) or MDO (n=9) for airway management.
- Primary outcomes included successful weaning from respiratory support and achievement of full oral feeding.
Main Results:
- Both TLA and MDO resulted in successful weaning from respiratory support for most infants (8/9 MDO, 9/9 TLA).
- Residual respiratory distress post-discharge was more frequent after TLA (6/9) compared to MDO (1/9).
- Infants undergoing MDO resumed full oral feeding significantly sooner (44±24 days) than those treated with TLA (217±134 days).
Conclusions:
- Both TLA and MDO are safe and effective surgical options for infants with severe PRS-related airway obstruction.
- While MDO may lead to a longer hospital stay, it provides more efficient airway stabilization and faster oral feeding resumption compared to TLA.
Abstract:
The objective was to review and compare outcomes after tongue-lip adhesion (TLA) and mandibular distraction osteogenesis (MDO) in infants with severe breathing difficulties related to Pierre Robin sequence (PRS). A single-centre retrospective (2002-2012) study was carried out; 18 infants with severe breathing difficulties related to PRS resistant to conservative treatment, who underwent TLA or MDO to correct airway obstruction, were enrolled. The primary outcome measures were successful weaning from respiratory support and resumption of full oral feeding. Nine underwent TLA and nine MDO. Eight of the nine infants who underwent MDO and all those treated with TLA were successfully weaned from respiratory support. After discharge, residual respiratory distress was diagnosed more commonly after TLA than after MDO (6/9 vs 1/9, P=0.050). Infants resumed oral feeding sooner after MDO than after TLA (mean days after surgery to full oral feeds 44±24 vs 217±134, P<0.003). The length of hospital stay was longer for infants treated with MDO than for those treated with TLA. The rate of complications was similar. Infants with severe airway obstruction related to PRS can benefit safely from either TLA or MDO. Although MDO lengthens the time to discharge, this option stabilizes airway patency of infants with PRS more efficiently and achieves full oral feeding more rapidly than TLA.
Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques