Related Experiment Video
Updated: May 8, 2026
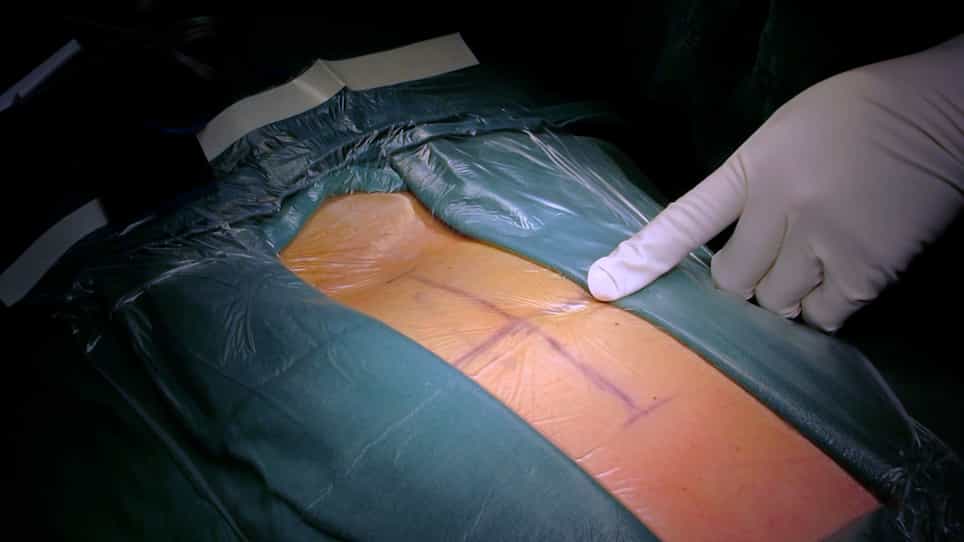

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Posterior vertebral column resection in early onset spinal deformities
D Jeszenszky1, D Haschtmann, F S Kleinstück
1Schulthess Clinic, Spine Center, Lengghalde 2, 8008, Zürich, Switzerland.

Insights
Posterior vertebral column resection (PVCR) effectively treats severe early onset spinal deformities (EOSD) in young children. This technique allows for spinal growth and future fusion, minimizing complications.
Area of Science:
- Pediatric Orthopedics
- Spinal Surgery
- Skeletal Dysplasias
Background:
- Early onset spinal deformities (EOSD) pose life-threatening risks in young children.
- Surgical intervention is often necessary for spinal deformities impacting growth, pulmonary function, and balance.
- Posterior vertebral column resection (PVCR) is an established technique, but its application in very young children is less documented.
Purpose of the Study:
- To present the surgical experience with PVCR in children with EOSD.
- To describe the PVCR surgical technique tailored to the unique anatomy of young children.
- To evaluate the efficacy and safety of PVCR in this pediatric population.
Main Methods:
- Retrospective analysis of four children (mean age 3.7 years) with severe spinal deformity treated with PVCR.
- Single-approach posterior circumferential resection of vertebral bodies and posterior elements.
- Use of transpedicular screw-rod system for correction and stabilization, with fusion limited to the resection site.
- Intraoperative multimodal monitoring and postoperative radiographic assessment.
Main Results:
- Significant reduction in mean Cobb angle (scoliosis) from 69° to 29° and kyphosis from 126° to 61°.
- Mean scoliosis correction of 57% and kyphosis correction of 51%.
- No spinal cord-related complications; two patients experienced anesthesia complications and postoperative infection requiring further intervention.
Conclusions:
- PVCR is an effective surgical option for severe EOSD in young children.
- Adaptations in surgical technique are crucial for addressing the unique anatomy of young patients.
- Non-fusion instrumentation beyond the resection site is advantageous for accommodating spinal growth and future fusion procedures.
Purpose:
Early onset spinal deformities (EOSD) can be life-threatening in very young children. In the growing spine, surgical intervention is often unavoidable and should be carried out as soon as possible. A deformed section of the spine not only affects the development of the remaining healthy spine, but also that of the chest wall (which influences pulmonary function), the extremities and body balance. Posterior vertebral column resection (PVCR) represents an effective surgical solution to address such problems. However, reports in the literature concerning PVCR are mostly limited to its use in adolescents or adults. The purpose of this study was to illustrate our experience with PVCR in EOSD and to describe the surgical technique with respect to the unique anatomy of young children.
Materials And Methods:
Four children [mean age 3.7 (range 2.5-5.2) years] with severe spinal deformity underwent PVCR through a single approach. Multimodal intraoperative monitoring was used in all cases. Surgery included one stage posterior circumferential resection of one vertebral body along with the adjoining intervertebral discs and removal of all posterior elements. A transpedicular screw-rod system was used for correction and stabilisation. Fusion was strictly limited to the resection site, allowing for later conversion into a growing rod construct at the remaining spine, if necessary. Relevant data were extracted retrospectively from patient charts and long spine radiographs.
Results:
The mean operation time was 500 (range 463-541) min, with an estimated blood loss of 762 (range 600-1,050) ml. Mean follow-up time was 6.3 (range 3.5-12.4) years. After PVCR, the mean Cobb angle for scoliosis was reduced from 69° (range 50-99°) to 29° (5-44°) and the sagittal curvature (kyphosis) from 126° (87-151°) to 61° (47-75°). The mean correction of scoliosis was 57 % (18-92°) and of kyphosis, 51 % (44-62°). There were no spinal cord-related complications. In three patients, spinal instrumentation for growth guidance (fusion less growing rod technique) was applied. Two patients had complications: one patient had a complication of anesthesia, halo pin failure, and revision surgery with extension of the instrumentation cranially due to loss of correction; the second patient had a postoperative infection, which required plastic reconstructive measures.
Conclusion:
PVCR appears to be an effective technique to treat severe EOSD. There are important differences in its use in young children when compared with older patients. In patients with EOSD, additional surgical procedures are often necessary during growth, and hence non-fusion instrumentation beyond the vertebral resection site is advantageous, as it permits spinal growth and the later addition of fusion.
More Related Videos

Related Concept Videos
 01:16
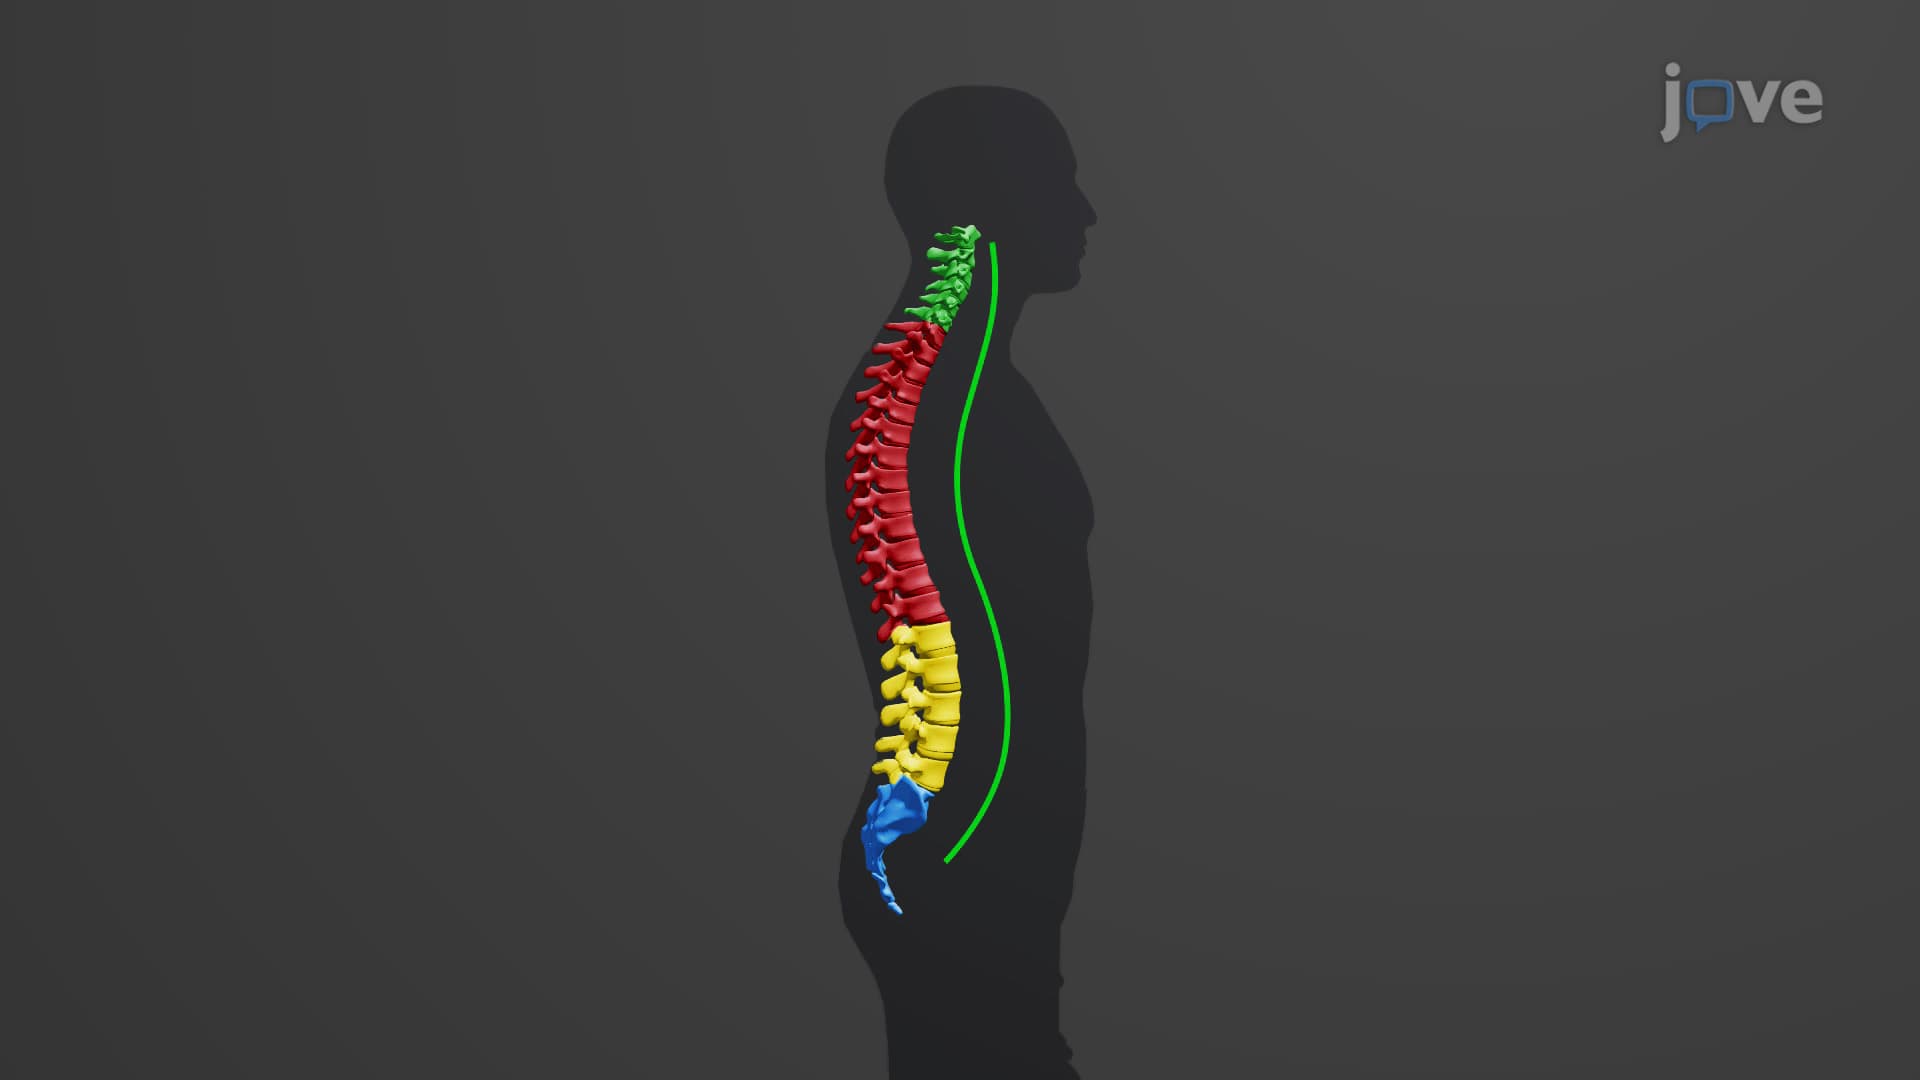
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:30
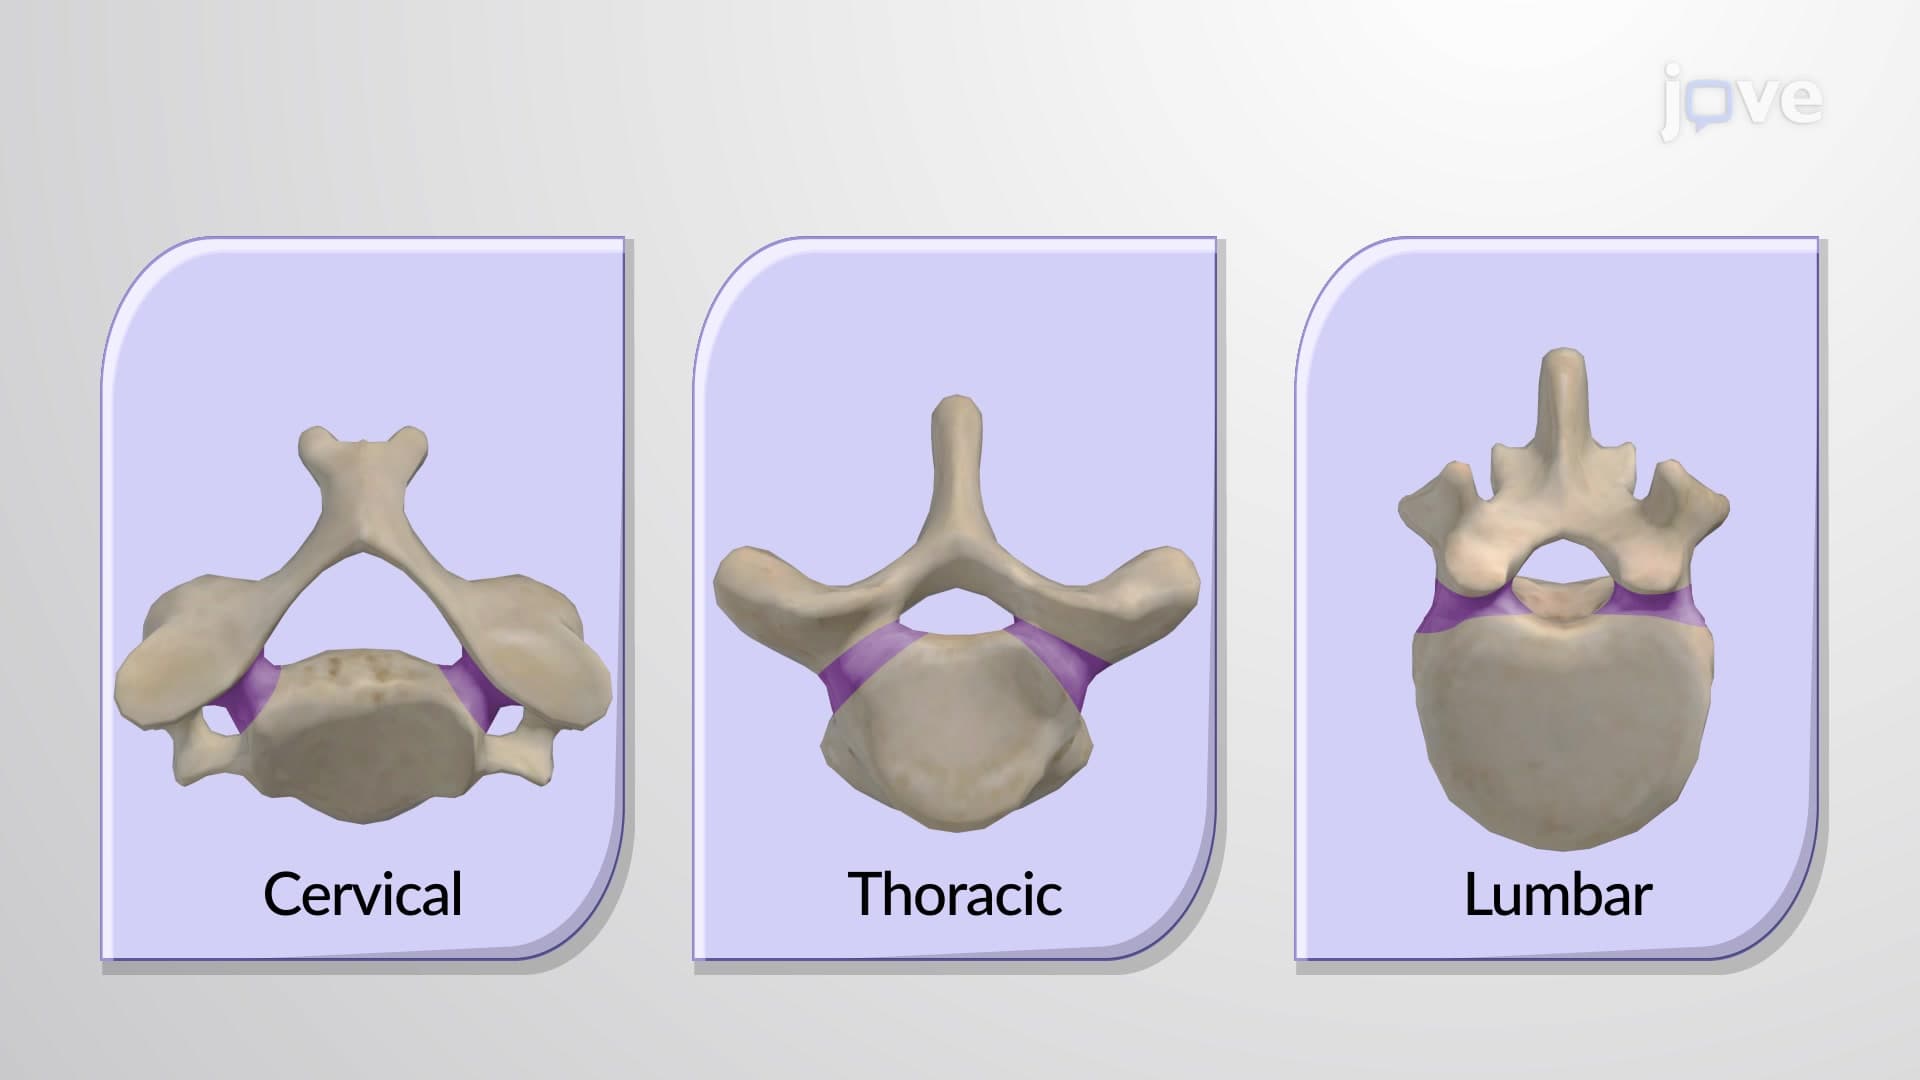
General Structure of a Vertebra
 01:29
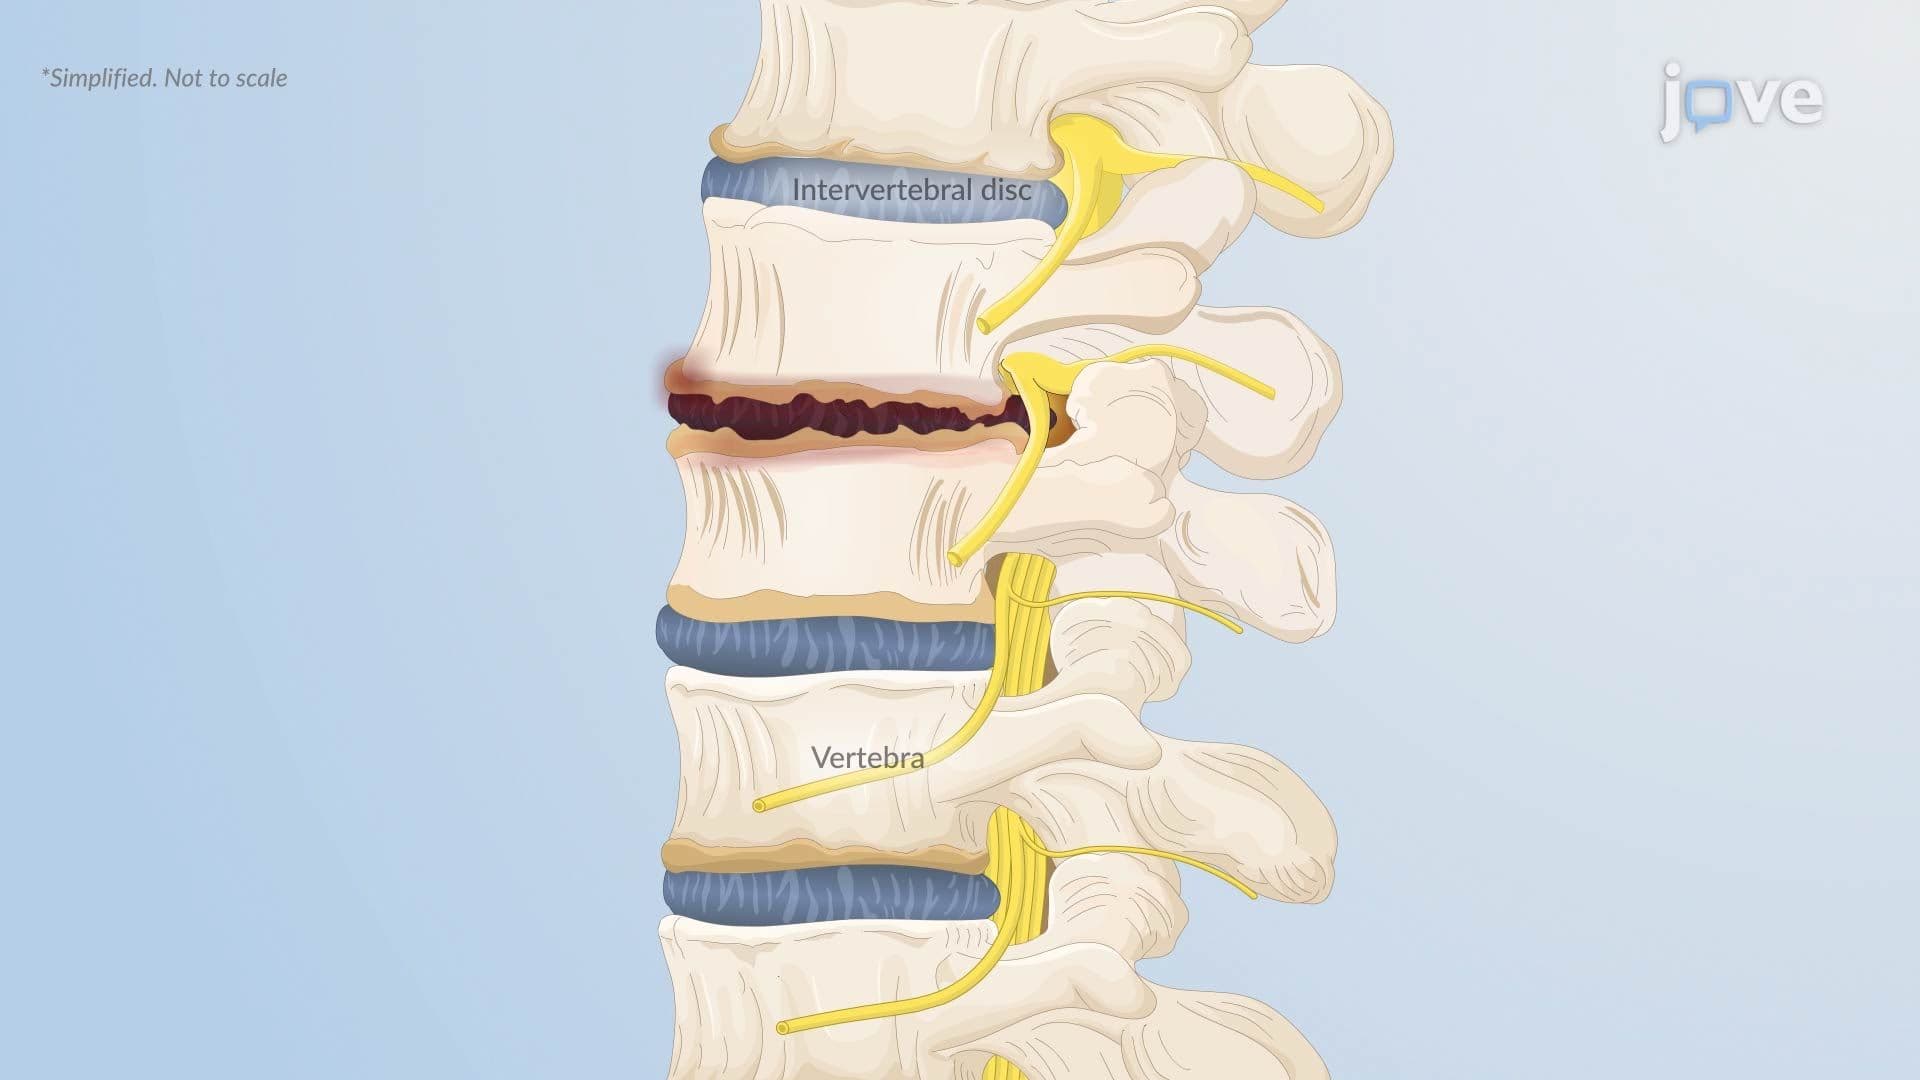
Herniated Intervertebral Disc l: Introduction