Related Experiment Video
Updated: May 8, 2026

Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
How useful are perioperative biochemical parameters in predicting the duration of calcium and/or vitamin D
Brian Hung-Hin Lang1, Kai Pun Wong
1Division of Endocrine Surgery, Department of Surgery, University of Hong Kong, Queen Mary Hospital, 102 Pokfulam Road, Hong Kong SAR, China, blang@hkucc.hku.hk.

Background:
Oral calcium and calcitriol are often prescribed after total thyroidectomy to avoid biochemical and/or symptomatic hypocalcemia. We aimed to identify independent perioperative factors that correlated with the duration of calcium and/or calcitriol supplementation after total thyroidectomy.
Methods:
Of 271 eligible patients, 48 (17.7 %) required calcium and/or calcitriol supplements on discharge. Patients were gradually weaned from the supplementation by one surgeon according to a biweekly algorithm based on serum calcium (Ca). Duration of supplementation was calculated from the date of operation to the date of ceasing all supplementation without biochemical hypocalcemia (i.e., serum adjusted Ca ≥ 8.44 mg/dL). The Cox regression analysis was performed to identify independent perioperative factors for duration of supplementation. The best cut-off value for these independent factors was determined by the receiver characteristic curve.
Results:
In the multivariate analysis, parathyroid hormone (PTH) at skin closure (PTH-SC) (RR 1.742, 95 % CI 1.080-2.810) and on postoperative day 1 adjusted Ca (Ca-D1) (RR 77.526, 95 % CI 3.600-1669.57) were the only two independent determinants for shorter duration before ceasing all supplementation. The best cut-off values in predicting supplementation ≥ 6 months for PTH-SC and Ca-D1 were 7.08 pg/mL (sensitivity = 100 %, specificity = 60.5 %, PPV = 40.0 % and NPV = 100 %) and 7.88 mg/dL (sensitivity = 90.0 %, specificity = 55.3 %, PPV = 34.6 % and NPV = 95.5 %), respectively.
Conclusions:
Both PTH-SC and Ca-D1 were independently associated with the duration of supplementation after total thyroidectomy. Almost all patients with PTH-SC ≥ 7.08 pg/mL or Ca-D1 ≥ 7.88 mg/dL did not require supplementation ≥ 6 months whereas about one third of patients with PTH-SC <7.08 pg/mL or Ca-D1 <7.88 mg/dL required supplementation ≥ 6 months.
Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:21
Skeleton and Calcium Homeostasis
 00:51
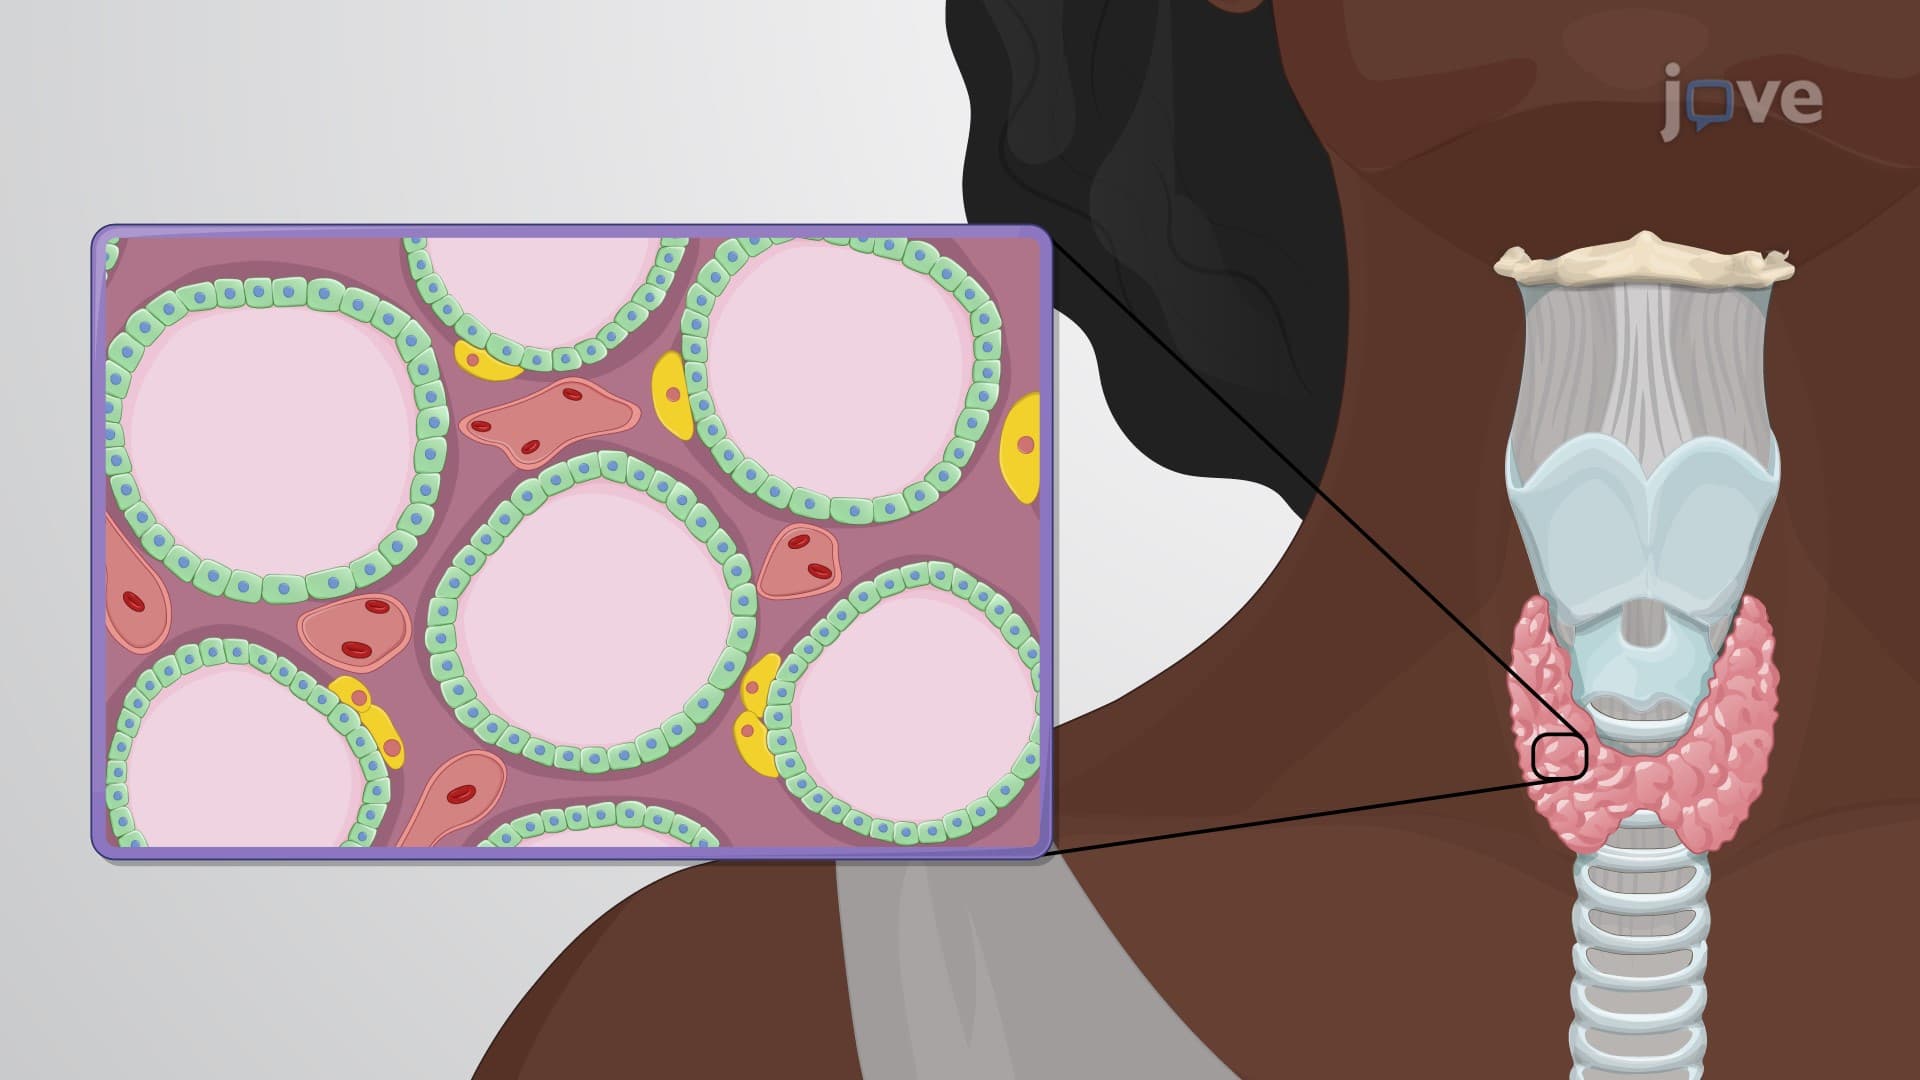
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test