Related Experiment Video
Updated: May 8, 2026


An Ultrasonic Tool for Nerve Conduction Block in Diabetic Rat Models
Published on: October 20, 2017
[Evaluation of neuromuscular blockade using TOF-Watch SX in type 2 diabetes patients]
Hajime Iwasaki1, Kenichi Takahoko, Shigeaki Otomo
1Department of Anesthesiology and Critical Care Medicine, Asahikawa Medical University, Asahikawa 078-8510.

Background:
Differences in the supramaximal current (STIM) and sensitivity of the transducer (SENS) after calibration using mode "CAL2" of the neuromuscular accelermyography (TOF-Watch SX, MSD, Japan) between type 2 diabetic and non-diabetic patients were evaluated undergoing general anesthesia.
Methods:
Thirty four elective surgical patients (20-69 years) were enrolled in this study. We evaluated STIM, SENS, onset time of rocuronium (onset time), time from onset to first T1 appearance (T1 appearance) and time from T1 appearance to T2 appearance (T1-T2 time) by using TOF stimulation between type 2 diabetic patients and non-diabetic patients, retrospectively.
Results:
Thirteen diabetic patients (DM group) and twenty one non-diabetic patients (non-DM group) were included in this analysis. The values of SENS in DM group were significantly higher compared to non-DM patients (207 +/- 59 vs 113 +/- 44). However, STIM did not differ significantly between the two groups. Anesthesia in the 6 patients in DM group (SEV-DM group) and 14 patients in the non-DM group (SEV-non DM group) were maintained with sevoflurane. The other 14 patients were maintained with desflurane (DES-DM: n = 7 and DES-non DM: n = 7). A significant difference in the SENS values only was observed between the two SEV groups. On the other hand, the onset time, T1 appearance and T1-T2 time were significantly longer in DES-DM patients than those in the DES-non DM group.
Conclusions:
It is demonstrated that the values in the SENS and the recovery speed (T1-T2 time) under measuring the degree of neuromuscular blockade by TOF stimulation were significantly higher in diabetic patients compared to non-diabetic patients. The present study provides additional confirmation of low neuromuscular response under peripheral electrical stimulation using TOF-Watch SX in type 2 diabetes patients, and attention should be paid to the evaluation of neuromuscular block using TOF-Watch SX in diabetic patients.

Related Concept Videos
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:17
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
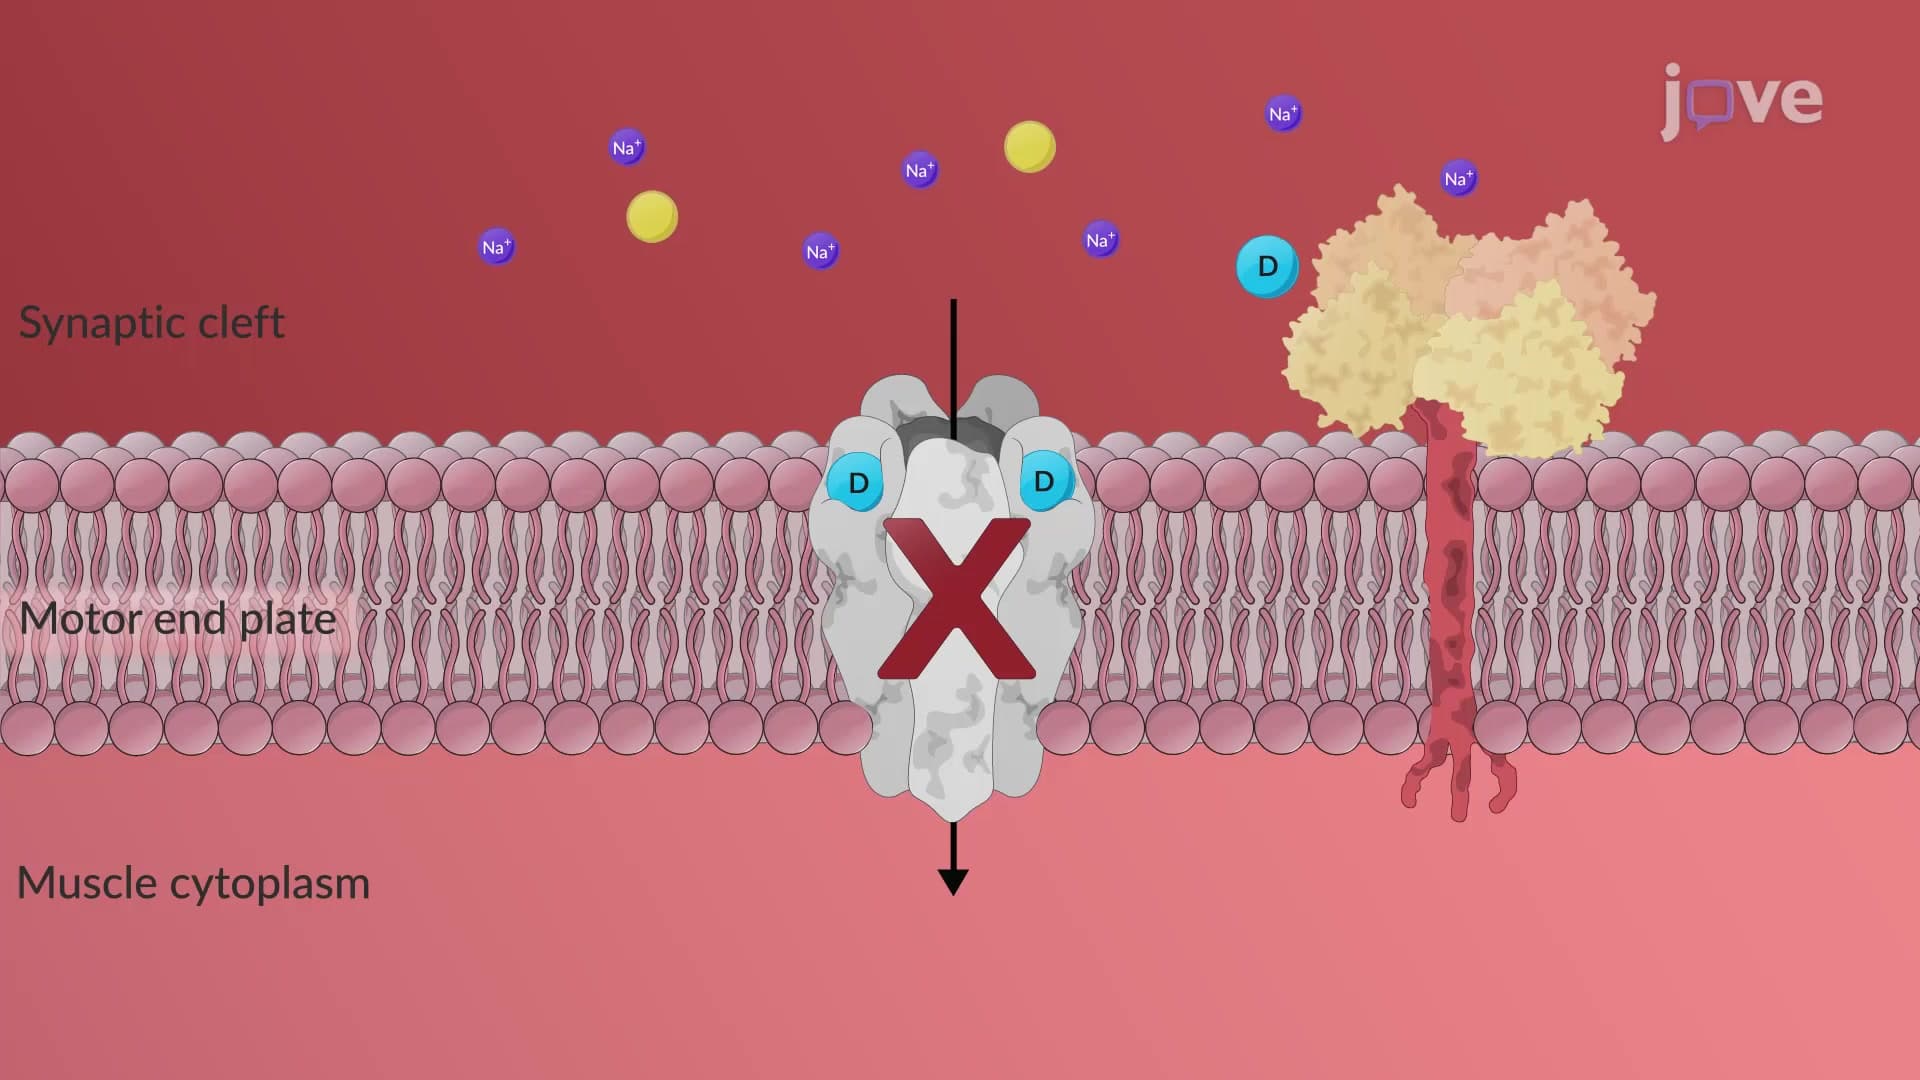
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:29
Neuromuscular Junction And Blockade
 01:22
Diabetic Neuropathy