Conversion to prolonged release tacrolimus formulation in stable kidney transplant recipients
Related Experiment Video
Updated: May 8, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Sheng-Wen Wu1, Hui-Ching Tsai, Pao-Yu Tsai
1The School of Medicine, Chung Shan Medical University, Taichung, Taiwan; s41111.tw@yahoo.com.tw.

Principles:
The once-daily tacrolimus formulation (Advagraf®), with the potential for improving medical adherence, has been advocated to improve long-term kidney allograft outcomes. However, experience with late conversion from the twice-daily tacrolimus formulation (Prograf®) to Advagraf in the daily care of stable kidney transplant recipients has been limited.
Methods:
The aim of this study was to observe the efficacy and safety of conversion from Prograf to Advagraf in chronic stable kidney transplant recipients in routine clinical practice. The recruited patients had postconversion follow-up at least once monthly for a total of six months, unless they had discontinued the use of Advagraf, had been lost the follow-up or had lost the graft.
Results:
The mean age of the 199 patients was 51.5 ± 10.4 years (60.8% male). The mean time from transplantation to the conversion to Advagraf was 8.3 ± 3.2 years and the mean tacrolimus trough level at conversion was 4.2 ± 1.4 ng/ml. After conversion, 147 patients (73.8 %) had a reduced trough level at one month and the mean change in trough level postconversion was -13.5%. The mean serum creatinine level between conversion and six months postconversion was not significantly different (1.12 ± 0.36 vs 1.10 ± 0.42 mg/dl). Thirty-four patients (17%) discontinued the treatment with Advagraf and two (1%) developed biopsy-proved acute rejection.
Conclusions:
In conclusion, frequent conversion caused by a high discontinuation rate may further raise the potential risk of allograft rejection and increase unnecessary cost. In view of this, the policy of converting to Advagraf with the purpose of improving medical adherence should be individualised in routine clinical practice.
Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Kidney Transplant I: Introduction
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:24
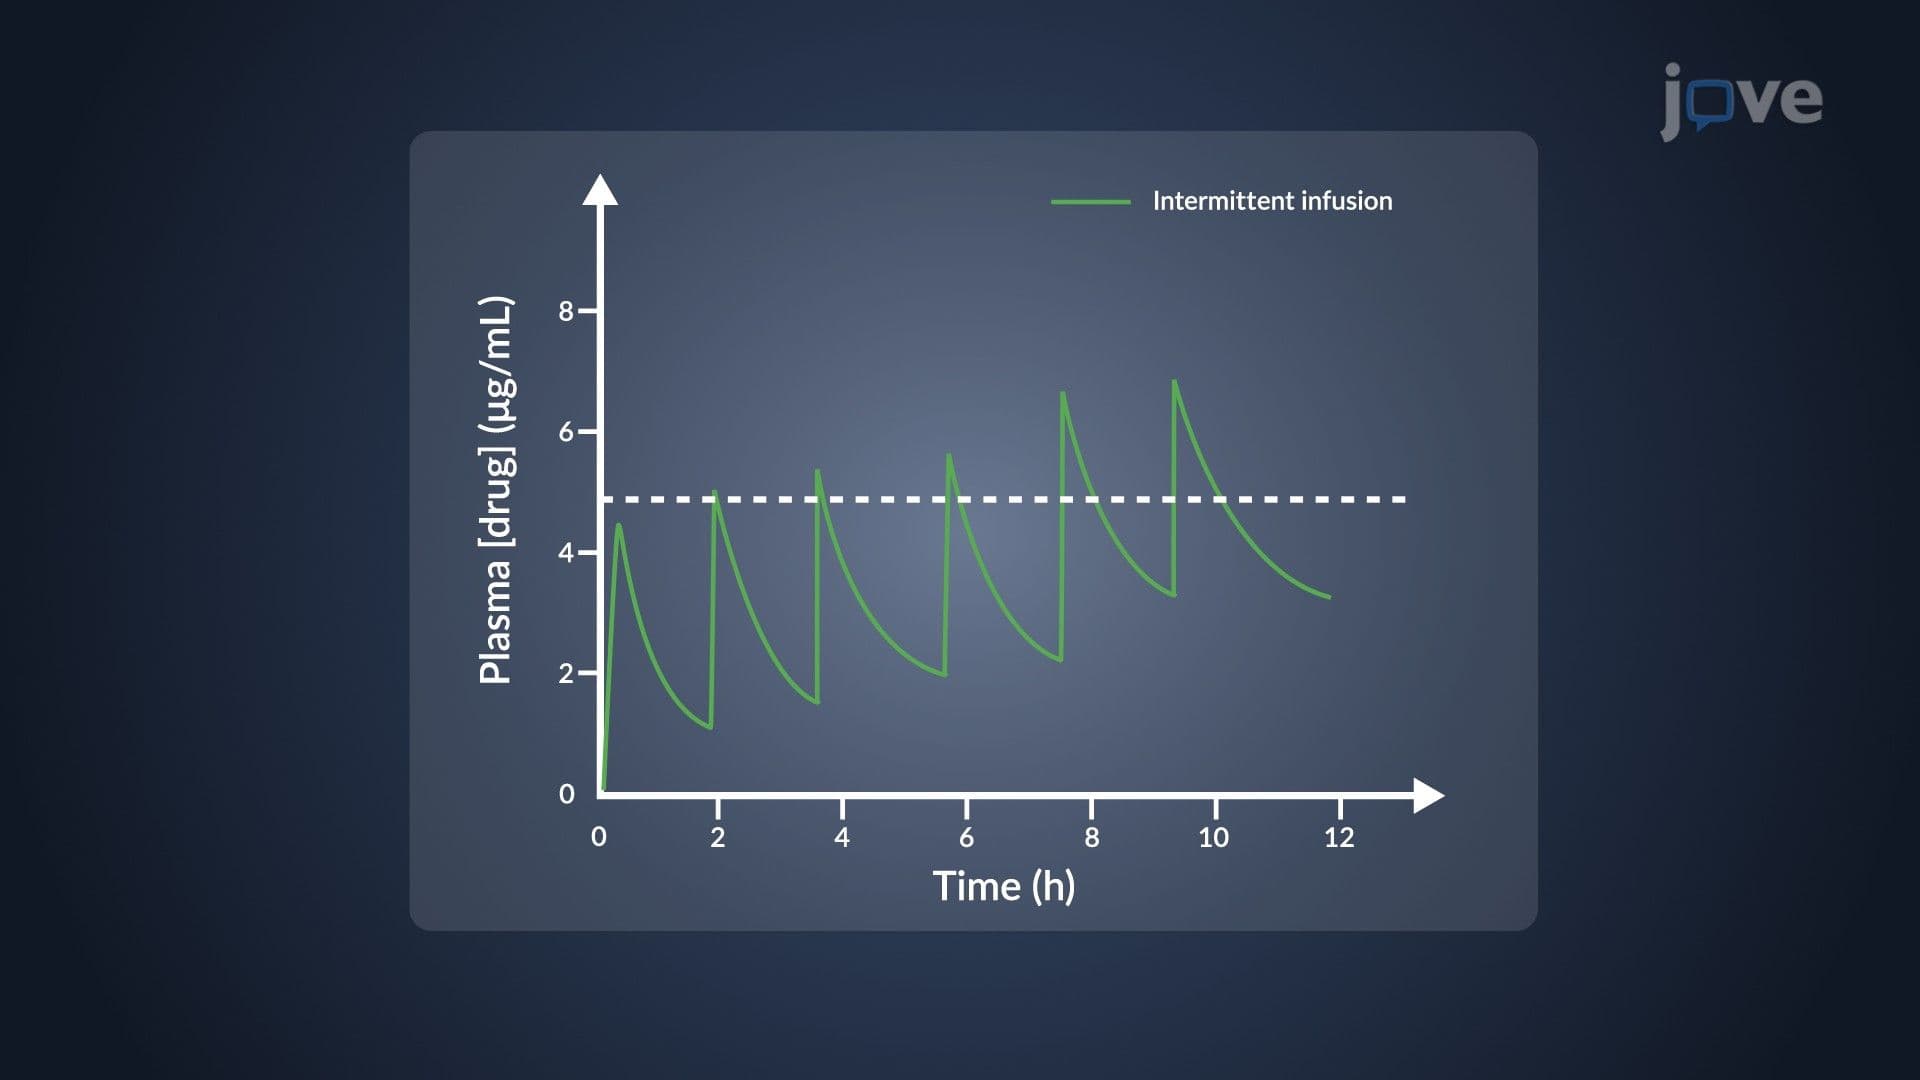
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:16
Kidney Transplant III: Nursing Management
 01:28
Renal Drug Excretion: Tubular Secretion