Related Experiment Video
Updated: May 8, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Bone mineral density in developing children with osteogenesis imperfecta: a longitudinal study with 9 years of
Dieke H J Kok1, Ralph J B Sakkers, Hans E H Pruijs
1Department of Orthopaedic Surgery, Wilhelmina Children's Hospital, University Medical Center Utrecht, the Netherlands. diekekok@tele2.nl

Insights
Bone mineral density (BMD) increased in children with osteogenesis imperfecta (OI) over 9 years, particularly in girls. This suggests potential differences in growth spurts and peak bone mass timing between sexes in OI patients.
Area of Science:
- Pediatric Endocrinology
- Orthopedics
- Genetics
Background:
- Osteogenesis imperfecta (OI) is a genetic disorder affecting collagen type I synthesis, leading to bone fragility, low bone mass, and skeletal deformities in children.
- These bone abnormalities can result in varying degrees of short stature and impact overall skeletal development.
Purpose of the Study:
- To investigate the longitudinal development of bone mineral density (BMD) in a cohort of children diagnosed with osteogenesis imperfecta.
- To identify factors influencing BMD changes over time in pediatric patients with OI.
Main Methods:
- Retrospective analysis of lumbar bone mineral density (BMD) in 74 children with OI, with a mean age of 16.3 years.
- Longitudinal data analysis was performed on 52 children with repeated BMD measurements over a mean follow-up of 9 years.
- Cross-sectional analysis of the latest BMD measurements was conducted for the entire cohort.
Main Results:
- A mean annual increase in BMD of 0.038 g/cm²/year was observed in the longitudinal cohort.
- BMD increase was significantly higher in girls compared to boys, both in unadjusted and adjusted analyses.
- In cross-sectional analysis, higher latest-measured lumbar BMD was associated with being female, having OI type I, being ambulatory (walker), and older age.
Conclusions:
- Children with OI experienced an increase in bone mineral density over a 9-year follow-up period.
- The increase in BMD was more pronounced in girls, potentially due to later growth spurts and peak bone mass attainment in boys.
- Findings highlight sex-based differences in bone density development in pediatric osteogenesis imperfecta.
Background And Purpose:
Osteogenesis imperfecta (OI) is a heritable disorder of connective tissue caused by a defect in collagen type I synthesis. For bone, this includes fragility, low bone mass, and progressive skeletal deformities, which can result in various degrees of short stature. The purpose of this study was to investigate development of bone mineral density in children with OI.
Patients And Methods:
Development of lumbar bone mineral density was studied retrospectively in a cohort of 74 children with OI. Mean age was 16.3 years (SD 4.3). In 52 children, repeated measurements were available. Mean age at the start of measurement was 8.8 years (SD 4.1), and mean follow-up was 9 years (SD 2.7). A longitudinal data analysis was performed. In the total cohort (74 children), a cross-sectional analysis was performed with the latest-measured BMD. Age at the latest BMD measurement was almost equal for girls and boys: 17.4 and 17.7 years respectively.
Result:
Mean annual increase in BMD in the 52 children was 0.038 g/cm(2)/year (SD 0.024). Annual increase in BMD was statistically significantly higher in girls, in both the unadjusted and adjusted analysis. In cross-sectional analysis, in the whole cohort the latest-measured lumbar BMD was significantly higher in girls, in the children with OI of type I, in walkers, and in those who were older, in both unadjusted and adjusted analysis.
Interpretation:
During 9 years of follow-up, there appeared to be an increase in bone mineral density, which was most pronounced in girls. One possible explanation might be a later growth spurt and older age at peak bone mass in boys.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into...
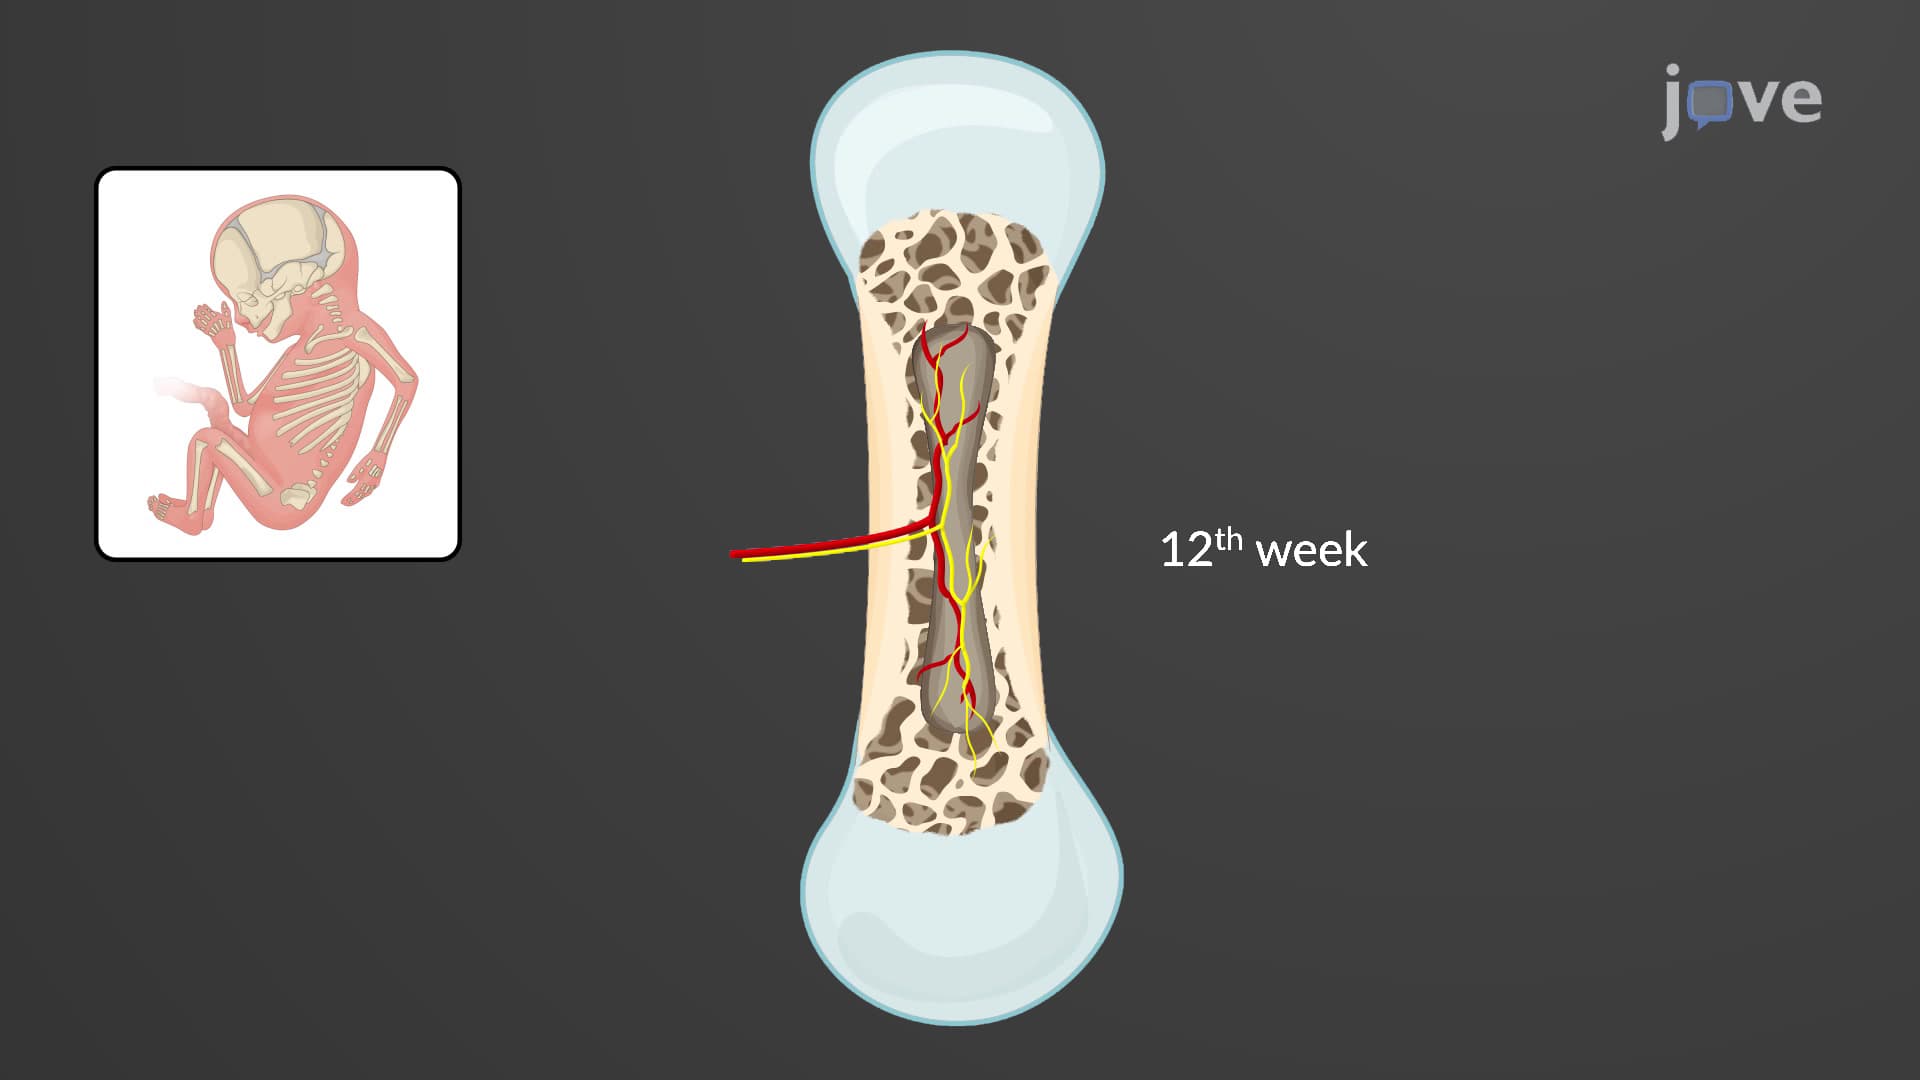 01:24
Bone Formation by Endochondral Ossification
 01:40
Bone Remodeling
 01:31
Bone Remodeling and Repair