Related Experiment Video
Updated: May 8, 2026


Ear Plaster Therapy as a Safe and Effective Treatment for Gestational Vomiting
Published on: August 4, 2023
Successful discharge of children with gastroenteritis requiring intravenous rehydration
Stephen B Freedman1, Julie M DeGroot2, Patricia C Parkin3
1Division of Paediatric Emergency Medicine and Division of Gastroenterology, Hepatology and Nutrition, Department of Paediatrics, The Hospital for Sick Children, Toronto, Ontario, Canada; Child Health Evaluative Sciences, The Hospital for Sick Children Research Institute, Faculty of Medicine, University of Toronto, Toronto, Ontario, Canada.

Insights
Higher serum bicarbonate levels in children treated for gastroenteritis with intravenous rehydration are linked to increased emergency department revisits. However, bicarbonate is not associated with successful discharge outcomes.
Area of Science:
- Pediatrics
- Emergency Medicine
- Gastroenterology
Background:
- Emergency Department (ED) revisits are a significant concern for children with gastroenteritis receiving intravenous rehydration.
- Identifying predictors of revisits can improve patient management and reduce healthcare utilization.
Purpose of the Study:
- To investigate the association between serum bicarbonate levels and ED revisits in pediatric patients with gastroenteritis.
- To determine if bicarbonate predicts successful discharge after intravenous rehydration.
Main Methods:
- Secondary analysis of prospectively collected data from children over 3 months old with gastroenteritis treated with intravenous fluids.
- Regression analysis was used to assess bicarbonate's predictive value for 7-day revisits and successful discharge.
- Successful discharge was defined as discharge from the index visit without a revisit requiring intravenous rehydration.
Main Results:
- Of 174 discharged children, 18% experienced a revisit. Higher baseline bicarbonate was a predictor of revisits (OR 1.1, p=0.03).
- Absence of a primary care provider and ondansetron administration also predicted revisits.
- Bicarbonate levels were not associated with successful discharge, but higher fluid volumes and dehydration scores negatively predicted it.
Conclusions:
- Serum bicarbonate levels are associated with ED revisits in children with gastroenteritis requiring intravenous rehydration.
- Lower bicarbonate values were not linked to unfavorable outcomes post-discharge.
Background:
Emergency Department (ED) revisits are very common in children with gastroenteritis administered intravenous rehydration.
Study Objectives:
To determine if bicarbonate values are associated with ED revisits in children with gastroenteritis.
Methods:
We conducted a secondary analysis of prospectively collected data, which included children >3 months of age with gastroenteritis treated with intravenous rehydration. Regression analysis was employed to determine whether, among discharged children, bicarbonate independently predicts revisits within 7 days (primary outcome) and successful discharge (secondary outcome). The latter composite outcome measure was defined as discharge at the index visit and the absence of a revisit requiring intravenous rehydration.
Results:
Of 226 potentially eligible children, 174 were discharged and were included in the primary outcome analysis. Of the eligible children, 18% (30/174) had a revisit that was predicted by a higher baseline bicarbonate (odds ratio [OR] 1.1; 95% confidence interval [CI] 1.0-1.3; p = 0.03), absence of a primary care provider (OR 7.8; 95% CI 1.2-51.0; p = 0.03), and ondansetron administration (OR 2.4; 95% CI 1.0-5.5; p = 0.05). Bicarbonate was not associated with successful discharge. Negatively associated independent predictors of successful discharge were volume of intravenous fluids administered (OR 0.84/10 mL/kg increase; 95% CI 0.76-0.93; p < 0.001), and baseline clinical dehydration score (OR 0.75/unit increase; 95% CI 0.58-0.97; p < 0.001). Revisits requiring intravenous rehydration and hospitalization were associated with higher bicarbonate values (21.2 ± 4.6 mEq, p = 0.001, and 22.3 ± 5.0 mEq/L, p < 0.001, respectively).
Conclusion:
Lower serum bicarbonate values at the time of intravenous rehydration are not associated with unfavorable outcomes after discharge.
Related Concept Videos
 01:30
Acute Pharyngitis
Acute pharyngitis is the inflammation of the back of the throat (pharynx), commonly resulting in a sore throat. It is a frequently encountered condition that prompts individuals to seek medical advice.
Classification
Acute pharyngitis can be categorized based on its underlying cause:
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:14
Prevention of Further Absorption of Poison
 01:17
Urinary Tract Infection IV: Nursing Management
 01:18
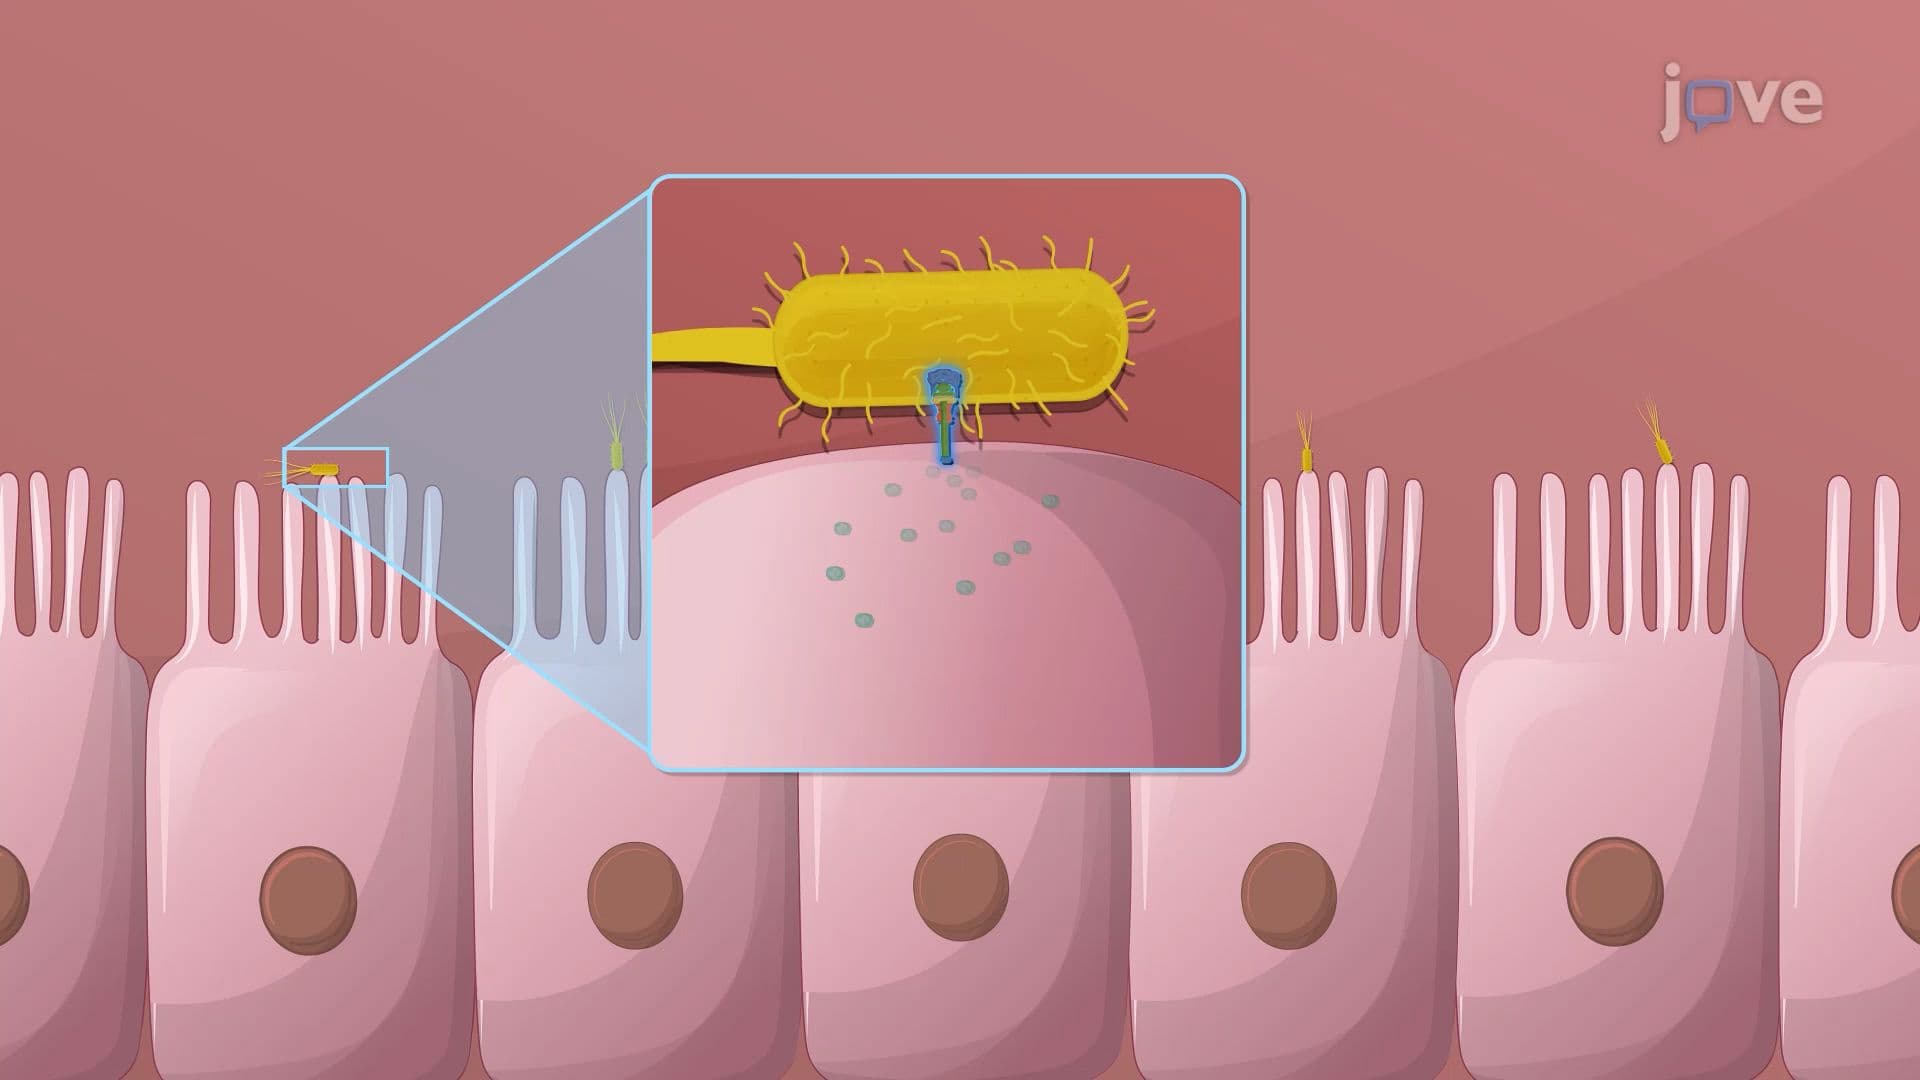
Bacterial Gastroenteritis
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...