Related Experiment Video
Updated: May 8, 2026
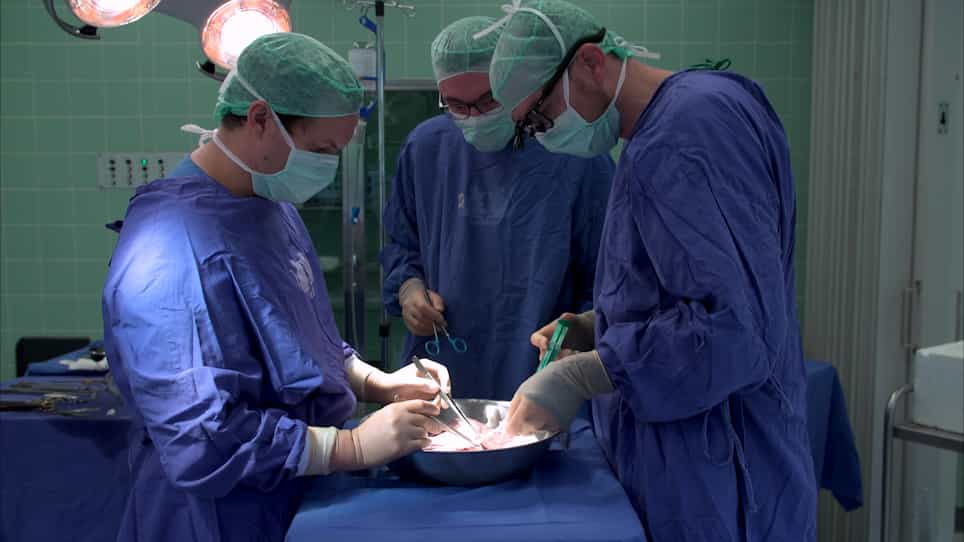
Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Predictive factors for pediatric patients requiring massive blood transfusion during living donor liver
Chia-Jung Huang1, Kwok-Wai Cheng, Chao-Long Chen
1Anesthesiology, Kaohsiung Chang Gung Memorial Hospital, Chang Gung University College of Medicine, Kaohsiung, Taiwan.

Background:
The aim of this study was to identify the preoperative risk factors that may predict the requirement of massive blood transfusion during pediatric living donor liver transplantation.
Material And Methods:
The anesthesia charts of pediatric patients undergoing living donor liver transplantation were reviewed retrospectively. Patients were grouped into 2 categories based on the amount of intraoperative blood transfusion. Group I (GI) consists of patients who received massive blood transfusion and Group II (GII) consists of patients who did not receive massive blood transfusion. The patients' characteristics and preoperative data were compared between groups with the Mann-Whitney U test. Predictive risk factors for massive blood transfusion were analyzed by binary regression. A p value of <0.05 was regarded as significant. Data are given as mean ±SD.
Results:
A total of 198 pediatric patients were included in this study. Thirteen (6.5%) of the 198 pediatric patients undergoing living donor liver transplantation met the criteria of massive blood transfusion. The mean estimated blood volume of GI and GII was 724±322 and 1097±830 ml, respectively. The mean quantity of blood products given were 1018±591 and 187±220 ml for GI and GII, respectively. RBC was given to 67% of the patients, FFP was given to 18%, and only 1% received platelet transfusion. The patients who required massive blood transfusion were younger in age and had smaller body size, with prolonged INR (international normalized ratio) observed. INR, a measure of blood clotting time, was the only predictive factor that can impact intraoperative massive blood loss and subsequent blood transfusion. Each prolongation of 0.1 unit of INR elevates by 1.083-fold the risk of massive blood transfusion (95% C.I.=1.030-1.139, P=0.002).
Conclusions:
Preoperative INR was the only predictive risk factor for massive blood transfusion during pediatric living donor liver transplantation. Increasing the ratio of FFP transfusion in patients with prolonged INR before or during pediatric LDLT is recommended.
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...
 01:26
Kidney Transplant II: Surgical Procedure
 01:15
Blood Transfusion
Blood Transfusion Overview
A blood transfusion is a medical procedure used to replace blood lost due to injury, surgery, or to treat conditions such as anemia or cancer. During a transfusion, donor blood is...
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...