Related Experiment Video
Updated: May 8, 2026


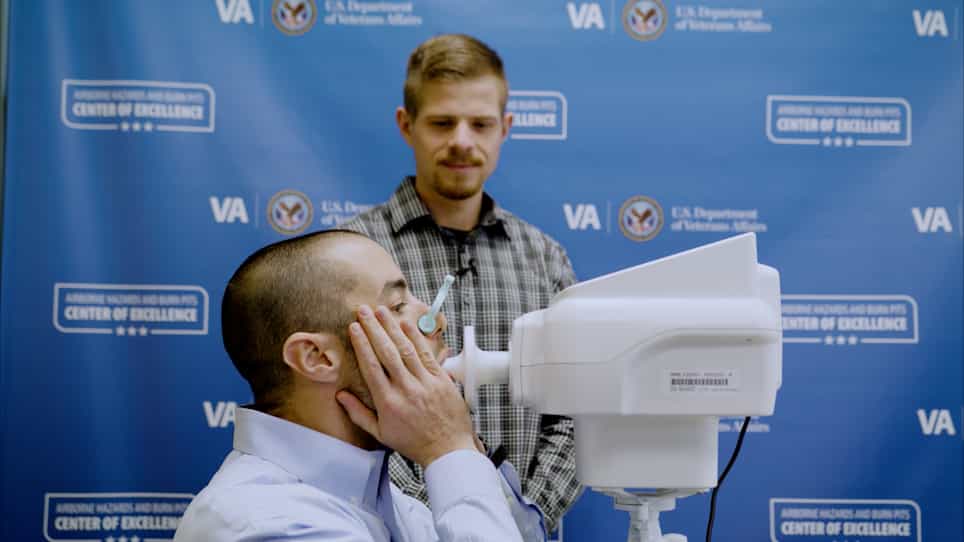
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Spirometry use in children hospitalized with asthma
Chee Chun Tan1, Karen M McDowell, Matthew Fenchel
1Cincinnati Children's Hospital Medical Center, Cincinnati, Ohio.

Insights
Few hospitalized children with asthma underwent recommended spirometry. Lower lung function and prior healthcare use were linked to repeat asthma exacerbations, but spirometry
Area of Science:
- Pediatric Pulmonology
- Asthma Management
- Respiratory Medicine
Background:
- Asthma is a leading cause of childhood hospital admissions.
- National Asthma Education and Prevention Program (NAEPP) guidelines recommend spirometry during hospitalization for asthma.
- The utility of pre-discharge spirometry in pediatric asthma patients requires further investigation.
Purpose of the Study:
- To describe spirometry use in children hospitalized with asthma.
- To determine the association between pulmonary function and future asthma exacerbations.
Main Methods:
- Retrospective cohort study of children (≥5 years) hospitalized with asthma.
- Reviewed medical records for spirometry performance and asthma re-exacerbations within 3 months.
- Analyzed spirometry parameters including forced expiratory volume in 1 second (FEV1) and forced vital capacity (FVC).
Main Results:
- Only 8.6% of 1,037 admissions had recommended spirometry, often performed by specialists before discharge.
- Acceptable spirometry was achieved by 54.9% of those tested, with older children more likely to perform it.
- Lower FEV1/FVC and FEF25-75 were associated with re-exacerbations, but this association was not significant after adjusting for age and length of stay.
Conclusions:
- Spirometry use in hospitalized pediatric asthma patients often falls short of NAEPP guidelines.
- Lower lung function and prior healthcare utilization are associated with repeat asthma exacerbations.
- The clinical value of routine pre-discharge spirometry in pediatric asthma patients remains uncertain.
Abstract:
Asthma is the most common chronic disorder of childhood and continues to be a leading cause of pediatric hospital admission. The National Asthma Education and Prevention Program (NAEPP) recommends that spirometry be obtained for asthma patients upon hospital admission, after bronchodilation during the acute phase of asthma symptoms, and at least one additional time before discharge from the hospital. The objectives of this study were to describe the use of spirometry in children hospitalized with asthma and to determine association of pulmonary function with future exacerbations. A retrospective cohort study design was utilized involving review of medical records of children ≥5 years old admitted with asthma to Cincinnati Children's Hospital Medical Center from September 1, 2009 to March 31, 2011. Hospitalization or emergency department (ED) visits were identified by the ICD-9-CM codes of having either a primary diagnosis of asthma (493) or a respiratory illness (460-496) plus a secondary diagnosis of asthma. Asthma re-exacerbation was defined as either having an ED visit or hospitalization for asthma that occurred within 3 months after the index hospitalization. All spirometries were performed in a pediatric pulmonary function laboratory. Among 1,037 admissions included in this study, 89 (8.6%) had spirometry that was recommended by a consulting asthma specialist and usually performed on the day of discharge. Spirometries for forty-five of these patients (54.9%) met all acceptability and repeatability criteria of the American Thoracic Society. Patients who performed acceptable spirometry were significantly older (12.4 ± 3.8 vs. 10.7 ± 3.0 years; P = 0.041). The average forced expiratory volume in the first second (FEV1 ) was 84.4 ± 19.7% predicted; forced vital capacity (FVC) was 98.1 ± 16.0% predicted; FEV1 /FVC was 74.6 ± 9.6%; forced expiratory flow at 25-75% (FEF25-75 ) was 61.2 ± 30.1% predicted. Ten patients (22%) who performed spirometry developed a re-exacerbation. Patients with versus without re-exacerbation had significantly lower FEV1 /FVC (P = 0.027) and FEF25-75 (P = 0.031). Nevertheless, separate logistic regression models found that FEV1 /FVC and FEF25-75 were not associated with re-exacerbation when adjusted for age and length-of-stay. We found that few children admitted with asthma had spirometry as recommended in the NAEPP guidelines unless recommended by specialists and both lower lung function (FEV1 /FVC and FEF25-75 ) and history of more frequent and more recent prior health-care utilization for asthma were associated with repeat asthma exacerbation. However, the value of performing spirometry on asthmatic children prior to hospital discharge remains unclear and will require prospective study.

Related Concept Videos
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:23
Inhaled Medications
 01:26
COPD: Management Using Bronchodilators and Corticosteroids