Related Experiment Video
Updated: May 8, 2026
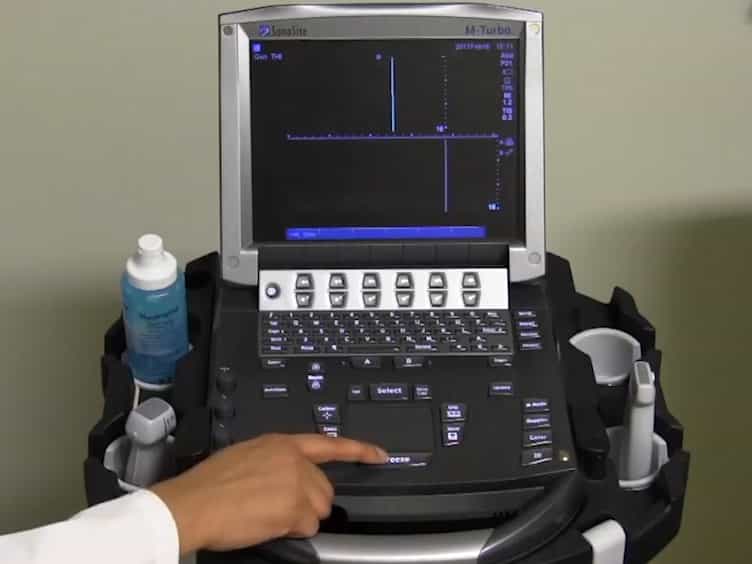

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Improving the predictive accuracy of identifying exudative effusions
Carlos E Kummerfeldt1, Cody C Chiuzan2, John T Huggins1
1Division of Pulmonary, Critical Care, Allergy, and Sleep Medicine.

Background:
Application of Light's criteria results in misclassification of some transudative effusions as exudative, particularly because of congestive heart failure (CHF). We sought to determine if the serum to pleural fluid albumin (SF-A) and serum to pleural fluid protein (SF-P) gradients increased the predictive accuracy to correctly identify exudative effusions.
Methods:
We retrospectively analyzed 1,153 consecutive patients who underwent a diagnostic thoracentesis at the Medical University South Carolina. Univariable logistic regression analyses were used to determine the statistical significance of pleural fluid tests that correctly identified exudative effusions. Tests with significant diagnostic accuracy were combined in multivariable logistic regression models, with calculation of areas under the curve (AUCs) to determine their predictive accuracy. The predictive capability of the best model was compared with Light's criteria and other test combinations.
Results:
Pleural fluid lactate dehydrogenase (LDH), SF-A gradient, and SF-P gradient had a significant effect on the probability of identifying exudative pleural effusions. When combined together in a multivariable logistic regression, LDH (OR, 14.09 [95% CI, 2.25-85.50]), SF-A gradient (OR, 7.16 [95% CI, 1.24-41.43]), and SF-P gradient (OR, 6.83 [95% CI, 1.56-27.88]) had an AUC of 0.92 (95% CI, 0.85-0.98).
Conclusions:
Application of Light's criteria, not uncommonly, misclassifies CHF transudative effusions as exudates. In cases where no cause for an exudative effusion can be identified or CHF is suspected, the sequential application of the fluid LDH, followed by the SF-P and then the SF-A gradients, may assist in reclassifying pleural effusions as transudates.

Related Concept Videos
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:24
Inflammatory Response II: Inflammatory Exudate and Tissue Repair
The typical wound exudate is odorless, transparent, straw-colored, thin, and watery. Exudate, however, can differ depending on the state of wound healing. Likewise, the exudate's...