Related Experiment Video
Updated: May 8, 2026
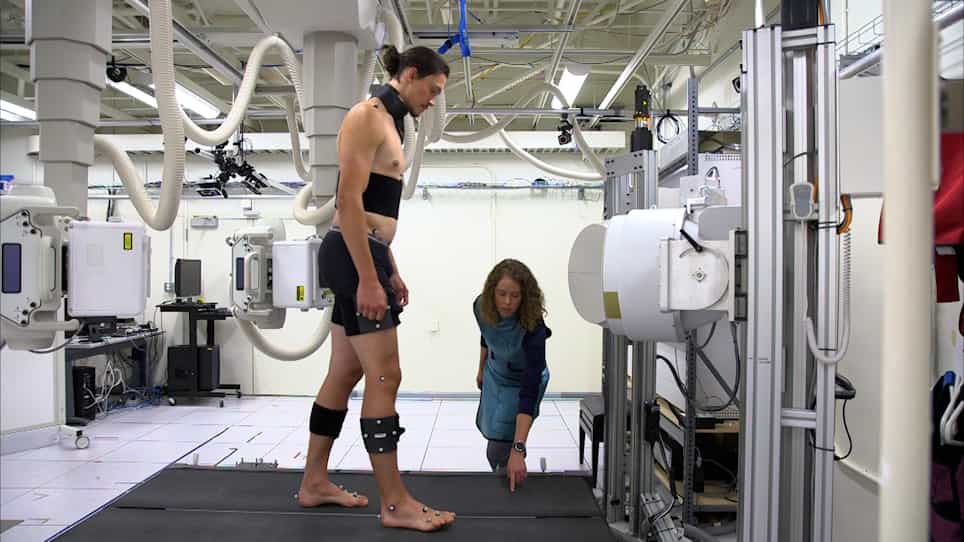
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Is hospital teaching status a key factor in hospital charge for children with hip fractures?: preliminary findings

Insights
Hospital teaching status does not significantly impact length of stay or total hospital costs for pediatric proximal femur fracture surgery. Further research is needed to identify cost and length of stay variation factors.
Area of Science:
- Orthopedic Surgery
- Pediatric Healthcare
- Health Economics
Background:
- Proximal femur fractures in children lead to substantial pain and healthcare expenses.
- Understanding cost and length of stay variations is crucial for optimizing pediatric orthopedic care.
Purpose of the Study:
- To analyze the distribution of pediatric hip fracture patients across U.S. teaching and non-teaching hospitals.
- To determine if hospital teaching status influences mean hospital charges and length of stay for pediatric hip fractures, using propensity score methods to mitigate bias.
Main Methods:
- Utilized the 2006 Healthcare Cost and Utilization Project (HCUP) Kids' Inpatient Database (KID).
- Included pediatric patients (up to 20 years) with principal hip fracture diagnoses (ICD-9 codes 820.0, 820.2, 820.8) and internal fixation procedures.
- Employed propensity score analysis to compare mean hospital charges and length of stay between teaching and non-teaching hospitals.
Main Results:
- Analyzed 1,827 pediatric patients; 76.2% treated at teaching hospitals, 23.8% at non-teaching hospitals.
- Propensity score adjustment revealed no significant differences in mean hospital charges ($34,779 vs. $32,891, p=0.2940) or length of stay (4.1 vs. 3.89 days, p=0.4220) based on teaching status.
Conclusions:
- Hospital teaching status does not significantly affect length of stay or total hospital costs for surgically treated pediatric proximal femur fractures.
- Future research should focus on identifying specific factors contributing to variations in hospital charges and length of stay.
Objective:
Proximal femur fractures cause significant pain and economic cost among pediatric patients. The purposes of this study were (a) to evaluate the distribution by hospital type (teaching hospital vs non-teaching hospital) of U.S. pediatric patients aged 1-20 years who were hospitalized with a closed hip fracture and (b) to discern the mean hospital charge and hospital length of stay after employing propensity score to reduce selection bias.
Methods:
The 2006 Healthcare Cost and Utilization Project (HCUP) Kids' Inpatient Database (KID) was queried for children aged up to 20 years that had principle diagnosis of hip fracture injury. Hip fractures were defined by International Classification of Diseases, 9th Revision, Clinical Modification codes 820.0, 820.2 and 820.8 under Section "Injury and Poisoning (800-999)" with principle internal fixation procedure codes 78.55, 79.15 and 79.35. Patient demographics and hospital status were presented and analyzed. Differences in mean hospital charge and hospital length of stay by hospital teaching status were assessed via two propensity score based methods.
Results:
In total, 1,827 patients were nation-ally included for analysis: 1,392 (76.2%) were treated at a teaching hospital and 435 (23.8%) were treated at a non-teaching hospital. The average age of the patients was 12.88 years old in teaching hospitals vs 14.33 years old in nonteaching hospitals. The propensity score based adjustment method showed mean hospital charge was $34,779 in teaching hospitals and $32,891 in the non-teaching hospitals, but these differences were not significant (p=0.2940). Likewise, mean length of hospital stay was 4.1 days in teaching hospitals and 3.89 days in non-teaching hospitals, but these differences were also not significant (p=0.4220).
Conclusions:
Hospital teaching status did not affect length of stay or total hospital costs in children treated surgically for proximal femur fractures. Future research should be directed at identifying factors associated with variations in hospital charge and length of stay.
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:28
Hospitals-I
 00:59
Hospitals-II
Nurses that work in hospitals have...