Related Experiment Video
Updated: Aug 12, 2026
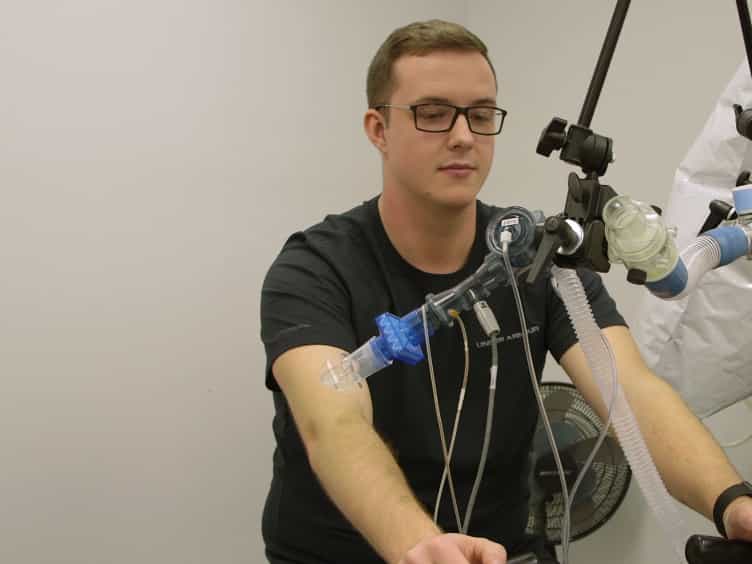

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Changes in airflow obstruction and oxygen saturation in response to exercise and bronchodilators in cystic fibrosis
1Respiratory Unit, Royal Liverpool Children's Hospital Alder Hey, England.

Abstract:
The airway response to exercise and inhaled terbutaline was assessed in 25 patients with cystic fibrosis (CF), seeking evidence for the possible deleterious effects of bronchial muscle relaxation. We postulated that "early" and "late" flows, taken from the full maximum expiratory flow volume curve, might move paradoxically in patients with unstable airways. Oxygen saturation was measured continuously; desaturation occurred early in exercise with partial recovery thereafter. This was unrelated to changes in expiratory airflow measurements. Both during and after exercise, and after inhaled bronchodilator, changes in expiratory airflow measurements were strikingly variable. Changes in individual measurements should be interpreted in relationship to the within-subject variability of the test in patients with CF. During exercise, there was a significant increase in mean FEV1; this was most marked in patients with worst lung function. Two patients (both with severe lung disease) showed paradoxical changes in early and late flows. After exercise, only two patients showed the asthmatic pattern of postexercise bronchoconstriction. After inhaled bronchodilator, the group as a whole showed small but statistically significant increases in expiratory airflow measurements. Those with highest baseline FEV1 had the greatest bronchodilator response; this is the opposite of the pattern observed in asthma. Paradox did not occur after bronchodilators and only one patient showed a significant fall in late expiratory airflow. This pattern of expiratory airflow changes is compatible with the concept of airway instability in which any beneficial effects of bronchial tone reduction are canceled out by the effects of compression of damaged airways rendered more compliant by loss of bronchial wall tone. We did not observe any clinically important deleterious effects from this mechanism.
More Related Videos


Related Concept Videos
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic sinusitis...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features