Supine or prone percutaneous nephrolithotomy: do anatomical changes make it worse?
Related Experiment Video
Updated: May 7, 2026
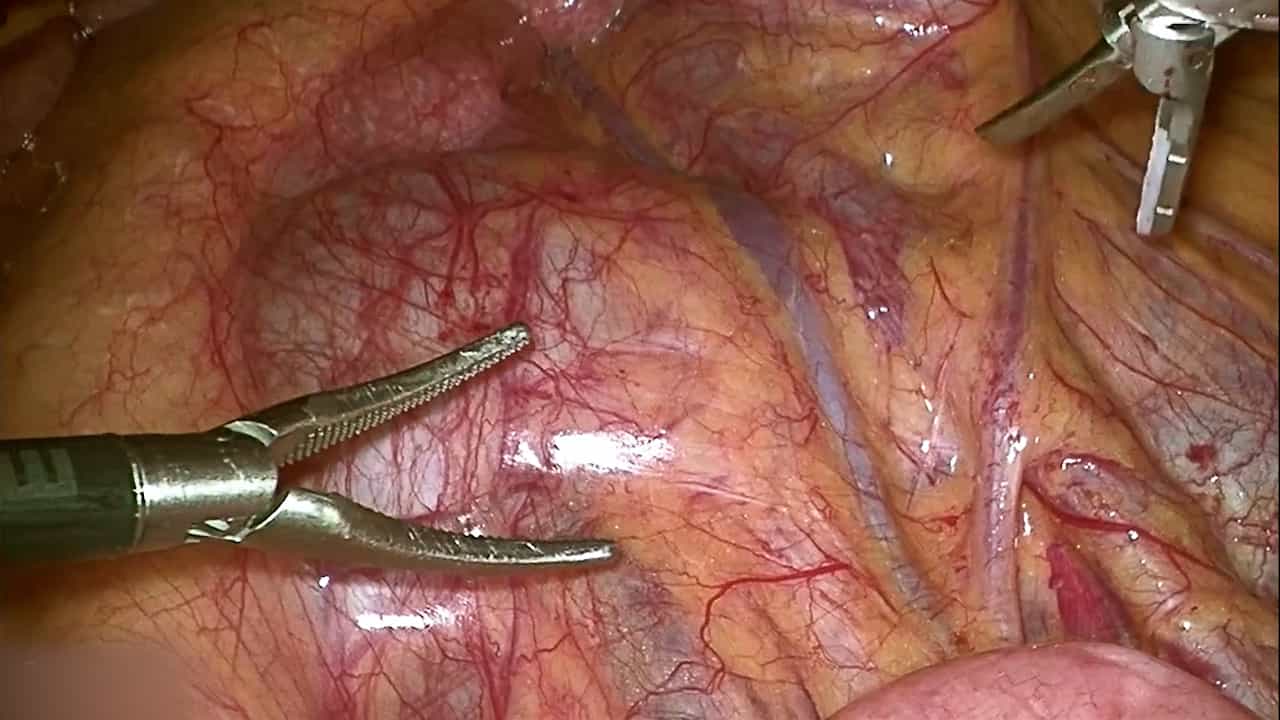
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
Cenk Murat Yazici1, Arda Kayhan, Cagri Dogan
11 Department of Urology, School of Medicine, Namik Kemal University , Tekirdag, Turkey .

Purpose:
To evaluate the different anatomical properties and determine the risk of visceral organ injury in supine, prone, and prone-flex positions.
Materials And Methods:
A total of 30 patients with renal stones >2 cm were included. A dose reduced abdominopelvic tomography in a supine, prone, and 30° prone-flex position was performed. The access tract length, subcutaneous tissue length, nearest organ distance, maximum access angle, access field, and the degree of renal displacement were measured in axial and coronal images. The parameters were analyzed by the paired t-test and Wilcoxon signed test according to normalcy analysis.
Results:
The mean tract lengths and the subcutaneous fat tissue lengths in the lower, middle, and upper poles of kidney were significantly longer in the supine position. The significance of access tract lengths had disappeared when we subtracted the subcutaneous fat tissue length from the whole tract length, exhibiting that the main determinant of tract length was subcutaneous tissue thickness. The maximum access angles were 96.7±22.0°, 94.2±23.6°, and 89.1±23.9° in the supine, prone, and prone-flex position, respectively (p>0.05). The access field was shorter in the supine (80.8±13.3 mm) than prone (86.3±15.0 mm) and prone-flex (86.7±18.4 mm) position (p<0.001). The nearest organ distance to access tract was similar between the supine and prone position in every pole of kidney.
Conclusions:
The anatomical changes related to supine positioning does not increase the risk of percutaneous nephrolithotomy (PCNL) complications. Although supine PCNL may have some benefits over prone PCNL, there will also be some technical difficulties related to the surgeon's manipulations, which are related with the longer access tract and more limited access field.
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:30
Urinary Tract Calculi III: Medical Management