Related Experiment Video
Updated: May 7, 2026

Simultaneous Laryngopharyngeal and Conventional Esophageal pH Monitoring
Published on: December 14, 2020
Anatomophysiology of the pharyngo-upper esophageal area in light of high-resolution manometry

Introduction:
The motility of the pharynx, upper esophageal sphincter (UES), and proximal esophagus is still poorly understood. These structures have anatomical and functional peculiarities that hinder the accurate study of their motility with the technology traditionally available. High-resolution manometry (HRM) has characteristics that make it more suitable for the study of the upper digestive tract. This study aims to evaluate in healthy volunteers, using HRM and transnasal pharyngoscopy, (1) the correlation between anatomical landmarks and HRM plots and (2) the normal values for manometric parameters of the pharynx, UES, and proximal esophagus.
Methods:
We studied 40 asymptomatic volunteers with HRM (50 % male; median age, 27 years). Fourteen of those also underwent transnasal pharyngoscopy.
Results And Discussion:
Pharyngeal peak pressure, rise time, recovery time, and duration of contraction were 128 mmHg (range, 100–164 mmHg), 197 ms (range, 169–268 ms), 385 ms (range, 285–465 ms), and 604 ms (range, 544–626 ms) at the velum and 116 mmHg (range, 97–139 mmHg), 128 ms (range, 100–156 ms), 194 ms (range, 148–219 ms), and 336 ms (range, 267–386 ms) at the epiglottis, respectively. UES extension, basal pressure, residual pressure, and duration of relaxation were 3 cm (range, 2.6–3.6 cm), 76 mmHg (range, 58–109 mmHg), 4.4 mmHg (range, 1.2–6.9 mmHg), and 678 ms (range, 636–757 ms), respectively. In the proximal esophagus, wave amplitudes at 2, 4, and 6 cm below the UES were 72 mmHg (range, 53–97 mmHg), 56 mmHg (range, 42–76 mmHg), and 48 mmHg (range, 35–59 mmHg), respectively.
Conclusions:
In conclusion, normal values were established. These values may prove clinically useful and could contribute to future studies with dysphagic patients.
Related Concept Videos
 01:24
Esophagus
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
 01:27
Esophageal Achalasia
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:25
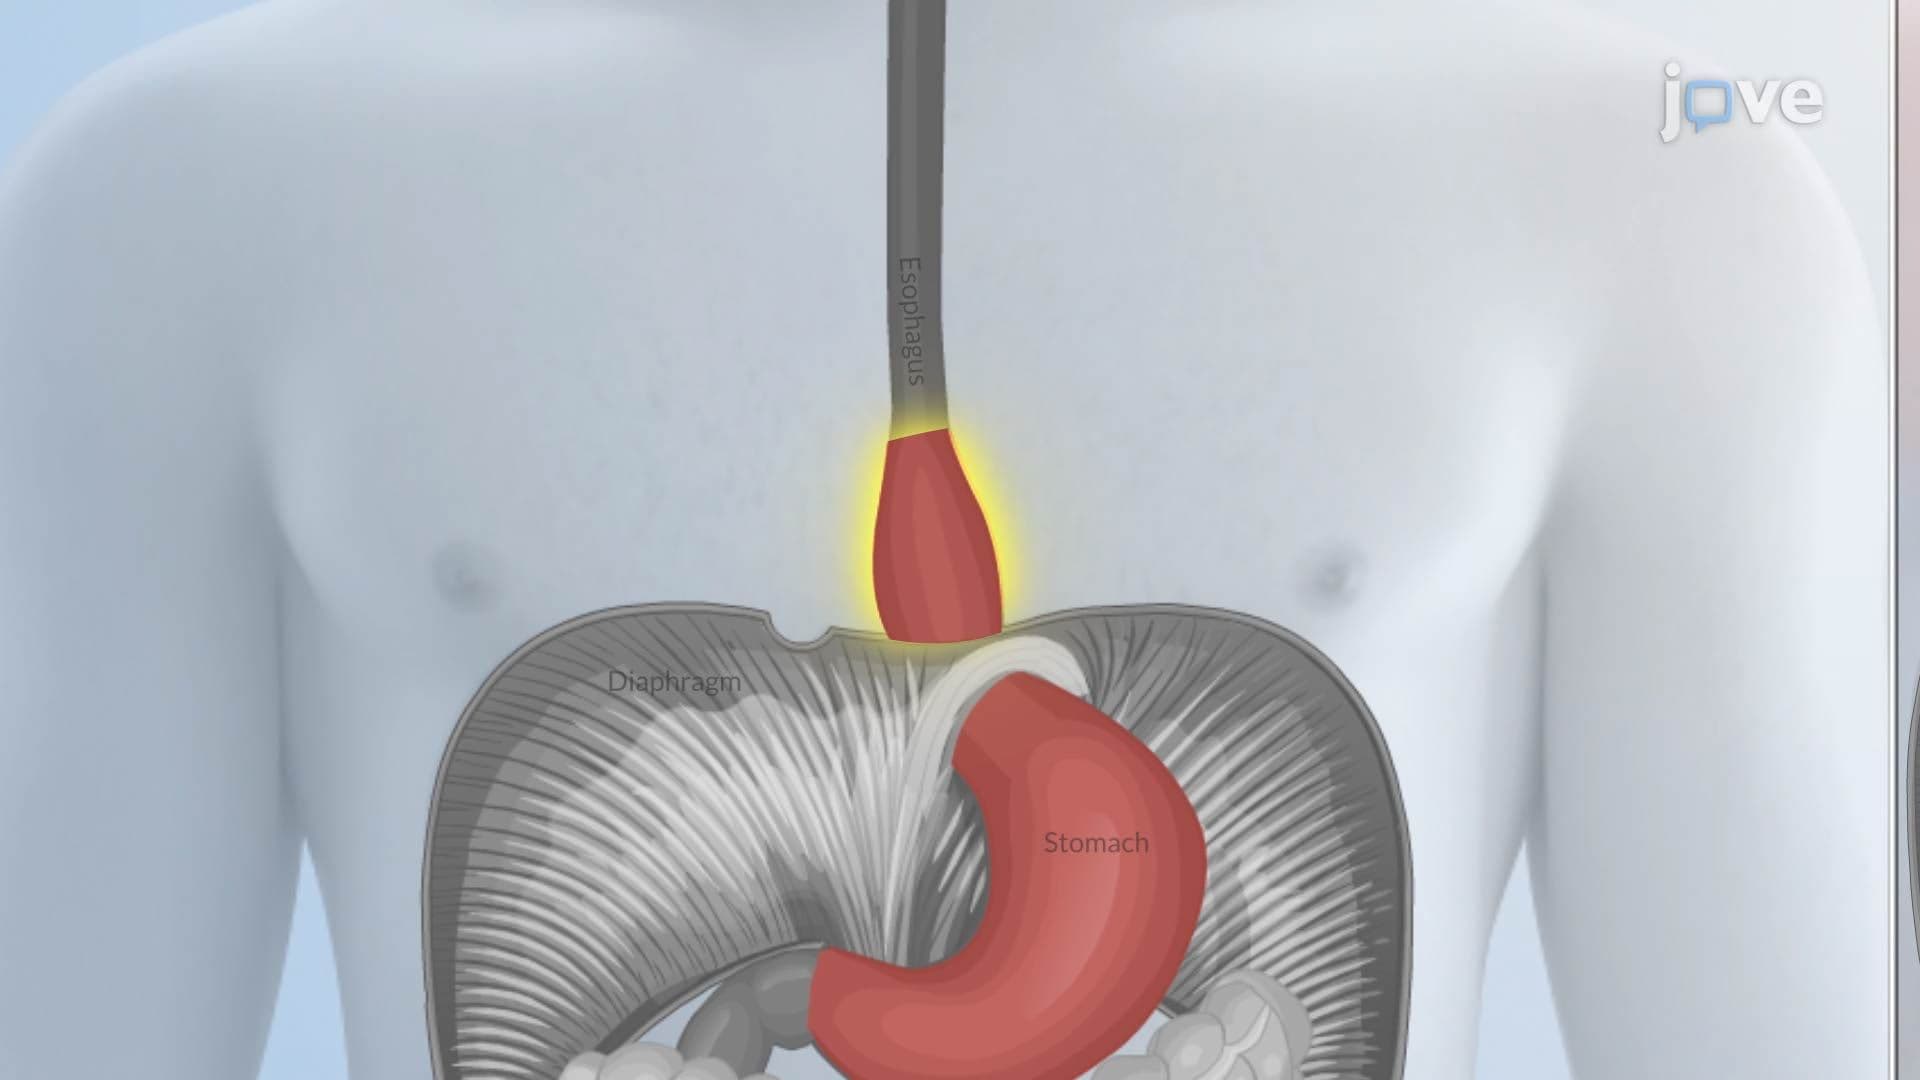
Hiatal Hernia
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:24
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...