Hippocampal and cortical atrophy in amyloid-negative mild cognitive impairments: comparison with amyloid-positive mild cognitive impairment
Related Experiment Video
Updated: May 7, 2026
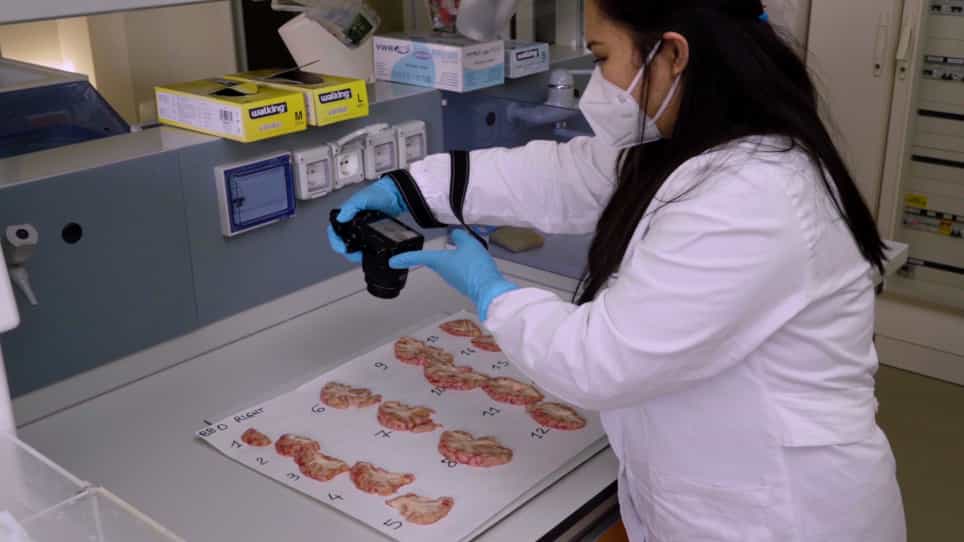
Abbiategrasso Brain Bank Protocol for Collecting, Processing and Characterizing Aging Brains
Published on: June 3, 2020
Byoung Seok Ye1, Sang Won Seo, Chi Hun Kim
1Department of Neurology, Sungkyunkwan University School of Medicine, Samsung Medical Center, Seoul, South Korea.

Abstract:
Although patients with amnestic mild cognitive impairment (aMCI) are at higher risk of developing Alzheimer's disease (AD), their pathologies could be heterogeneous. We aimed to evaluate structural changes in amyloid-negative and amyloid-positive aMCI patients. Forty-eight aMCI patients who underwent Pittsburgh compound B (PiB) positron emission tomography were recruited. They were classified as PiB (-) aMCI (N = 16) and PiB (+) (N = 32). Hippocampal shape and regional cortical thickness were compared with 41 subjects with normal cognition (NC). Relative to NC, PiB(-) aMCI exhibited hippocampal deformity in the right cornu ammonis 1, whereas PiB(+) aMCI exhibited hippocampal deformity in bilateral subiculum and cornu ammonis 1 subregions. Relative to NC, PiB(-) aMCI showed cortical thinning in the left medial prefrontal and right anterior temporal regions, whereas PiB(+) aMCI exhibited cortical thinning in bilateral medial temporal regions, temporoparietal junctions and precuneus, and prefrontal cortices. Our findings suggest that structural changes in PiB(-) aMCI might be due to several possible pathologic changes, whereas structural changes in PiB(+) aMCI reflect AD-like structural changes.
Insights
Structural brain changes in amnestic mild cognitive impairment (aMCI) differ based on amyloid-beta plaque presence. Amyloid-negative aMCI shows distinct changes, while amyloid-positive aMCI exhibits Alzheimer's disease-like patterns.
Area of Science:
- Neuroscience
- Neurology
- Medical Imaging
Background:
- Patients with amnestic mild cognitive impairment (aMCI) have an increased risk of developing Alzheimer's disease (AD).
- The underlying pathologies in aMCI patients can be heterogeneous, necessitating differentiation for accurate diagnosis and prognosis.
- Understanding structural brain differences between amyloid-positive and amyloid-negative aMCI is crucial for identifying distinct disease trajectories.
Purpose of the Study:
- To investigate and compare structural brain changes in amyloid-negative (PiB(-)) and amyloid-positive (PiB(+)) aMCI patients.
- To differentiate the specific patterns of hippocampal and cortical alterations in these two aMCI subgroups.
- To correlate observed structural changes with amyloid-beta deposition status.
Main Methods:
- Recruited 48 aMCI patients and classified them into PiB(-) aMCI (N=16) and PiB(+) aMCI (N=32) based on Pittsburgh Compound B (PiB) positron emission tomography (PET) scans.
- Compared hippocampal shape and regional cortical thickness in aMCI subgroups against 41 cognitively normal (NC) individuals.
- Utilized neuroimaging techniques to analyze structural differences in key brain regions.
Main Results:
- PiB(-) aMCI patients showed hippocampal deformity in the right cornu ammonis 1 and cortical thinning in the left medial prefrontal and right anterior temporal regions compared to NC.
- PiB(+) aMCI patients exhibited hippocampal deformity in bilateral subiculum and cornu ammonis 1, along with cortical thinning in bilateral medial temporal regions, temporoparietal junctions, precuneus, and prefrontal cortices, relative to NC.
- These findings indicate distinct structural alterations correlating with amyloid status in aMCI.
Conclusions:
- Structural changes in PiB(-) aMCI may stem from various pathological processes beyond typical AD.
- Structural alterations in PiB(+) aMCI align with known AD-related neurodegenerative patterns.
- Differentiating aMCI based on amyloid status is essential for understanding heterogeneous brain changes and disease progression.

Related Concept Videos
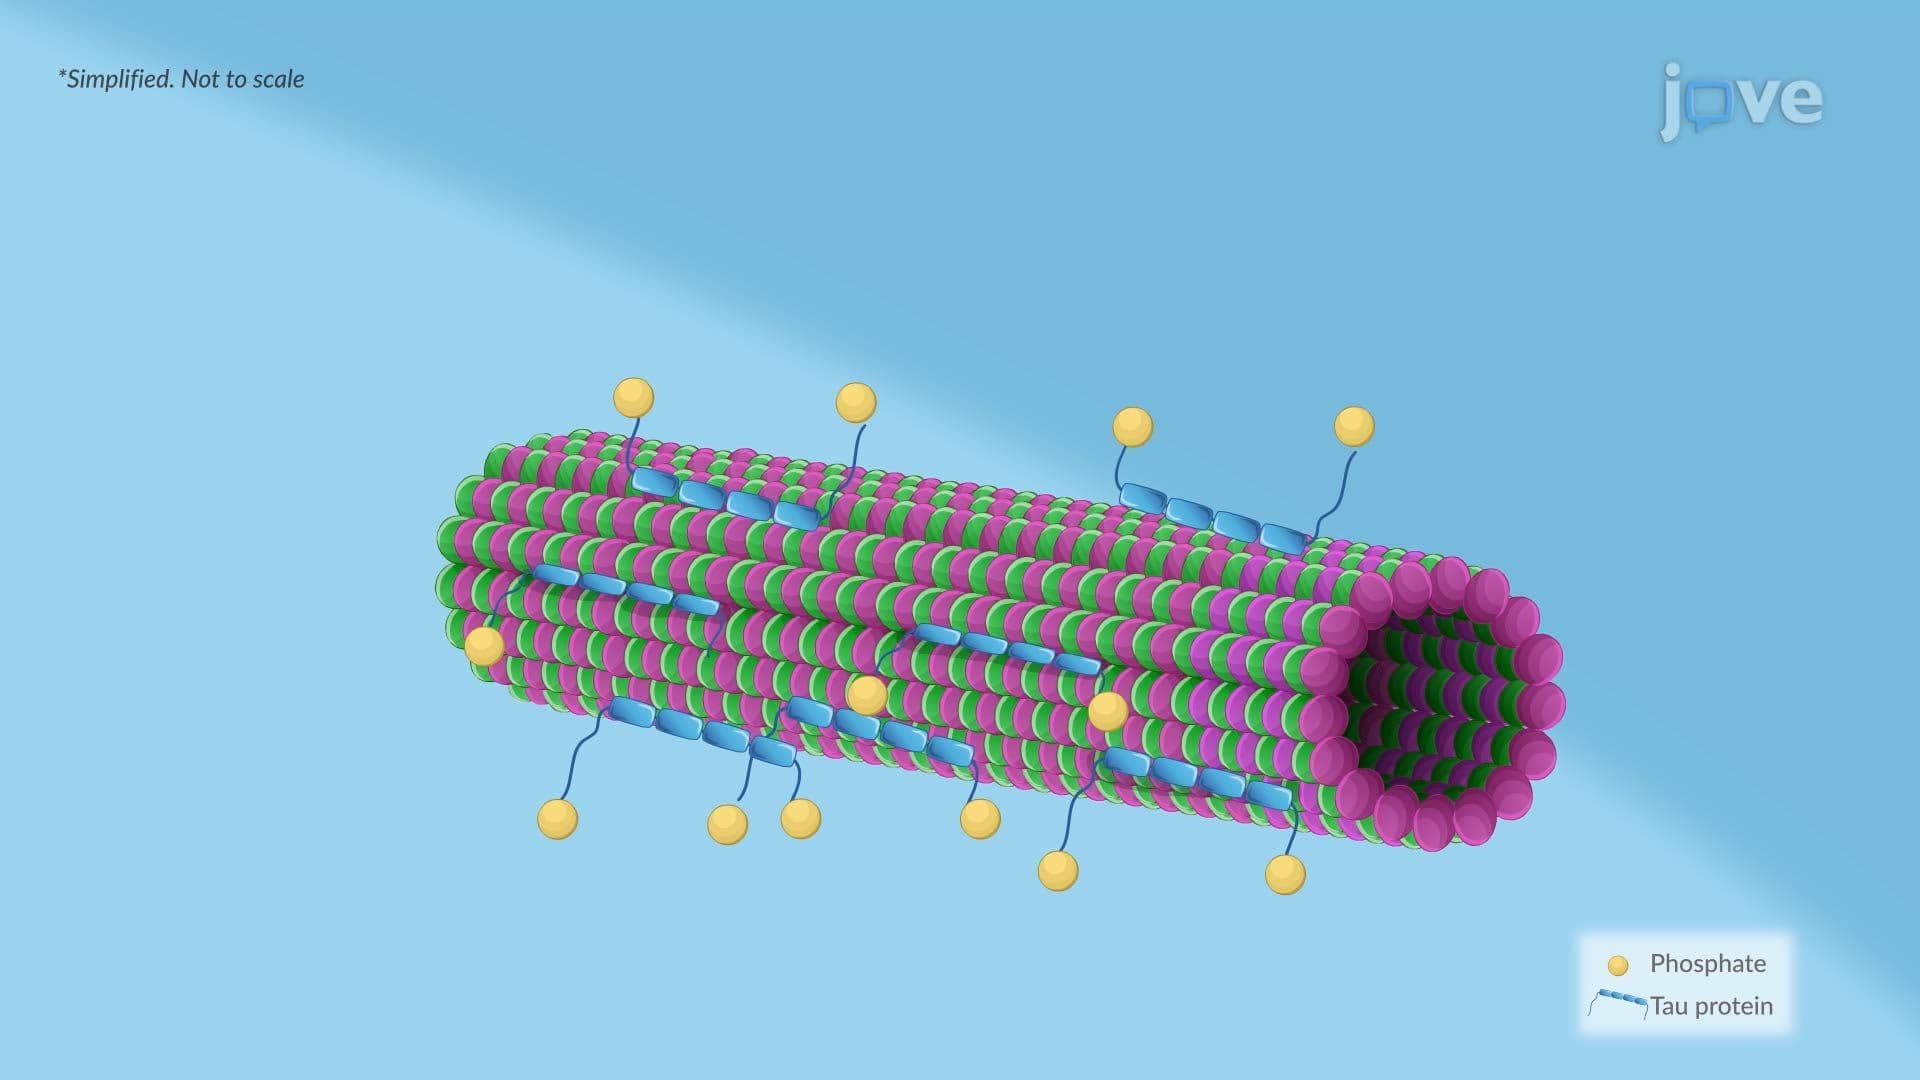 01:23
Alzheimer Disease ll: Pathophysiology
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
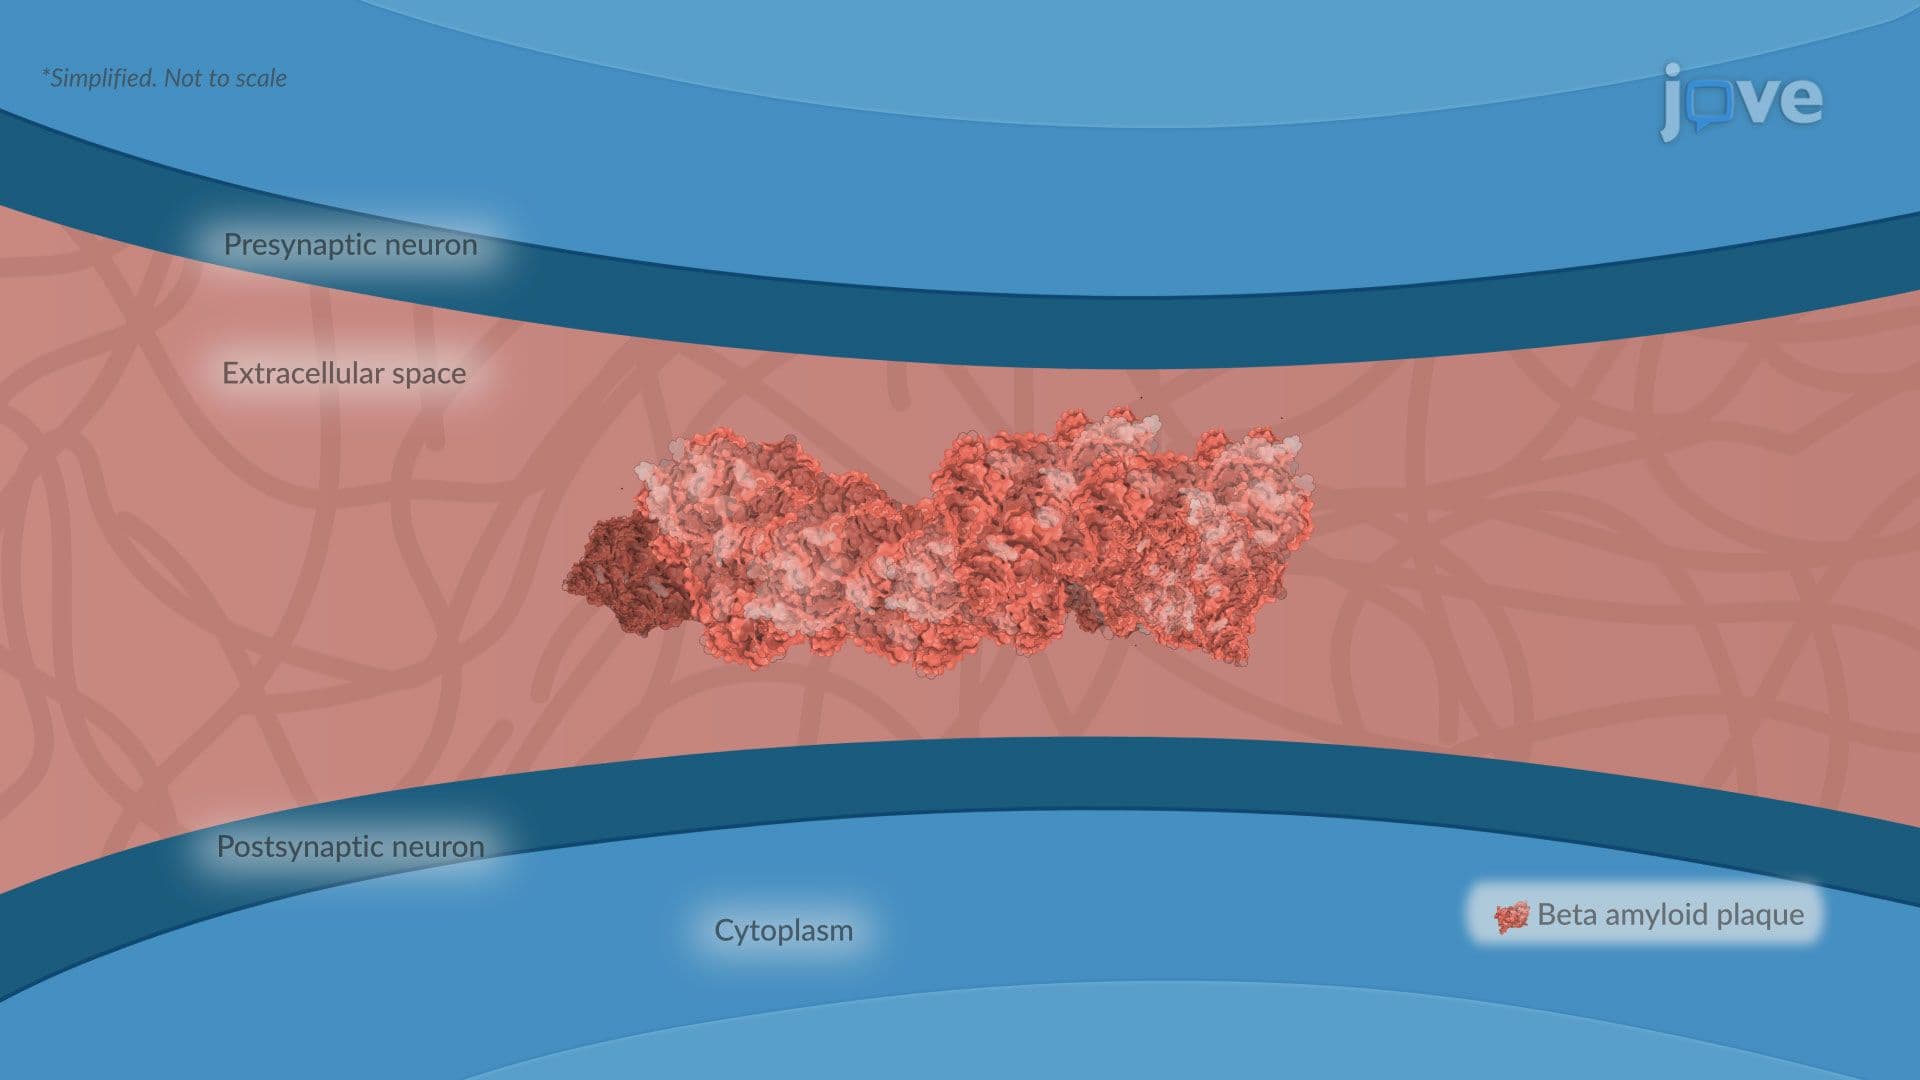 01:22
Dementia l: Introduction
 01:29
Alzheimer Disease l: Introduction
 01:30
Dementia
The progression of dementia is generally gradual.
 01:22
Alzheimer's Disease: Treatment