Ventriculo-peritoneal shunt: A rare cause of basal ganglia and thalamic abscess

Parvesh Sangwan1, Bhaskar Saikia, Pradeep Kumar Sharma

  • 1Department of Pediatrics, B. L. Kapur Super Speciality Hospital, New Delhi, India.

Insights

A thalamic abscess in a child with a ventriculo-peritoneal shunt was successfully treated with stereotactic aspiration. This approach offers a more aggressive management for deep-seated abscesses, reducing risks and improving outcomes.

Area of Science:

  • Neurosurgery
  • Pediatric Neurology
  • Infectious Diseases

Background:

  • Deep-seated brain abscesses pose significant management challenges.
  • Ventriculo-peritoneal shunts can be associated with complications, including abscess formation.
  • Thalamic abscesses are particularly difficult to access and treat.

Observation:

  • An 18-month-old female presented with a thalamic abscess secondary to ventriculo-peritoneal shunt placement.
  • The abscess was deep-seated, increasing the risks of intraventricular rupture and antibiotic resistance.

Findings:

  • Stereotactic aspiration was utilized as the primary treatment modality.
  • This minimally invasive neurosurgical technique allowed for direct abscess drainage.

Implications:

  • Stereotactic aspiration provides an effective and aggressive neurosurgical option for deep-seated thalamic abscesses.
  • Early and targeted intervention can mitigate the risks associated with complex intracranial infections.
  • This case highlights the importance of considering advanced neurosurgical techniques for shunt-related complications in pediatric patients.

Related Concept Videos

Brain Abscess l: Introduction01:26

Brain Abscess l: Introduction

A brain abscess is a focal, intracerebral infection characterized by a localized collection of pus within the brain parenchyma, resulting from microbial invasion and the body’s inflammatory response. It progresses through stages: early and late cerebritis, followed by early and late capsule formation, reflecting tissue destruction, immune response, and eventual encapsulation.Etiology and PathogenesisCausative organisms vary with source and host factors, often involving polymicrobial infections,...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Bacterial Meningitis II: Pathophysiology01:26

Bacterial Meningitis II: Pathophysiology
Bacterial meningitis typically begins when pathogens such as Neisseria meningitidis and Streptococcus pneumoniae colonize the nasopharynx and invade the bloodstream. This process is facilitated by bacterial virulence factors, such as polysaccharide capsules, which resist phagocytosis and complement-mediated killing. Less commonly, bacteria reach the central nervous system via contiguous spread from infections like otitis media or sinusitis, through congenital or acquired dural defects, or...
Anatomy of the Brain: Ventricles01:18

Anatomy of the Brain: Ventricles

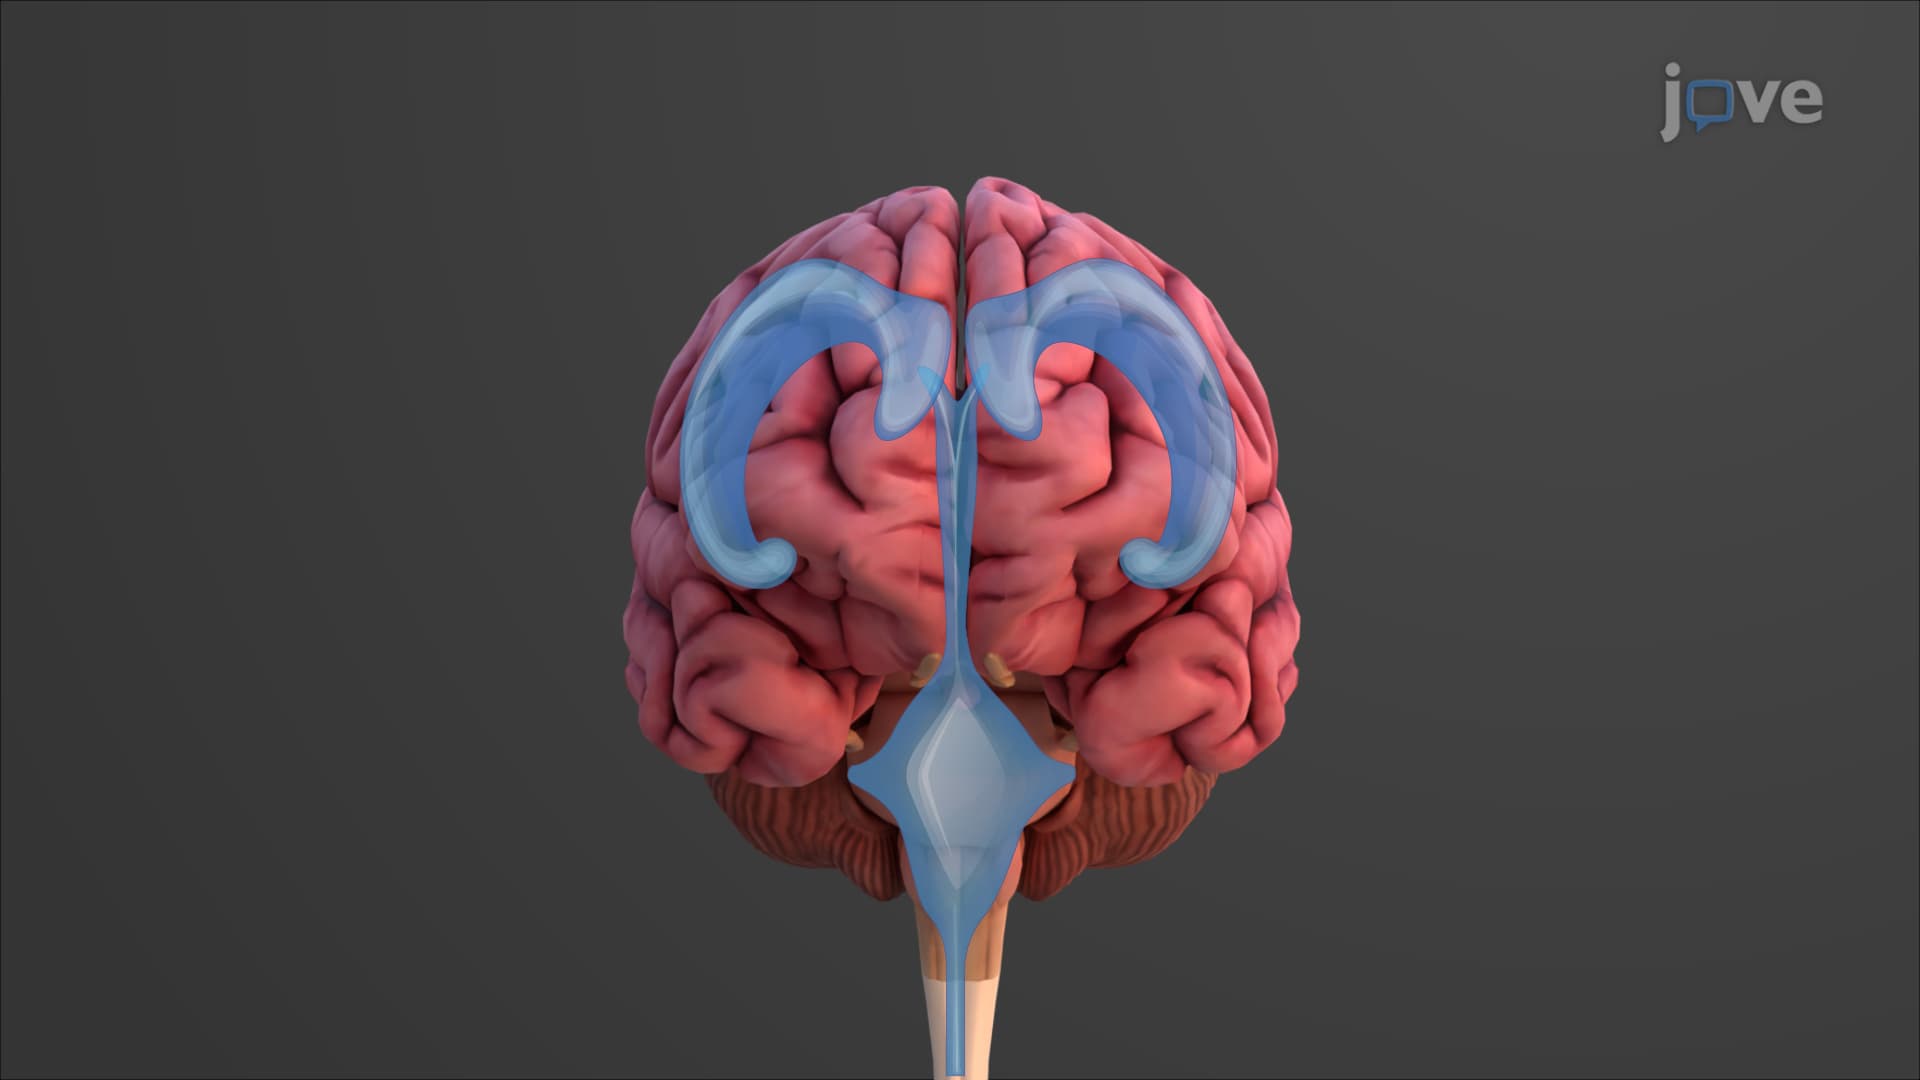
There are hollow fluid-filled cavities known as ventricles deep inside the human brain. There are two lateral ventricles, one in each cerebral hemisphere, and each has three different projections — the anterior, inferior, and posterior horns visible from the lateral side. A thin membrane called the septum pellucidum separates the two lateral ventricles. The slender third ventricle in the diencephalon is connected to each lateral ventricle via a channel called the interventricular foramen. The...
Cerebral Edema l: Introduction01:19

Cerebral Edema l: Introduction

Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
Increased Intracranial Pressure l: Introduction01:14

Increased Intracranial Pressure l: Introduction

Intracranial hypertension is a sustained elevation of intracranial pressure (ICP) above 22 mm Hg. In supine adults, normal ICP is ~7–15 mm Hg.The rigid, nonexpandable cranium contains three components—brain tissue, blood, and cerebrospinal fluid (CSF)—that total ~1,700 mL in a typical adult: 1,400 mL brain (~80%), 150 mL blood (~10%), and 150 mL CSF (~10%). According to the Monro–Kellie doctrine, total intracranial volume is effectively fixed. When one component expands, CSF and venous blood...





