Related Experiment Video
Updated: May 7, 2026


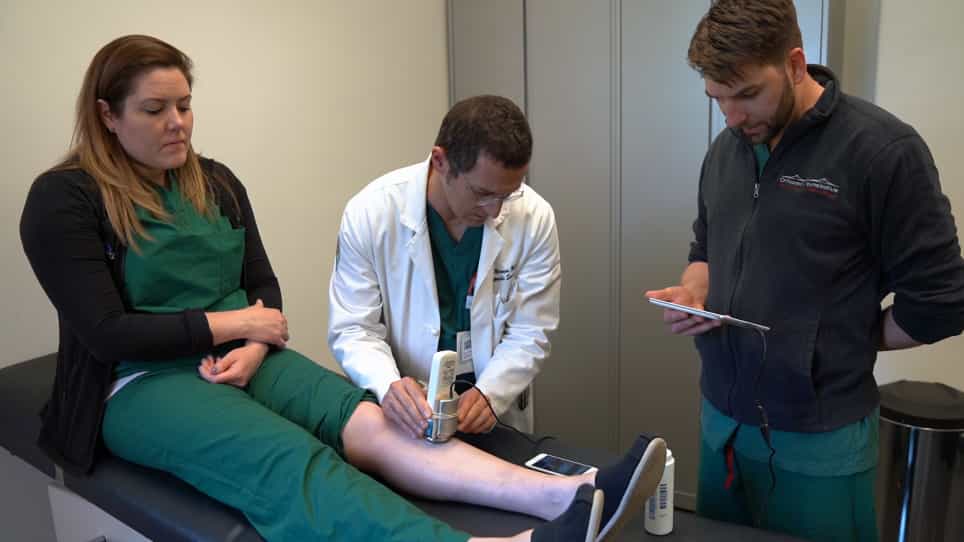
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Compartment syndrome as a complication of ileofemoral deep venous thrombosis:a case presentation
David R Lamborn1, Craig Schranz1
1Emergency Department, Naval Medical Center, Portsmouth, VA 23708, USA.

Abstract:
A 22-year-old morbidly obese, nonpregnant woman presented with left ileofemoral deep vein thrombosis (DVT) presenting as low back pain and bilateral, left greater than right, leg swelling and pain for 2 days. While on heparin, she developed compartment syndrome in her left leg and had evidence of dead muscle tissue at the time of fasciotomy. Three options exist for treatment of ileofemoral DVT: catheter-directed thrombolysis (CDT), CDT plus pharmacomechanical thrombolysis or percutaneous mechanical thrombectomy, and surgical thrombectomy. Catheter-directed thrombolysis alone or in conjunction with pharmacomechanical thrombolysis in patients with low risk of bleeding has shown significant lysis of occlusion in 79% of patients with ileofemoral DVT with relatively low complication rates. Surgical thrombectomy and fasciotomy have not proven to be as effective but are appropriate alternatives if CDT is not available. Standard anticoagulation alone is likely not a sufficient treatment for ileofemoral DVT. Other therapies including CDT, CDT plus pharmacomechanical thrombolysis or percutaneous mechanical thrombectomy, or surgical thrombectomy to address lysis of the clot should be attempted first or in conjunction with anticoagulation for appropriate patients. Catheter-directed thrombolysis with or without pharmacomechanical thrombolysis is the preferred initial treatment.
Related Concept Videos
 01:30
Venous Thrombosis I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Varicose Veins I: Introduction
 01:19
Pulmonary Embolism I: Introduction