Related Experiment Video
Updated: May 7, 2026

Ex Vivo Porcine Experimental Model for Studying and Teaching Lung Mechanics
Published on: April 19, 2024
Expiratory rib cage Compression in mechanically ventilated subjects: a randomized crossover trial [corrected]
Fernando S Guimarães1, Agnaldo J Lopes, Sandra S Constantino
1Rehabilitation Sciences Master's Program, Augusto Motta University Center, Rio de Janeiro, Brazil.

Background:
Expiratory rib cage compression (ERCC) has been empirically used by physiotherapists with the rationale of improving expiratory flows and therefore the airway clearance in mechanically ventilated patients. This study evaluates the acute mechanical effects and sputum clearance of an ERCC protocol in ventilated patients with pulmonary infection.
Methods:
In a randomized crossover study, sputum production and respiratory mechanics were evaluated in 20 mechanically ventilated subjects submitted to 2 interventions. ERCC intervention consisted of a series of manual bilateral ERCCs, followed by a hyperinflation maneuver. Control intervention (CTRL) followed the same sequence, but instead of the compressive maneuver, the subjects were kept on normal ventilation. Static (Cst) and effective (C(eff)) compliance and total (R(tot)) and initial (R(init)) resistance of the respiratory system were measured pre-ERCC (baseline), post-ERCC or CTRL (POST1), and post-hyperinflation (POST2). Peak expiratory flow (PEF) and the flow at 30% of the expiratory tidal volume (flow 30% VT) were measured during the maneuver.
Results:
ERCC cleared 34.4% more secretions than CTRL (1 [0.5-1.95] vs 2 [1-3.25], P < .01). Respiratory mechanics showed no differences between control and experimental intervention in POST1 for Cst, Ceff, R(tot), and R(init). In POST2, ERCC promoted an increase in Cst (38.7 ± 10.3 vs 42.2 ± 12 mL/cm H2O, P = .03) and in C(eff) (32.6 ± 9.1 vs 34.8 ± 9.4 mL/cm H2O, P = .04). During ERCC, PEF increased by 16.2 L/min (P < .001), and flow 30% VT increased by 25.3 L/min (P < .001) compared with CTRL. Six subjects (30%) presented expiratory flow limitation (EFL) during ERCC. The effect size was small for secretion volume (0.2), Cst (0.15), and C(eff) (0.12) and negligible for R(tot) (0.04) and R(init) (0.04).
Conclusions:
Although ERCC increases expiratory flow, it has no clinically relevant effects from improving the sputum production and respiratory mechanics in hypersecretive mechanically ventilated patients. The maneuver can cause EFL in some patients. (ClinicalTrials.gov registration NCT01525121).
More Related Videos
 07:52
Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
Related Concept Videos
 01:08
Pneumothorax II: Pathophysiology
 01:26
Respiratory Volumes and Capacities I
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
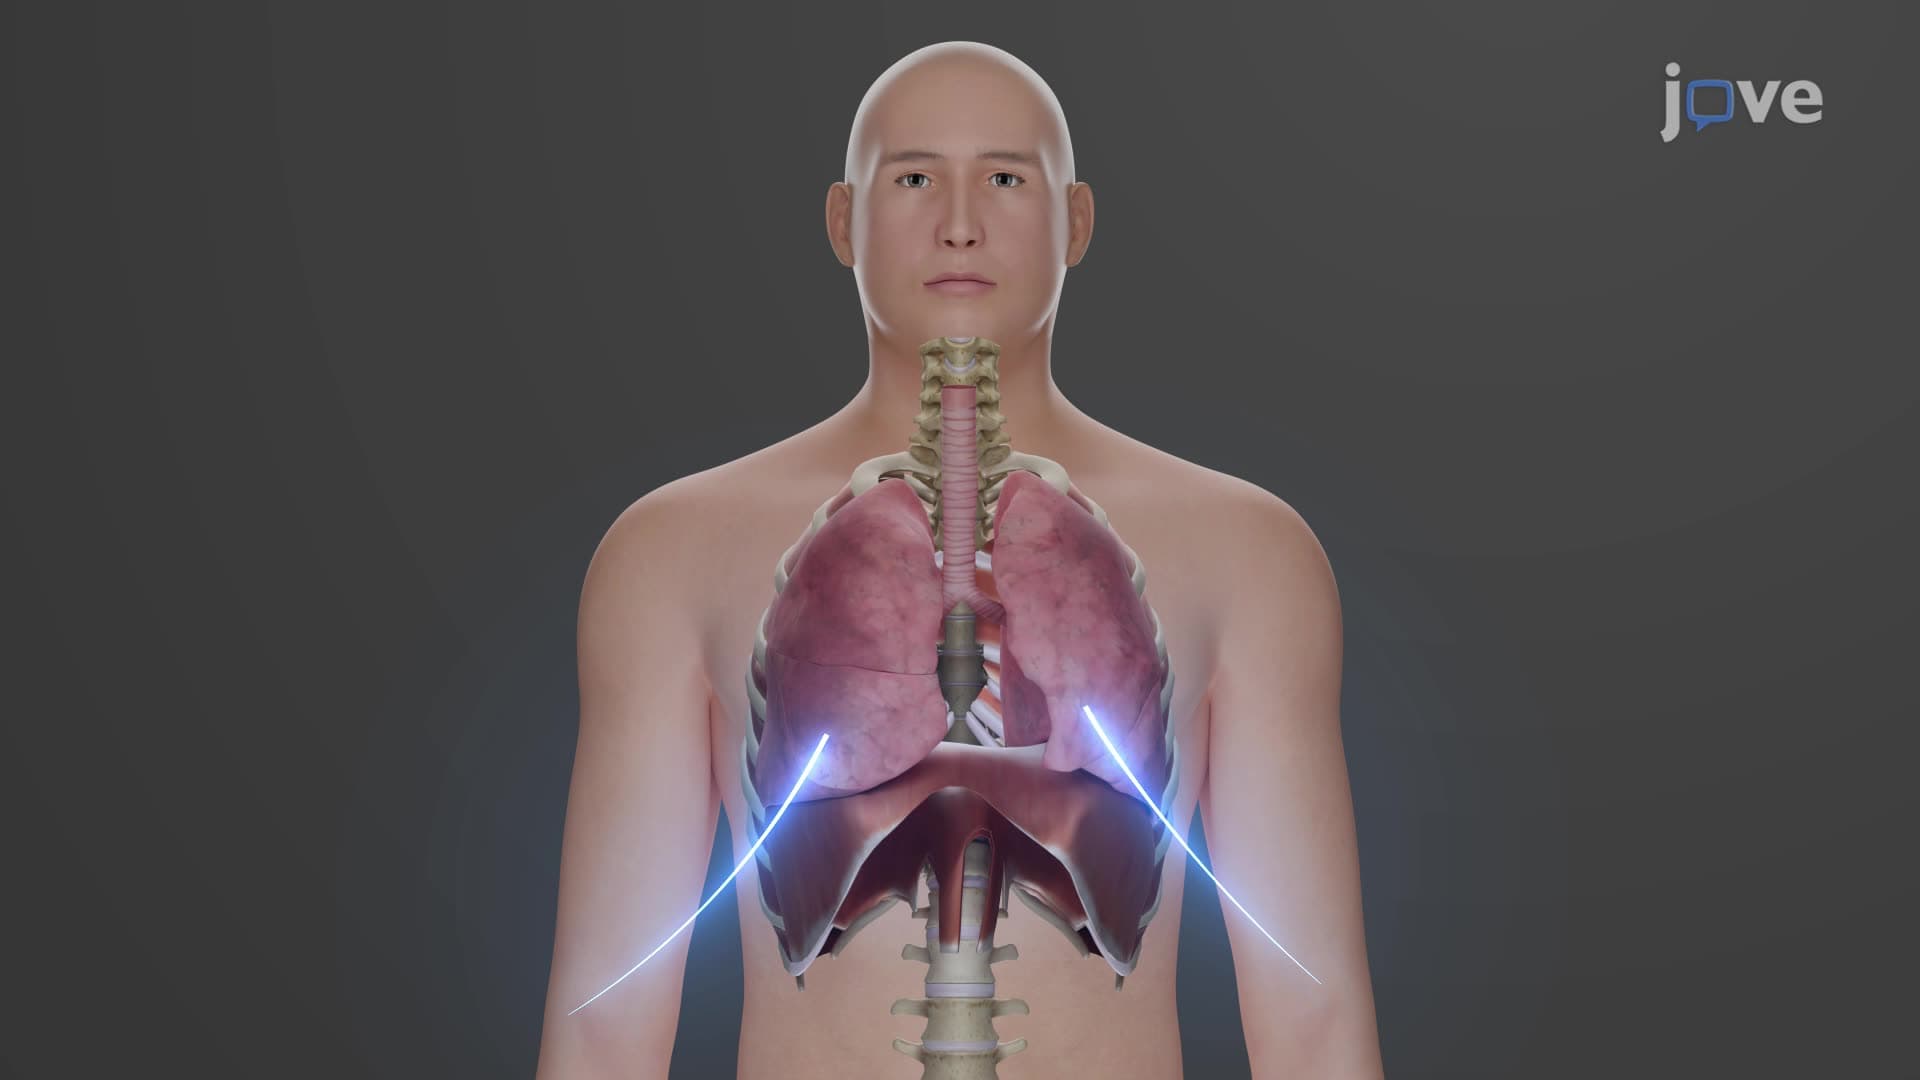
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:15
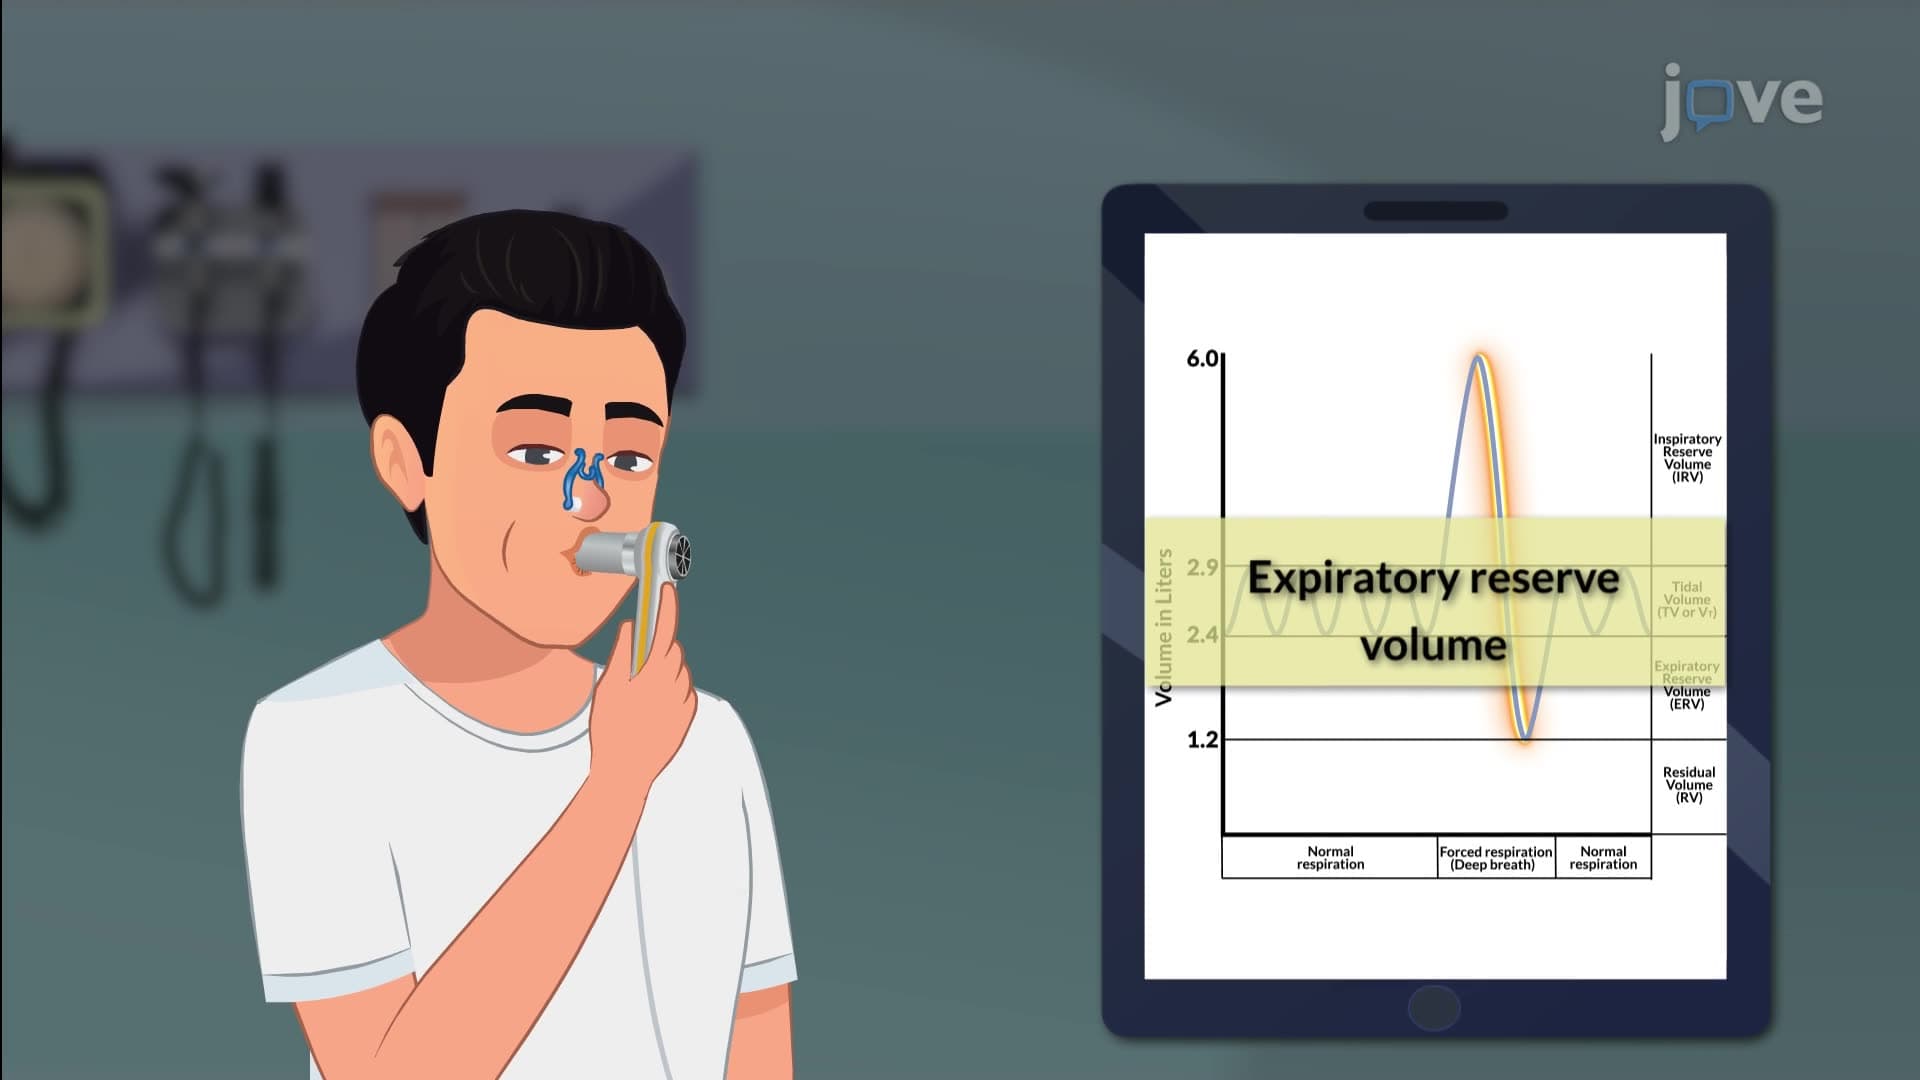
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: