Related Experiment Video
Updated: May 7, 2026
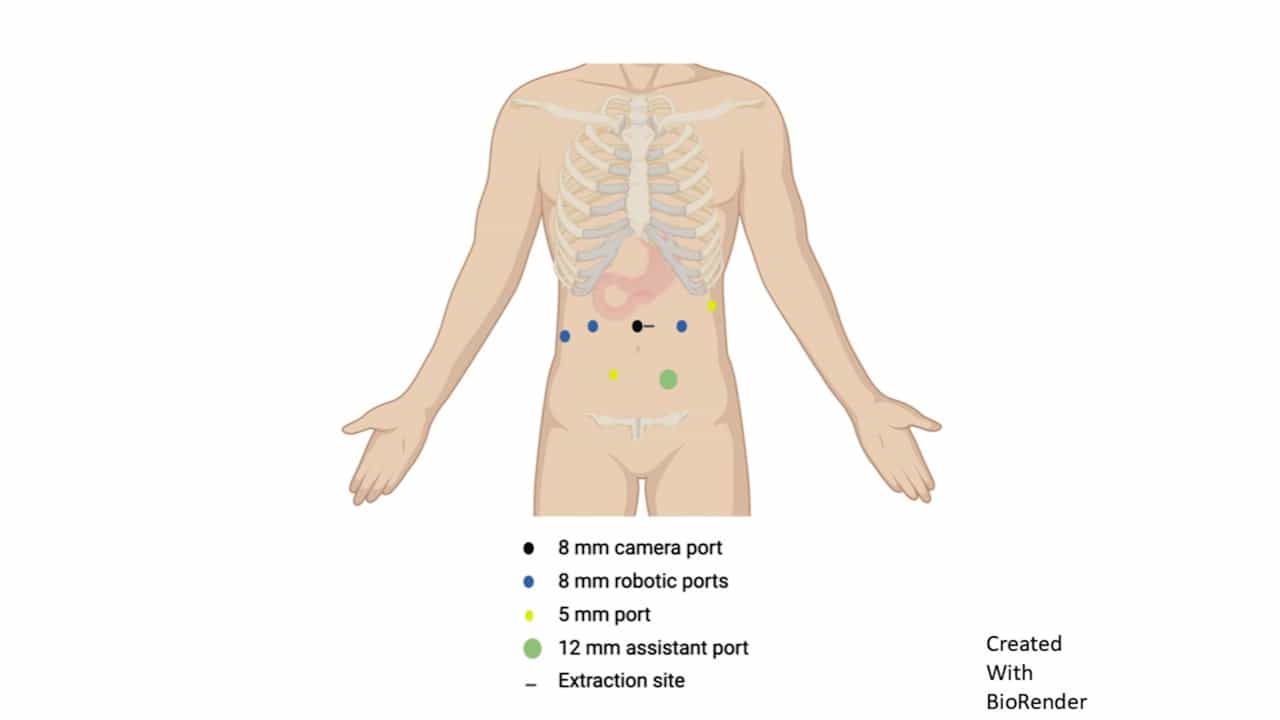

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Beyond the GIST: mesenchymal tumors of the stomach
Hyunseon C Kang1, Christine O Menias, Ayman H Gaballah
1Departments of Diagnostic Radiology and Pathology, University of Texas M.D. Anderson Cancer Center, 1515 Holcombe Blvd, Unit 1473, Houston, TX 77030; Department of Radiology, Mayo Clinic, Tucson, Ariz.

Abstract:
Intramural gastric masses arise in the wall of the stomach (generally within the submucosa or muscularis propria), often with intact overlying mucosa. These tumors are typically mesenchymal in origin and have overlapping radiologic appearances. A combination of features such as location, attenuation, enhancement, and growth pattern may suggest one diagnosis over another. Gastrointestinal stromal tumors (GISTs) account for the majority of intramural tumors and can vary widely in appearance, from small intraluminal lesions to exophytic masses that protrude into the peritoneal cavity, commonly with areas of hemorrhage or necrosis. A well-circumscribed mass measuring -70 to -120 HU is a lipoma. Leiomyomas usually manifest as low-attenuation masses at the gastric cardia. Homogeneous attenuation is a noteworthy characteristic of schwannomas, particularly for larger lesions that might otherwise be mistaken for GISTs. A hypervascular mass in the antrum is a common manifestation of glomus tumors. Hemangiomas are also hypervascular but often manifest in childhood. Inflammatory fibroid polyps usually arise as a polypoid mass in the antrum. Inflammatory myofibroblastic tumors are infiltrative neoplasms with a propensity for local recurrence. Plexiform fibromyxomas are rare, usually antral tumors. Carcinoid tumors are epithelial in origin, but often submucosal in location, and therefore should be distinguished from other intramural lesions. Multiple carcinoid tumors are associated with hypergastrinemia, either in the setting of chronic atrophic gastritis or Zollinger-Ellison syndrome. Sporadic solitary carcinoid tumors not associated with hypergastrinemia have a higher rate of metastasis. Histopathologic analysis, including immunohistochemistry, is usually required for diagnosis of intramural masses.
More Related Videos
 10:28
Gene Regulation and Targeted Therapy in Gastric Cancer Peritoneal Metastasis: Radiological Findings from Dual Energy CT and PET/CT
Published on: January 22, 2018
 05:16
Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
Related Concept Videos
 01:16
Gross Anatomy of the Stomach
 02:30
Metastasis
Epithelial-to-Mesenchymal Transition
The epithelial-to-mesenchymal transition or EMT is a developmental process commonly observed in wound healing, embryogenesis, and cancer metastasis. EMT is induced by transforming growth factor-beta (TGF-β) or receptor tyrosine kinase (RTK) ligands, which further...
 01:26
Stomach Histology
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 02:17
The Tumor Microenvironment
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...