Related Experiment Video
Updated: May 7, 2026
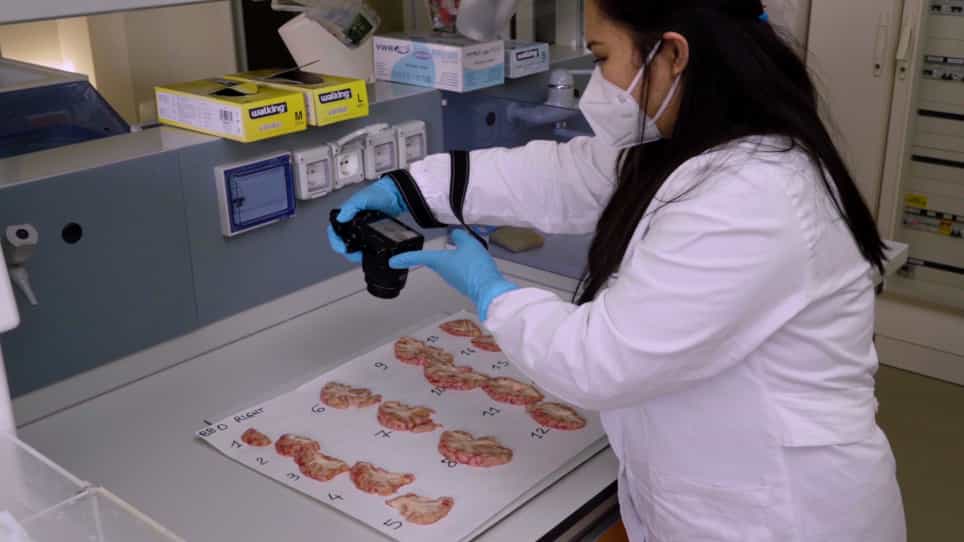
Abbiategrasso Brain Bank Protocol for Collecting, Processing and Characterizing Aging Brains
Published on: June 3, 2020
Clinical, electrophysiological, imaging, and ultrastructural description in 68 patients with neuronal ceroid
Rakesh H Jadav1, Sanjib Sinha1, T C Yasha2
1Department of Neurology, National Institute of Mental Health and Neurosciences, Bangalore, India.

Purpose:
We evaluated the clinical, electrophysiological, imaging, and ultrastructural features of neuronal ceroid lipofuscinoses and its subtypes.
Methods:
The clinical, electrophysiological, imaging, histopathological, and ultrastructural features of 68 (age at onset: 4.3 ± 5.4 years) neuronal ceroid lipofuscinoses and its subtypes (infantile neuronal ceroid lipofuscinoses [9], late infantile neuronal ceroid lipofuscinoses [34], juvenile neuronal ceroid lipofuscinoses [23], and adult neuronal ceroid lipofuscinoses [2] were evaluated. Skin (n = 56), brain (n = 12), muscle (n = 4) and nerve (n = 1) biopsies confirmed the diagnosis.
Results:
Clinical manifestations were milestone regression (93%), involuntary movements (92%), seizures (89%), myoclonus (79%), and visual impairment (68%). Response to anticonvulsants was unsatisfactory. Electroencephalography (n = 59) was abnormal in 90%: background slowing (90%); epileptiform discharges (71%), and photoparoxysmal response (4/21). Visual-evoked (n = 33) and somatosensory evoked (n = 40) potentials were abnormal in 62% and 63% of patients. Cranial computed tomography (n = 33) showed diffuse cerebral (61%) and cerebellar (27%) atrophy. Magnetic resonance imaging was abnormal in all 43 patients who were scanned: diffuse atrophy (100%), cerebellar atrophy (40%), leukoencephalopathy (65%), and thalamic T2 W hypointensity (33%). Dermal inclusions such as curvilinear inclusions were the most common abnormality: late infantile neuronal ceroid lipofuscinoses (97%), juvenile neuronal ceroid lipofuscinoses (100%), and infantile neuronal ceroid lipofuscinoses (88%). Additional fingerprint inclusions were noted: juvenile neuronal ceroid lipofuscinoses (43%), late infantile neuronal ceroid lipofuscinoses (15%), and infantile neuronal ceroid lipofuscinoses (13%). Granular osmiophilic deposits were noted in 50% of infantile neuronal ceroid lipofuscinoses. In 75% of patients, there was good correlation between the clinical subtype and ultrastructural inclusion pattern. In 27% of neuronal ceroid lipofuscinoses, multiple inclusions were noted.
Conclusions:
The diagnosis of neuronal ceroid lipofuscinoses should be considered in individuals with characteristic clinical presentations and characteristic ultrastructural dermal inclusions. Three fourths showed morphological correlation of the inclusions with neuronal ceroid lipofuscinoses subtype.
More Related Videos
 08:33
Olfactory Neurons Obtained through Nasal Biopsy Combined with Laser-Capture Microdissection: A Potential Approach to Study Treatment Response in Mental Disorders
Published on: December 4, 2014
 08:59
Real-Time Fluorescent Measurement of Synaptic Functions in Models of Amyotrophic Lateral Sclerosis
Published on: July 16, 2021
