Related Experiment Video
Updated: May 7, 2026
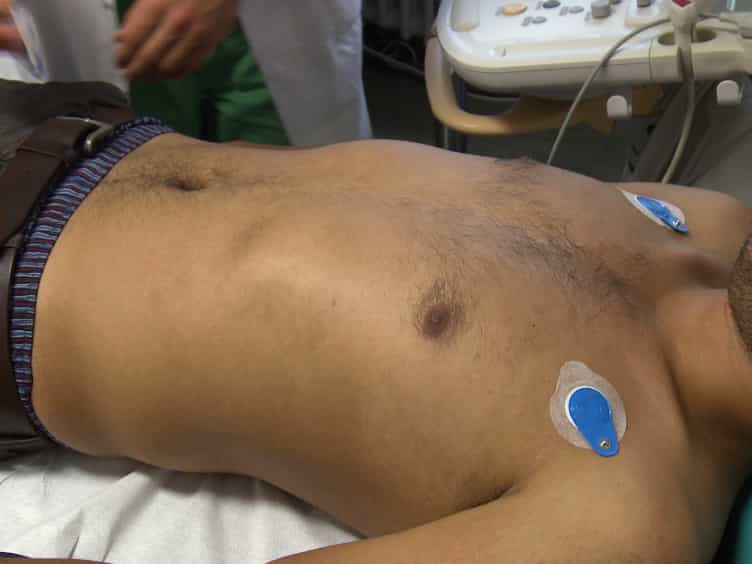

Transthoracic Speckle Tracking Echocardiography for the Quantitative Assessment of Left Ventricular Myocardial Deformation
Published on: October 20, 2016
Systolic and diastolic function assessment in fabry disease patients using speckle-tracking imaging and comparison
Miriam Shanks1, Richard B Thompson, Ian D Paterson
1Division of Cardiology, Department of Medicine, Mazankowski Alberta Heart Institute, University of Alberta, Edmonton, Alberta, Canada.

Insights
Strain and strain rate analysis effectively detects subclinical Fabry cardiomyopathy, even without left ventricular hypertrophy. Echocardiography reveals reduced myocardial function, aiding early diagnosis and management of Fabry disease.
Area of Science:
- Cardiology
- Medical Imaging
- Genetics
Background:
- Fabry cardiomyopathy, a complication of Fabry disease (FD), causes progressive left ventricular hypertrophy (LVH) and diastolic dysfunction.
- LVH is not universally present in FD patients, especially early in the disease or in females.
- Myocardial deformation analysis using strain and strain rate (SR) may detect subclinical Fabry cardiomyopathy independently of LVH.
Purpose of the Study:
- To assess systolic and diastolic myocardial function in Fabry disease patients using echocardiography.
- To determine if strain and SR analysis can identify subclinical cardiac dysfunction in FD, irrespective of LVH.
- To compare the diagnostic performance of strain/SR analysis with conventional echocardiographic indices.
Main Methods:
- 16 FD patients and 24 controls underwent two-dimensional speckle-tracking echocardiography.
- Assessed longitudinal, circumferential, and radial systolic strain and SR, plus diastolic SR and strain.
- Measured mitral annular velocities (S', E') and calculated diastolic filling indices (E/SR(IVR), E/E').
Main Results:
- FD patients had normal ejection fractions; 9/16 had LVH.
- Reduced longitudinal systolic strain and SR, and impaired longitudinal diastolic SR (early diastole, isovolumic relaxation [SR(IVR)]) were observed in FD patients.
- SR(IVR) and E/SR(IVR) remained significantly different after adjusting for LVH, showing high sensitivity (94%) and specificity (92%) for detecting cardiac dysfunction.
Conclusions:
- Strain and SR analysis is valuable for identifying reduced myocardial function in FD patients.
- Longitudinal systolic strain and diastolic isovolumic SR are superior echocardiographic measures of myocardial function in FD.
- These measures are independent of LVH, offering a sensitive tool for early detection of Fabry cardiomyopathy.
Background:
Fabry cardiomyopathy is characterized by progressive left ventricular hypertrophy (LVH) associated with diastolic dysfunction and is the most common cause of death in Fabry disease (FD). However, LVH is not present in all subjects, particularly early in disease progression and in female patients. Direct assessment of myocardial deformation by strain and strain rate (SR) analysis may be sensitive to detect subclinical Fabry cardiomyopathy independent of the presence of LVH.
Methods:
Systolic (longitudinal, circumferential, and radial systolic strain and SR) and diastolic (SR during isovolumic relaxation [SR(IVR)] and early diastole and strain at peak transmitral E wave) function was assessed in 16 patients with FD using two-dimensional speckle-tracking echocardiography. In addition, mean S' and E' mitral annular velocities by Doppler tissue imaging were measured. Diastolic filling indices, including E/SR(IVR) and E/E' ratios, were calculated. The patients were compared with 24 healthy age-matched and gender-matched controls.
Results:
All 16 patients with FD had normal left ventricular ejection fractions, and nine patients had LVH. Compared with controls, patients with FD had reduced longitudinal systolic strain (P < .001) and systolic SR (P = .007), while there were no differences in circumferential systolic strain and S'. Diastolic function assessment showed reduced longitudinal early diastolic SR (P = .001), SR(IVR) (P < .001), and E/SR(IVR) (P < .001), while radial and circumferential diastolic function was not affected. Of the conventional diastolic function indices, reductions were seen in E (P = .006), E' (P = .021), and E/E' ratio (P < .001). After correcting for LVH, only SR(IVR) (P < .001) and E/SR(IVR) (P = .025) remained significantly different between patients with FD and controls, with sensitivity of 94% and specificity of 92% for SR(IVR) of 0.235 sec(-1) (area under the receiver operating characteristic curve, 0.953).
Conclusions:
Strain and SR analysis is useful in identifying patients with FD with reduced myocardial function, with longitudinal systolic strain and diastolic isovolumic SR being superior to the other echocardiographic measurements of myocardial contraction and relaxation and independent of LVH.
More Related Videos
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
 12:12
Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
Related Concept Videos
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies