Related Experiment Video
Updated: May 6, 2026
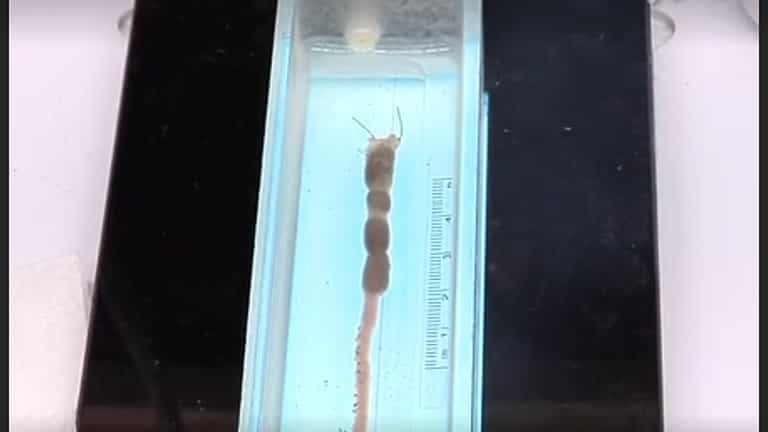

Gastrointestinal Motility Monitor GIMM
Published on: December 1, 2010
Rectal motility in pediatric constipation
Iben Moeller Joensson1, Soren Hagstroem, Lotte Fynne
1*Institute of Clinical Medicine, University of Aarhus †Department of Pediatrics, Aarhus University Hospital, Skejby ‡Neurogastroenterology Unit, Department of Hepatology and Gastroenterology V, Aarhus University, Hospital, Aarhus, Denmark.

Insights
Children with constipation exhibit prolonged rectal contractions and larger rectal dimensions compared to healthy children. This study utilized rectal impedance planimetry to assess rectal motility and size in pediatric constipation.
Area of Science:
- Pediatric Gastroenterology
- Gastrointestinal Motility Research
- Clinical Physiology
Background:
- Childhood constipation is a prevalent condition with unclear etiological factors.
- Rectal impedance planimetry offers detailed insights into rectal cross-sectional area (CSA) and pressure, crucial for understanding rectal motility.
Purpose of the Study:
- To investigate and compare rectal motility patterns between children experiencing constipation and healthy children.
- To characterize differences in rectal dimensions and compliance using rectal impedance planimetry.
Main Methods:
- The study involved 10 constipated children (Rome III criteria) and 10 healthy children, aged 8.8 and 9.9 years, respectively.
- Rectal impedance planimetry measured CSA at three levels, recorded resting motility for 30 minutes, and assessed compliance via distension.
- Phasic rectal contractions were defined as >10% CSA change from baseline for at least 2 minutes.
Main Results:
- Constipated children showed significantly longer durations of phasic rectal contractions (median 38%) compared to healthy children (median 8.8%).
- Rectal CSA was significantly larger in constipated children (median 1802 mm²) versus healthy children (median 1375 mm²).
- Rectal compliance did not significantly differ between the two groups.
Conclusions:
- Children with constipation demonstrate a prolonged period of phasic rectal contractions.
- Constipated children exhibit larger rectal dimensions than their healthy counterparts.
- These findings suggest altered rectal motility and size contribute to pediatric constipation.
Objectives:
Constipation is a common disorder in children, but little is known about its etiology. Rectal impedance planimetry determines segmental rectal cross-sectional area (CSA) and pressure, allowing detailed description of rectal motility. The aim of the present study was to compare rectal motility in healthy and constipated children.
Methods:
We analyzed data from 10 children (1 girl) with constipation according to the Rome III criteria, mean age 8.8 years (standard deviation ± 1.2), and 10 healthy children (5 girls), mean age 9.9 years (standard deviation ± 1.5). CSA was determined at 3 levels (4, 5.5, and 7 cm from the anal verge). The resting rectal motility was recorded for 30 minutes followed by a distension protocol to assess compliance. Runs of phasic rectal contractions were defined as changes of >10% from baseline CSA and lasting at least 2 minutes. Rectal dimensions were expressed as mean CSA.
Results:
A low-amplitude contraction pattern (3%-5% of baseline CSA) with a frequency of 6 to 8/minute was present in all of the children. There was significantly more time with phasic rectal contractions in constipated children (median 38%, range [0-100]) compared with healthy children (median 8.8%, range [0-57]) (P < 0.05). The rectal CSA was higher in constipated children (median 1802 mm [range 1106-2948]) compared with healthy children (1375 mm [range 437-1861]) (P < 0.05), but compliance did not differ (constipated: median 38 mm/H2O [range 12-86] vs healthy 33 mm/H2O [range 10-63]) (P = 30).
Conclusions:
In children with constipation, we found phasic rectal contractions for a significantly longer period compared with healthy children, and their rectum is larger than normal.
More Related Videos

Related Concept Videos
 01:20
Drugs Affecting GI Tract Motility: Other Laxatives
Osmotic or saline laxatives, like magnesium hydroxide or milk of...
 01:20
Gastrointestinal Motility Disorders
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:23
Drugs Affecting GI Tract Motility: Serotonin Receptor Agonists
 01:22
Drugs Affecting GI Tract Motility: Bulk-Forming and Stimulant Laxatives
Bulk-forming laxatives, such as psyllium, methylcellulose, and polycarbophil, absorb water in the intestine, increasing stool bulk and promoting bowel movement. This...
 01:28
Drugs Affecting GI Tract Motility: Dopamine Receptor Antagonists