Related Experiment Video
Updated: May 6, 2026
SECONDs Administration Guidelines: A Fast Tool to Assess Consciousness in Brain-injured Patients
Published on: February 6, 2021
Implementing routine screening for distress, the sixth vital sign, for patients with head and neck and neurologic
Barry D Bultz1, Amy Waller, Jodi Cullum
1From the aDepartment of Psychosocial Resources, Tom Baker Cancer Centre; bDepartment of Oncology, University of Calgary; cResearch and Evaluation Unit, Alberta Health Services, University of Calgary; and dDepartment of Oncology, Tom Baker Cancer Center, University of Calgary, Calgary Alberta; and the eDepartment of Oncology, Division of Palliative Care Medicine, University of Alberta, Edmonton, Alberta, Canada.

Abstract:
This study examined the benefits of incorporating screening for distress as a routine part of care for patients with head and neck and neurologic cancers in a tertiary cancer center. Using a comparative 2-cohort pre-post implementation sequential design, consecutive outpatients with head and neck and neurologic cancers were recruited into 2 separate cohorts. Cohort 1 included patients attending clinics during April 2010, before the implementation of the screening program. The program was then implemented and patients completed the Screening for Distress Minimum Dataset (the Edmonton Symptom Assessment System [ESAS] and the Canadian Problem Checklist [CPC]) at each clinic visit. Cohort 2 included patients attending clinics during March 2011. Consenting patients completed screening and outcome measures (ESAS, CPC, and either the Functional Assessment of Cancer Therapy-Brain or the Functional Assessment of Cancer Therapy-Head and Neck). A total of 146 patients (78 head and neck and 68 neurologic) provided data for Cohort 1, and 143 (81 head and neck and 62 neurologic) provided data for Cohort 2. Compared with Cohort 1, patients with neurologic cancers in Cohort 2 reported significantly higher scores on the Functional Assessment of Cancer Therapy: General total and emotional quality of life subscale; fewer high scores (≥ 4) on the ESAS breathlessness item; and fewer problems with fears/worries, frustration/anger, finding meaning in life, and worry about friends/family. Head and neck patients in Cohort 2 reported significantly higher emotional quality of life and fewer problems with eating and weight than those in Cohort 1. Although no definitive causal attributions can be made, patients exposed to routine screening for distress reported better well-being and fewer emotional, physical, and practical problems than historical controls.
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:19
Guidelines For Measuring Vital Signs
Before taking a patient's vital signs, a nurse would consider and assess the patient's comfort level and ensure appropriate equipment is available.
 01:25
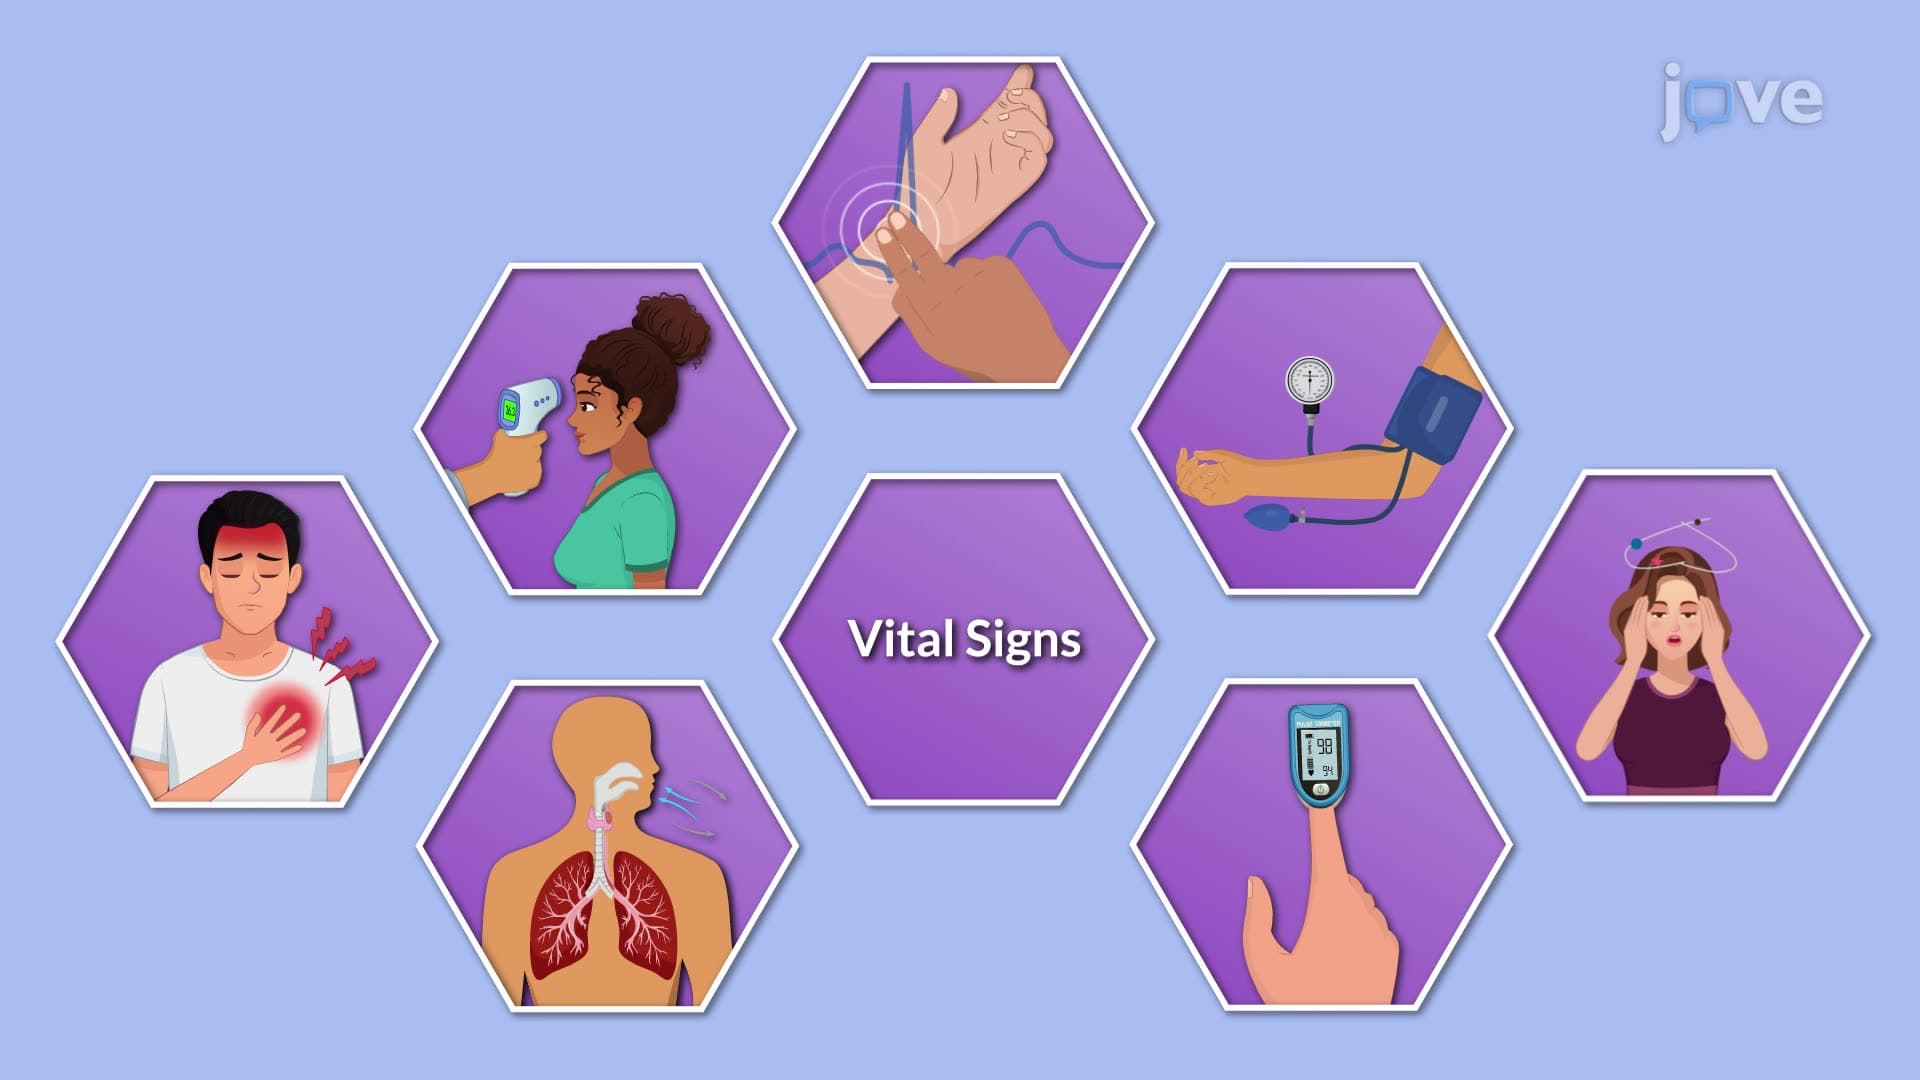
Introduction to Vital Signs
Vital signs help healthcare professionals assess an individual's well-being and detect any functional changes...
 01:22
Aneurysm IV: Nursing Management
 01:15
Techniques of therapeutic communication I: Active Listening, Sharing Observations, Validation, and Using Touch
Therapeutic communication is not the same as social interaction. Social interaction has no goal or purpose and consists of casual information sharing, whereas therapeutic communication has a plan or purpose for the conversation. Therapeutic...
 01:14
SBAR II: Application of SBAR
SBAR Report from a Nurse to a Health Care Provider
S: "Hello, Dr. Smith. This is Jane, RN, from the Med Surg unit. I am calling to tell you about Ms. White in Room 210, who is experiencing increased pain and redness at her incision site. Her recent...