Related Experiment Video
Updated: May 6, 2026
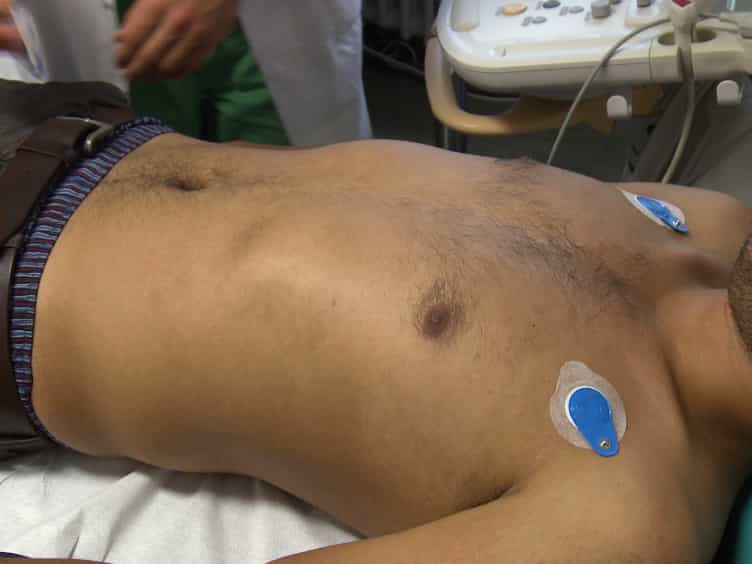

Transthoracic Speckle Tracking Echocardiography for the Quantitative Assessment of Left Ventricular Myocardial Deformation
Published on: October 20, 2016
Global longitudinal strain in patients with suspected heart failure and a normal ejection fraction: does it improve
Pierpaolo Pellicori1, Anna Kallvikbacka-Bennett, Olga Khaleva
1Department of Academic Cardiology, Hull and East Yorkshire Medical Research and Teaching Centre, Castle Hill Hospital, MRTDS (Daisy) Building, Entrance 2, Cottingham, Kingston upon Hull, HU16 5JQ, UK, p.pel@libero.it.

Insights
Global longitudinal strain (GLS) is abnormal in heart failure with preserved ejection fraction (HeFNEF) patients and indicates a worse prognosis. However, GLS is not an independent predictor of adverse outcomes in this population.
Area of Science:
- Cardiology
- Cardiovascular Imaging
- Heart Failure Research
Background:
- Heart failure with preserved ejection fraction (HeFNEF) affects many patients with clinical, structural, or biomarker evidence of heart failure but a normal left ventricular ejection fraction (LVEF).
- Global longitudinal strain (GLS) measurement may provide additional diagnostic and prognostic information in HeFNEF patients.
Purpose of the Study:
- To investigate the role of GLS in patients with symptoms of heart failure and preserved LVEF (≥50%).
- To assess the association between GLS and clinical characteristics, and its prognostic value in HeFNEF.
Main Methods:
- Patients with preserved LVEF were categorized into three groups: no substantial cardiac dysfunction, possible HeFNEF, and definite HeFNEF, based on left atrial diameter (LAD) and amino-terminal pro-brain natriuretic peptide (NTproBNP) levels.
- Global longitudinal strain (GLS) was measured, and clinical data were collected.
- A median follow-up of 647 days was conducted to track cardiovascular death or unplanned heart failure hospitalizations.
Main Results:
- Patients with definite HeFNEF were older, had higher rates of atrial fibrillation, more fluid retention symptoms, right ventricular dysfunction, and elevated pulmonary pressures.
- Mean GLS was significantly less negative in definite HeFNEF patients (-13.6%) compared to possible HeFNEF (-15.2%) and no substantial cardiac dysfunction (-15.9%) groups.
- In univariable analysis, GLS predicted adverse events, but in multivariable analysis, only urea, NTproBNP, left atrial volume, inferior vena cava diameter, and atrial fibrillation were independent predictors.
Conclusions:
- GLS is abnormal in patients with other evidence of HeFNEF, suggesting impaired myocardial function.
- Abnormal GLS is associated with a worse prognosis in the HeFNEF population.
- Despite its association with prognosis, GLS is not a powerful independent predictor of adverse outcomes in HeFNEF when considering other clinical factors.
Abstract:
Many patients have clinical, structural or bio-marker evidence of heart failure (HF) but a normal left ventricular ejection fraction (LVEF; HeFNEF). Measurement of global longitudinal strain (GLS) may add diagnostic and prognostic information. Patients with symptoms suggesting heart failure and LVEF ≥50% were studied: 76 had no substantial cardiac dysfunction (left atrial diameter (LAD) <40 mm and amino-terminal pro-brain natriuretic peptide (NTproBNP) <400 ng/l); 99 had "possible HeFNEF" (LAD ≥40 mm or NTproBNP ≥400 ng/l); and 138 had "definite HeFNEF" (LAD ≥40 mm and NTproBNP ≥400 ng/L). Mean LVEF was 58% in each subgroup. Patients with definite HeFNEF were older, more likely to have atrial fibrillation, had more symptoms and signs of fluid retention, were more likely to have right ventricular dysfunction and had higher pulmonary pressures than other groups. Mean GLS (SD) was less negative in patients with definite HeFNEF (-13.6 (3.0)% vs. possible HeFNEF: -15.2 (3.1)% vs. no substantial cardiac dysfunction: -15.9 (2.4)%; p < 0.001). GLS was -19.1 (2.1)% in 20 controls. During a median follow up of 647 days, cardiovascular death or an unplanned hospitalisation for heart failure occurred in 62 patients. In univariable analysis, GLS but not LVEF predicted events. However, in a multi-variable analysis, only urea, NTproBNP, left atrial volume, inferior vena cava diameter and atrial fibrillation independently predicted adverse outcome. GLS is abnormal in patients who have other evidence of HeFNEF, is associated with a worse prognosis in this population but is not a powerful independent predictor of outcome.
Related Concept Videos
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:17
Pathophysiology of Heart Failure
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:29
Heart Failure II: Pathophysiology
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests