Related Experiment Video
Updated: May 6, 2026


Biotin-based Pulldown Assay to Validate mRNA Targets of Cellular miRNAs
Published on: June 12, 2018
Time and dose-dependent effects of phenobarbital on the rat liver miRNAome
Costas Koufaris1, Jayne Wright, Michael Osborne
1Surgery and Cancer, Imperial College London, SW72AZ, UK; Department of Cytogenetics and Genomics, Cyprus Institute of Neurology and Genetics, Nicosia, Cyprus.

Abstract:
In a previous study we had shown that treatment of male Fischer rats with exogenous chemicals for three months resulted in prominent, mode-of-action dependent effects on liver microRNA (miRNA) (Koufaris et al., 2012). Here we investigated how the effects of chemicals on liver miRNA in male Fischer rats relate to the length and dose of exposure to phenobarbital (PB), a drug with multiple established hepatic effects. Importantly, although acute PB treatment (1-7 days) had significant effects on liver mRNA and the expected effects on the liver phenotype (transient hyperplasia, hepatomegaly, cytochrome P450 induction), limited effects on liver miRNA were observed. However, at 14 days of PB treatment clear dose-dependent effects on miRNA were observed. The main effect of PB treatment from days 1 to 90 on liver miRNA was found to be the persistent, progressive, and highly correlated induction of the miR-200a/200b/429 and miR-96/182 clusters, occurring after the termination of the xenobiotic-induced transient hyperplasia. Moreover, in agreement with their reported functions in the literature we found associations between perturbations of miR-29b and miR-200a/200b by PB with global DNA methylation and zeb1/zeb2 proteins respectively. Our data suggest that miRNA are unlikely to play an important role in the acute responses of the adult rodent liver to PB treatment. However, the miRNA responses to longer PB exposures suggest a potential role for maintaining liver homeostasis in response to sub-chronic and chronic xenobiotic-induced perturbations. Similar studies for more chemicals are needed to clarify whether the temporal and dose pattern of miRNA-toxicant interaction identified here for PB are widely applicable to other xenobiotics.
Insights
Phenobarbital (PB) exposure in male Fischer rats showed limited liver microRNA (miRNA) effects acutely, but dose-dependent changes emerged with longer exposure, suggesting a role in maintaining liver homeostasis. Further research is needed for other chemicals.
Area of Science:
- Toxicology
- Molecular Biology
- Hepatology
Background:
- Previous studies demonstrated chemical-induced liver microRNA (miRNA) alterations in male Fischer rats.
- Phenobarbital (PB) is a drug with known hepatic effects, making it a relevant model for toxicological studies.
Purpose of the Study:
- To investigate the relationship between phenobarbital (PB) exposure duration and dose on liver miRNA in male Fischer rats.
- To understand the temporal dynamics of miRNA responses to xenobiotic exposure.
Main Methods:
- Male Fischer rats were treated with phenobarbital (PB) for varying durations (1-90 days) and doses.
- Liver miRNA and mRNA expression levels were analyzed.
- Liver phenotype, DNA methylation, and zeb1/zeb2 protein levels were assessed.
Main Results:
- Acute PB treatment (1-7 days) caused significant liver mRNA changes and expected phenotypic effects but limited miRNA alterations.
- Dose-dependent changes in liver miRNA were observed after 14 days of PB exposure.
- Long-term PB exposure (up to 90 days) led to persistent induction of miR-200a/200b/429 and miR-96/182 clusters, and associations with DNA methylation and zeb1/zeb2 proteins were found for miR-29b and miR-200a/200b.
Conclusions:
- MicroRNAs (miRNAs) are unlikely to be involved in the acute response of the adult rodent liver to PB.
- The observed miRNA responses to sub-chronic and chronic PB exposure suggest a potential role in maintaining liver homeostasis against xenobiotic-induced perturbations.
- Further studies across various chemicals are necessary to determine if these temporal and dose-dependent miRNA-toxicant interaction patterns are broadly applicable.


Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
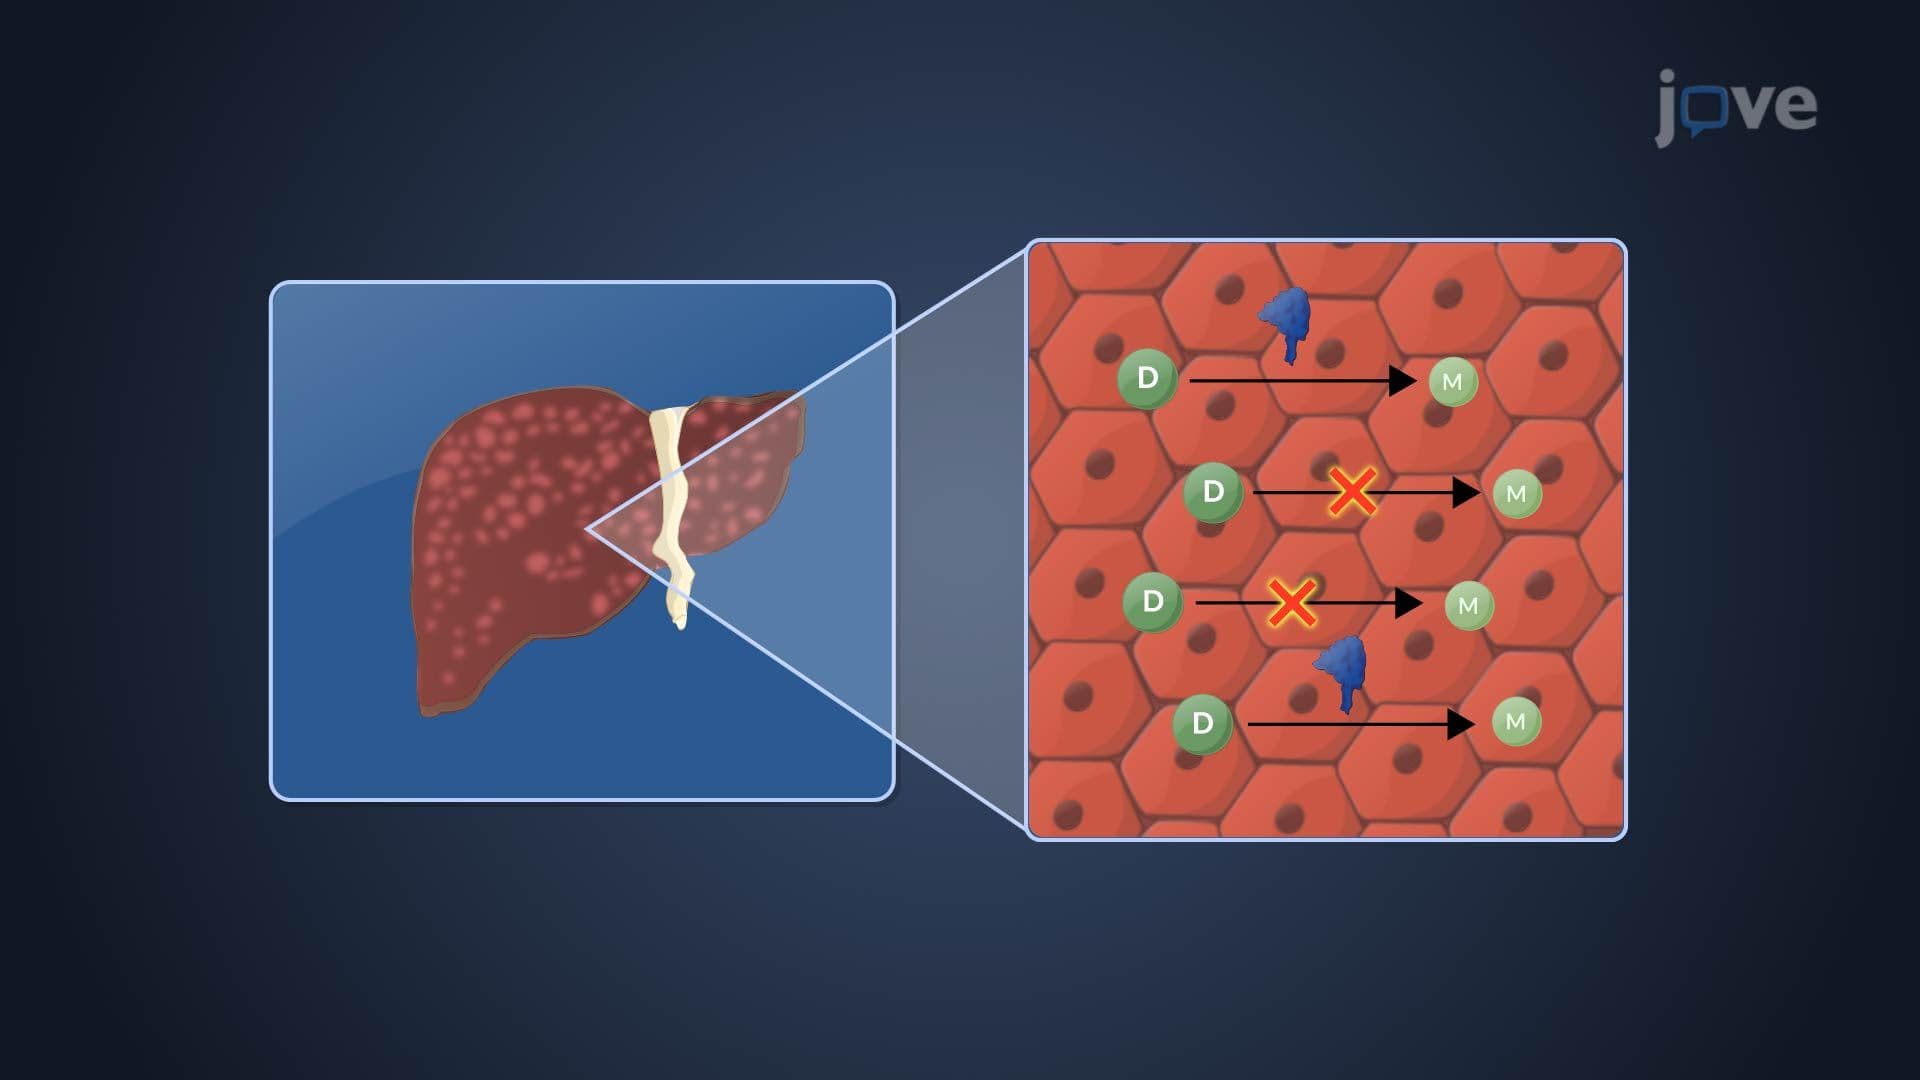
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:19
Phase I Reactions: Oxidation of Aliphatic and Aromatic Carbon-Containing Systems
Oxidation reactions are fundamental in aromatic carbon-containing systems. An example is the hydroxylation of phenobarbital, a process that transforms it into...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment