Related Experiment Video
Updated: May 6, 2026
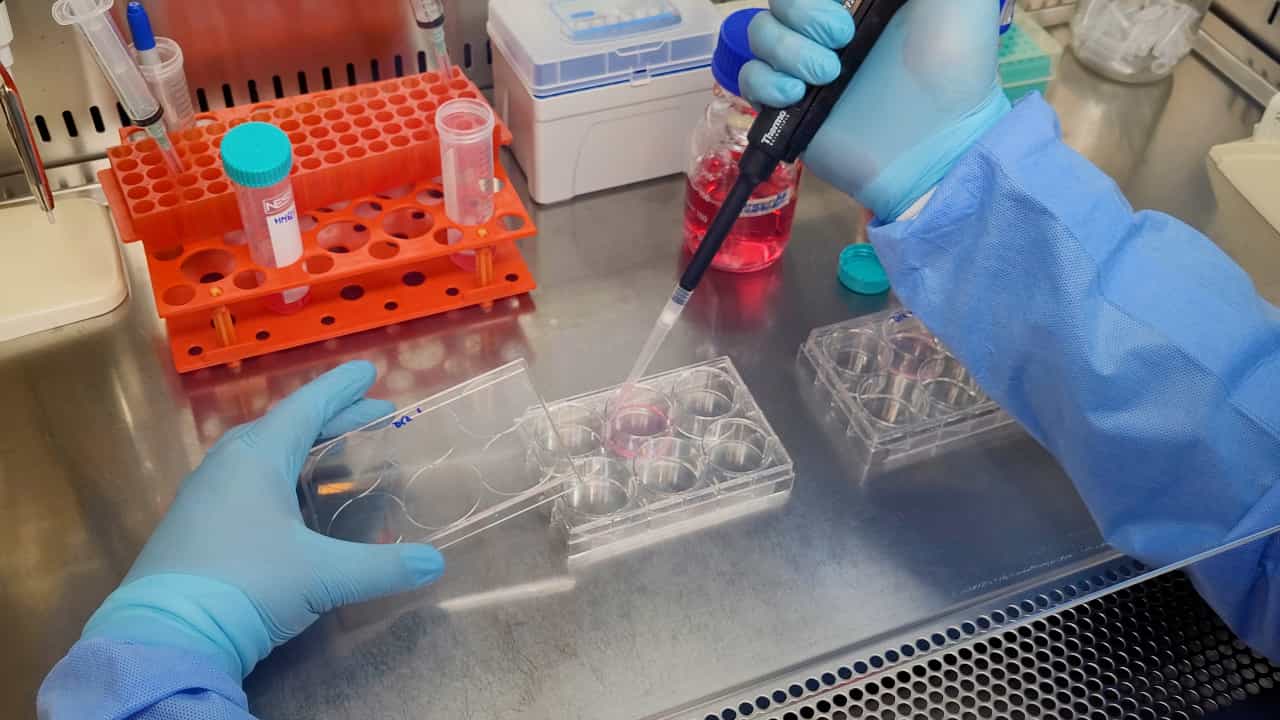

Trophoblast Cell Recovery from Angiogenesis-Tube Formation Assay for Differentiation Marker Expression Analysis
Published on: November 8, 2024
Evidence for extraplacental sources of circulating angiogenic growth effectors in human pregnancy
S Zamudio1, O Kovalenko, L Echalar
1Department of Obstetrics and Gynecology, Division of Maternal-Fetal Medicine and Surgery and the Center for Abnormal Placentation, Hackensack University Medical Center, Hackensack, NJ, USA.

Pregnancy complications such as preeclampsia (PE) and intrauterine growth restriction (IUGR) are associated with reduced blood flow, contributing to placental and fetal hypoxia. Placental hypoxia is thought to cause altered production of angiogenic growth effectors (AGEs), reflected in the circulation of mother and fetus. Vascular endothelial growth factor (VEGF), placental growth factor (PlGF) and their soluble binding protein (sFlt-1) are, in turn, postulated as being causally involved in PE via induction of systemic endothelial cell dysfunction. To dissect the role of AGEs, accurate measurement is of great importance. However, the values of AGEs are highly variable, contributing to heterogeneity in their association (or lack thereof) with preeclampsia. To test the hypothesis that variability may be due to peripheral cell release of AGEs we obtained blood samples from normal healthy pregnant women (n = 90) and the cord blood of a subset of their neonates using standard serum separation and compared results obtained in parallel samples collected into reagents designed to inhibit peripheral cell activation (sodium citrate, theophylline, adenosine and dipyridamole-CTAD). AGEs were measured by ELISA. CTAD collection reduced maternal and fetal free VEGF by 83%, and 98%, respectively. Free PlGF was decreased by 29%, maternal sFlt-1 by >20% and fetal sFlt-1 by 59% in the CTAD-treated vs. serum sample (p < 0.0001). In summary blood collection techniques can profoundly alter measured concentrations of AGEs in mother and fetus. This process is highly variable, contributes to variation reported in the literature, and renders questionable the true impact of alteration in AGEs on pregnancy pathologies.
Pregnancy complications such as preeclampsia (PE) and intrauterine growth restriction (IUGR) are associated with reduced blood flow, contributing to placental and fetal hypoxia. Placental hypoxia is thought to cause altered production of angiogenic growth effectors (AGEs), reflected in the circulation of mother and fetus. Vascular endothelial growth factor (VEGF), placental growth factor (PlGF) and their soluble binding protein (sFlt-1) are, in turn, postulated as being causally involved in PE via induction of systemic endothelial cell dysfunction. To dissect the role of AGEs, accurate measurement is of great importance. However, the values of AGEs are highly variable, contributing to heterogeneity in their association (or lack thereof) with preeclampsia. To test the hypothesis that variability may be due to peripheral cell release of AGEs we obtained blood samples from normal healthy pregnant women (n = 90) and the cord blood of a subset of their neonates using standard serum separation and compared results obtained in parallel samples collected into reagents designed to inhibit peripheral cell activation (sodium citrate, theophylline, adenosine and dipyridamole-CTAD). AGEs were measured by ELISA. CTAD collection reduced maternal and fetal free VEGF by 83%, and 98%, respectively. Free PlGF was decreased by 29%, maternal sFlt-1 by >20% and fetal sFlt-1 by 59% in the CTAD-treated vs. serum sample (p < 0.0001). In summary blood collection techniques can profoundly alter measured concentrations of AGEs in mother and fetus. This process is highly variable, contributes to variation reported in the literature, and renders questionable the true impact of alteration in AGEs on pregnancy pathologies.
More Related Videos
 05:31
Author Spotlight: Modeling an Aspect of Preeclampsia in Female Mice Using Hypoxic Human Placenta-Derived Small Extracellular Vesicles
Published on: January 26, 2024
 12:17
The 4-vessel Sampling Approach to Integrative Studies of Human Placental Physiology In Vivo
Published on: August 2, 2017
Related Concept Videos
 01:24
Regulation of Angiogenesis and Blood Supply
 01:10
Mechanism of Angiogenesis
 01:07
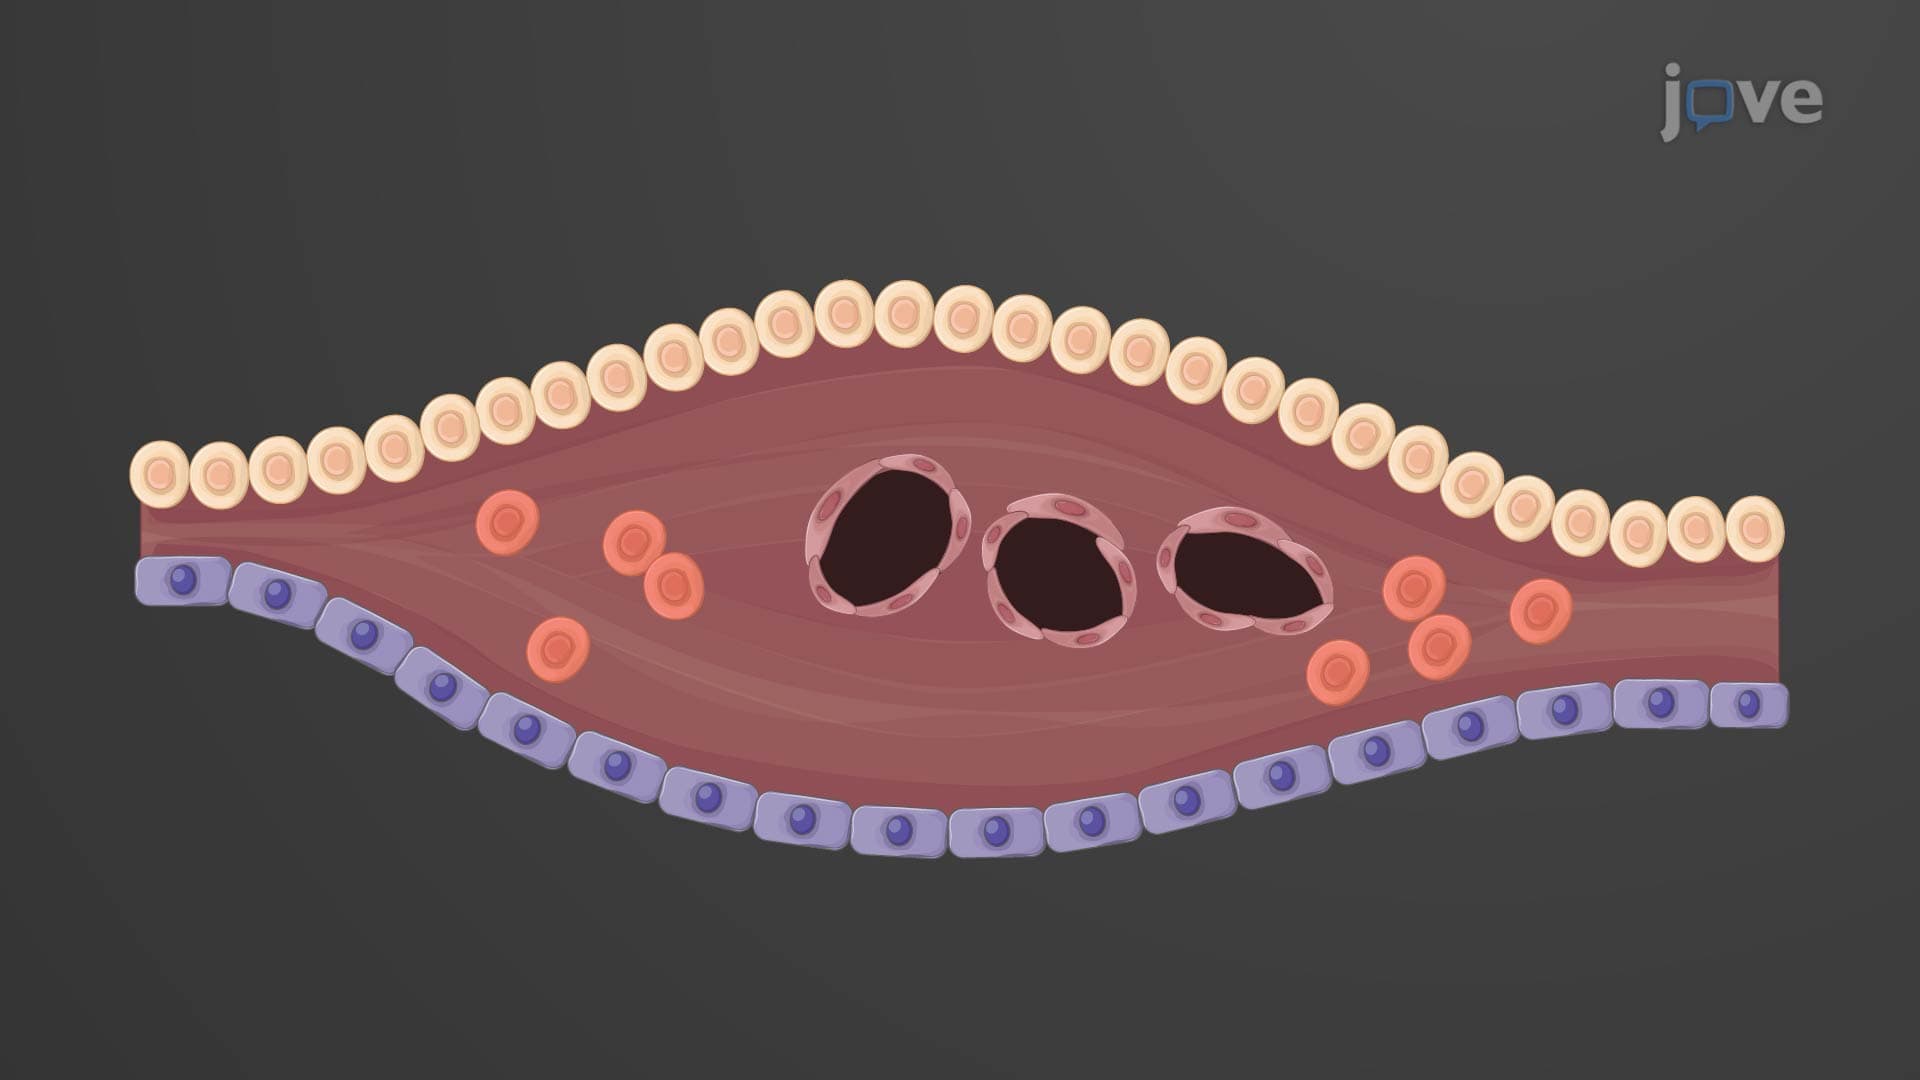
Development of Blood Vessels
The initial formation of this system is facilitated by the small amount of yolk present in the ovum and yolk sac. Blood vessels originate from...