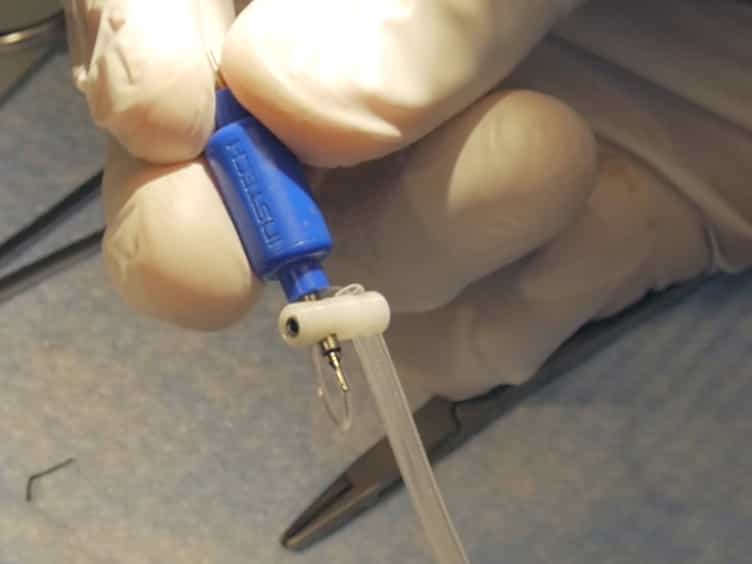

Vancomycin intermittent dosing versus continuous infusion for treatment of ventilator-associated pneumonia in trauma
Thomas M Schmelzer1, A Britton Christmas, H James Norton
1F.H. Sammy Ross, Jr. Trauma Center, Carolinas Medical Center, Charlotte, North Carolina, USA.

Abstract:
Current guidelines for the empiric treatment of ventilator-associated pneumonia (VAP) recommend that vancomycin is dosed 15 mg/kg and administered twice daily for a target trough level of 15 to 20 μg/mL. This study compared conventional intermittent vancomycin infusion (IVI) with continuous vancomycin infusion (CVI). Our prospective, randomized study compared CVI with IVI in trauma patients with suspected VAP. The primary outcome measure was a serum vancomycin level within the target level 48 hours after initiation of therapy. Treatment groups were compared using standard statistical methods. The study included 73 patients, 36 IVI and 37 CVI. Eighteen patients were withdrawn from the study as a result of discontinuation of the drug before 48 hours or failure to draw levels at the appropriate time, resulting in 27 IVI and 28 CVI study patients. There were no differences between treatment groups in gender (P = 0.97), Injury Severity Score (P = 0.70), total body weight (P = 0.36), or age (P = 0.81). The mean serum vancomycin level for the IVI group was 8.9 ± 3.9 μg/mL, and the CVI level was 19.8 ± 6.13 μg/mL (P < 0.0001). Two patients in the IVI group (7.4%) were in the therapeutic range compared with 16 (57.1%) in the CVI group (P < 0.0001). Six patients in the CVI group (21.4%) and none of the IVI patients had supratherapeutic levels. Four patients developed renal insufficiency, three IVI (11.1%) and one CVI (3.6%) (P = 0.36). The current American Trauma Society dosing recommendations for vancomycin for presumptive VAP treatment are inadequate. Continuous vancomycin infusion should be adopted as the standard dosing strategy.
Insights
Continuous vancomycin infusion (CVI) achieved therapeutic serum levels in significantly more patients with ventilator-associated pneumonia (VAP) than intermittent vancomycin infusion (IVI). CVI is recommended as the standard dosing strategy for VAP treatment.
Area of Science:
- Pharmacology
- Critical Care Medicine
- Infectious Diseases
Background:
- Current guidelines recommend vancomycin dosing for ventilator-associated pneumonia (VAP) with a target trough level of 15-20 μg/mL.
- Conventional intermittent vancomycin infusion (IVI) may not consistently achieve therapeutic vancomycin serum levels.
Purpose of the Study:
- To compare the efficacy of continuous vancomycin infusion (CVI) versus IVI in trauma patients with suspected VAP.
- To determine if CVI achieves target serum vancomycin levels more effectively than IVI.
Main Methods:
- A prospective, randomized study comparing CVI and IVI in trauma patients with suspected VAP.
- Serum vancomycin levels were measured 48 hours after therapy initiation.
- Patient demographics and clinical characteristics were recorded and compared between groups.
Main Results:
- Continuous vancomycin infusion (CVI) resulted in significantly higher mean serum vancomycin levels (19.8 μg/mL) compared to intermittent vancomycin infusion (IVI) (8.9 μg/mL).
- Therapeutic vancomycin levels were achieved in 57.1% of CVI patients versus 7.4% of IVI patients (P < 0.0001).
- Renal insufficiency occurred in 3.6% of CVI patients and 11.1% of IVI patients (P = 0.36).
Conclusions:
- Current vancomycin dosing recommendations for VAP are inadequate.
- Continuous vancomycin infusion (CVI) should be adopted as the standard dosing strategy for VAP treatment.
- CVI demonstrates superior efficacy in achieving therapeutic vancomycin levels with comparable safety profiles.
More Related Videos


Related Concept Videos
 01:24
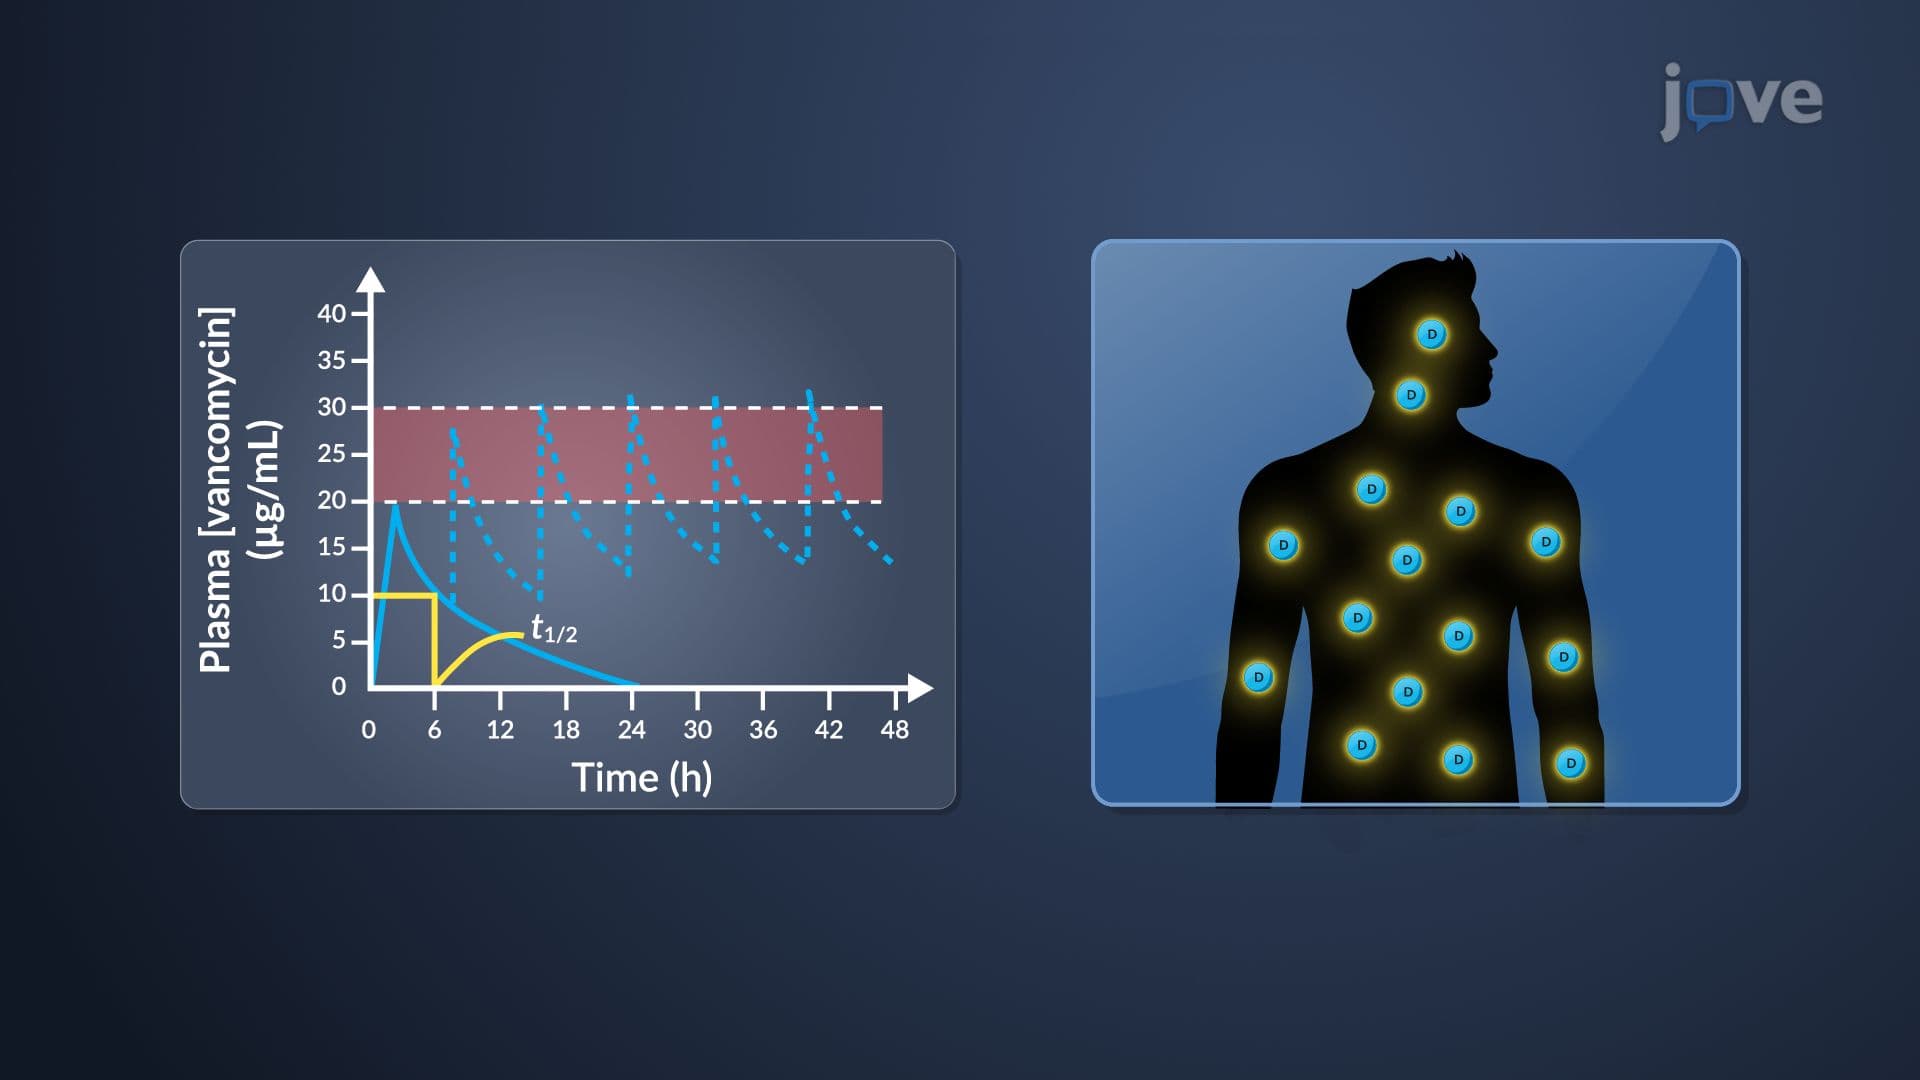
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Continuous Renal Replacement Therapy
 01:19
Dosage Interval and Administration Route: Determination Methods
 01:09
One-Compartment Model: IV Infusion
The one-compartment model for IV infusion uses mathematical equations to describe the rate of change in drug quantity in the body. At steady-state or infusion equilibrium, the drug input...