

Usefulness of echocardiographically guided left ventricular lead placement for cardiac resynchronization therapy in
Josef J Marek1, Samir Saba1, Tetsuari Onishi1
1Heart and Vascular Institute, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania.

Insights
Echocardiography-guided left ventricular lead placement improves cardiac resynchronization therapy outcomes for heart failure patients with narrow QRS or non-LBBB. Precise lead positioning is key for better clinical results in these CRT candidates.
Area of Science:
- Cardiology
- Medical Imaging
- Heart Failure Management
Background:
- Current cardiac resynchronization therapy (CRT) guidelines prioritize patients with QRS width ≥150 ms and left bundle branch block (LBBB).
- Optimal left ventricular (LV) lead positioning is crucial for CRT efficacy, but guidance methods vary, especially for non-standard candidates.
Purpose of the Study:
- To evaluate the benefit of echocardiography-guided LV lead positioning using speckle tracking in heart failure patients with QRS width <150 ms or non-LBBB.
- To compare clinical outcomes between echocardiographically guided and routine LV lead implantation in this specific patient subgroup.
Main Methods:
- Substudy of the STARTER prospective randomized controlled trial involving 151 patients.
- Patients randomized to LV lead implantation guided by speckle tracking radial strain to the site of latest mechanical activation versus routine implantation.
- Primary endpoint: heart failure hospitalization or death within 2 years.
Main Results:
- Patients with QRS 120-149 ms or non-LBBB receiving echocardiographically guided CRT showed favorable outcomes, similar to standard CRT candidates.
- Conversely, patients with QRS 120-149 ms or non-LBBB and remote LV leads experienced unfavorable outcomes (HR 5.45, HR 4.92).
- Significant interaction between LV lead position and outcomes observed (p=0.038, p=0.008).
Conclusions:
- Echocardiographically guided LV lead positioning is associated with significantly improved clinical outcomes in heart failure patients with QRS duration <150 ms and/or non-LBBB.
- This technique optimizes CRT benefits beyond current guideline criteria.
- Further prospective studies are recommended to confirm these findings.
Abstract:
The current guidelines most strongly support cardiac resynchronization therapy (CRT) for patients with heart failure with a QRS width of ≥150 ms and left bundle branch block (LBBB). Our objective was to assess the potential benefit of echocardiographically guided left ventricular (LV) lead positioning for patients with a QRS width <150 ms or non-LBBB as a substudy of the Speckle Tracking Assisted Resynchronization Therapy for Electrode Region (STARTER) prospective, randomized controlled trial. The STARTER trial randomized 187 patients with heart failure, a QRS of ≥120 ms, and ejection fraction of ≤35% to LV lead guided to the site of latest mechanical activation by speckle tracking radial strain versus routine implantation. The predefined primary end point was heart failure hospitalization or death within 2 years. This substudy included 151 CRT patients with matching echocardiographic and LV lead position data and complete follow-up data. Patients with a QRS width of 120 to 149 ms or non-LBBB and LV lead concordant or adjacent to the site of latest mechanical activation had favorable outcomes after CRT similar to those with LBBB or a QRS width of ≥150 ms. In contrast, patients with a QRS of 120 to 149 ms or non-LBBB and remote LV leads had unfavorable outcomes (hazard ratio 5.45, 95% confidence interval 2.36 to 12.6, p <0.001, and hazard ratio 4.92, 95% confidence interval 2.12 to 11.39, p <0.001, respectively, with significant interaction after adjusting for baseline variables, p = 0.038 and p = 0.008). In conclusion, LV lead positioning with respect to the echocardiographic site of latest activation was significantly associated with more favorable clinical outcomes in patients with a QRS duration <150 ms and/or non-LBBB. Additional prospective study is warranted.
More Related Videos
 10:17
Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
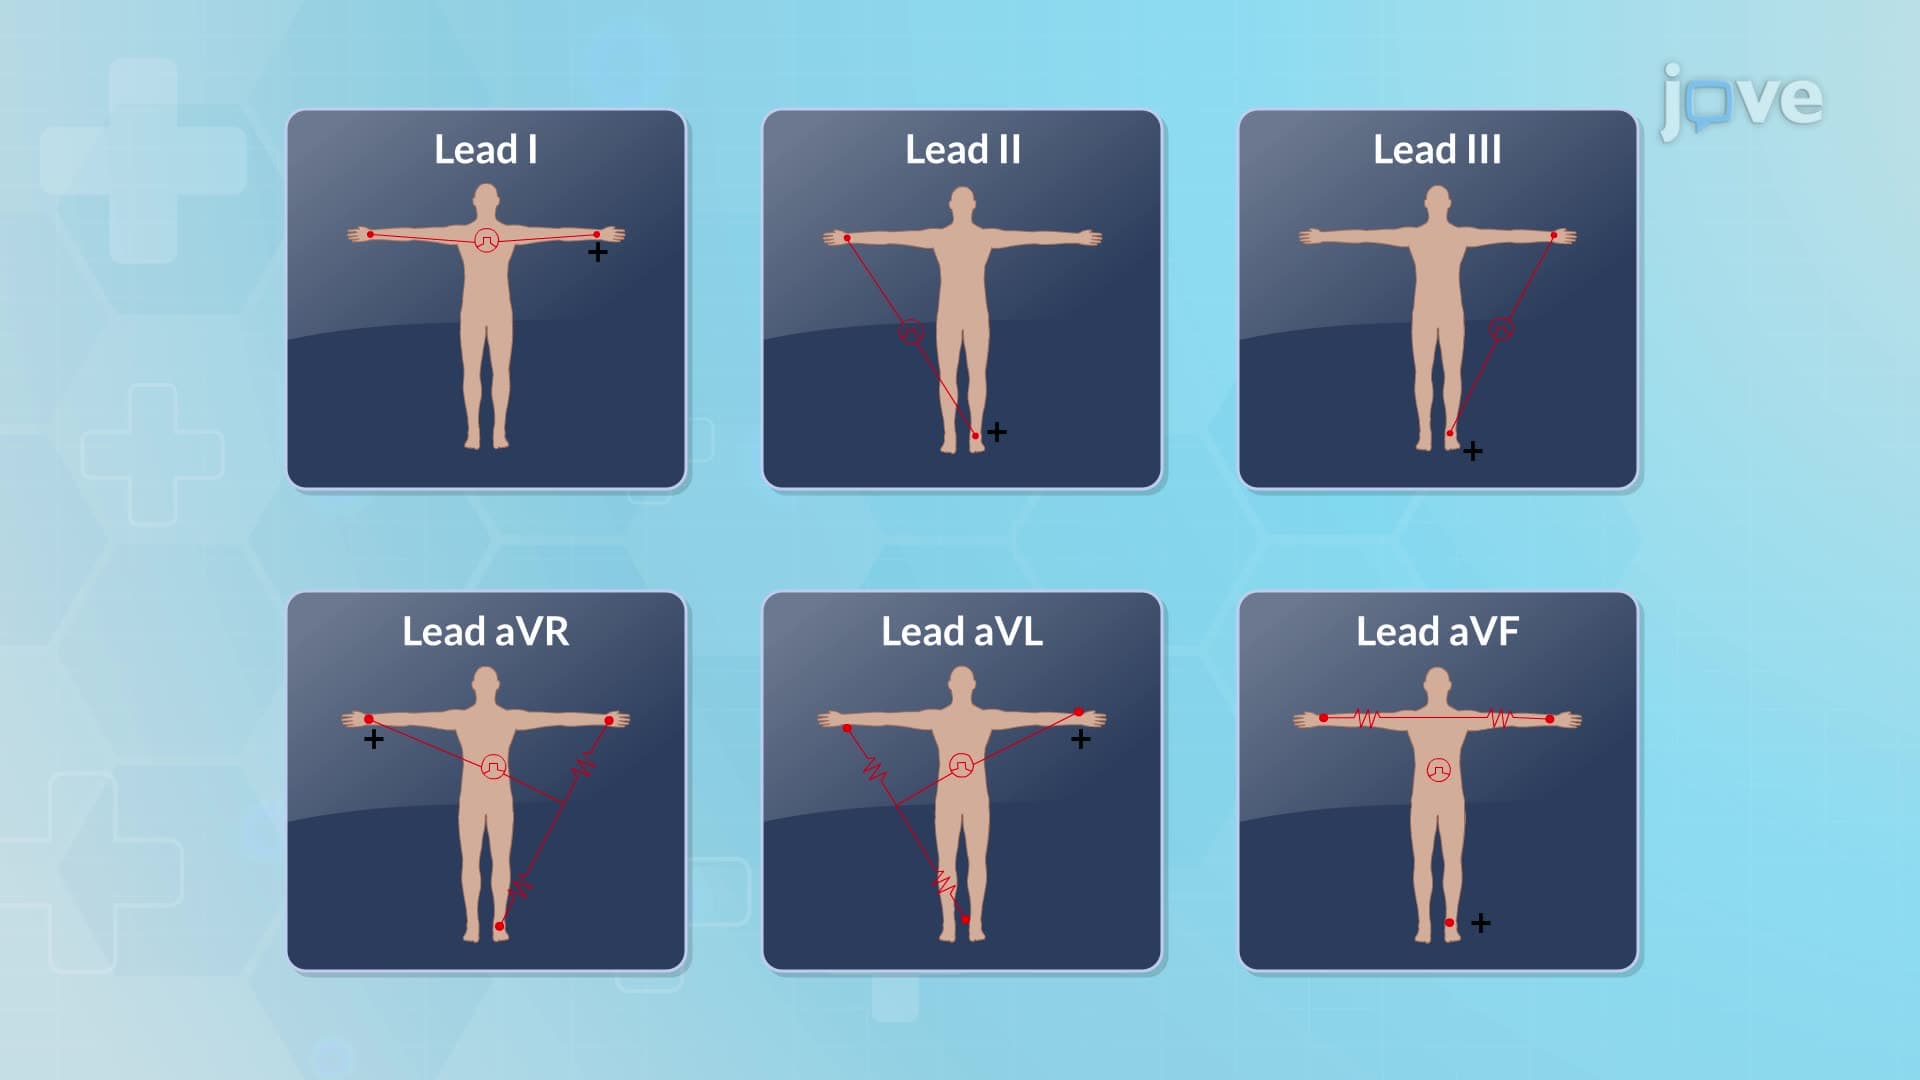 01:28
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...
 01:24
Cardiac Catheterization III: Left Heart Catheterization