Related Experiment Video
Updated: May 6, 2026
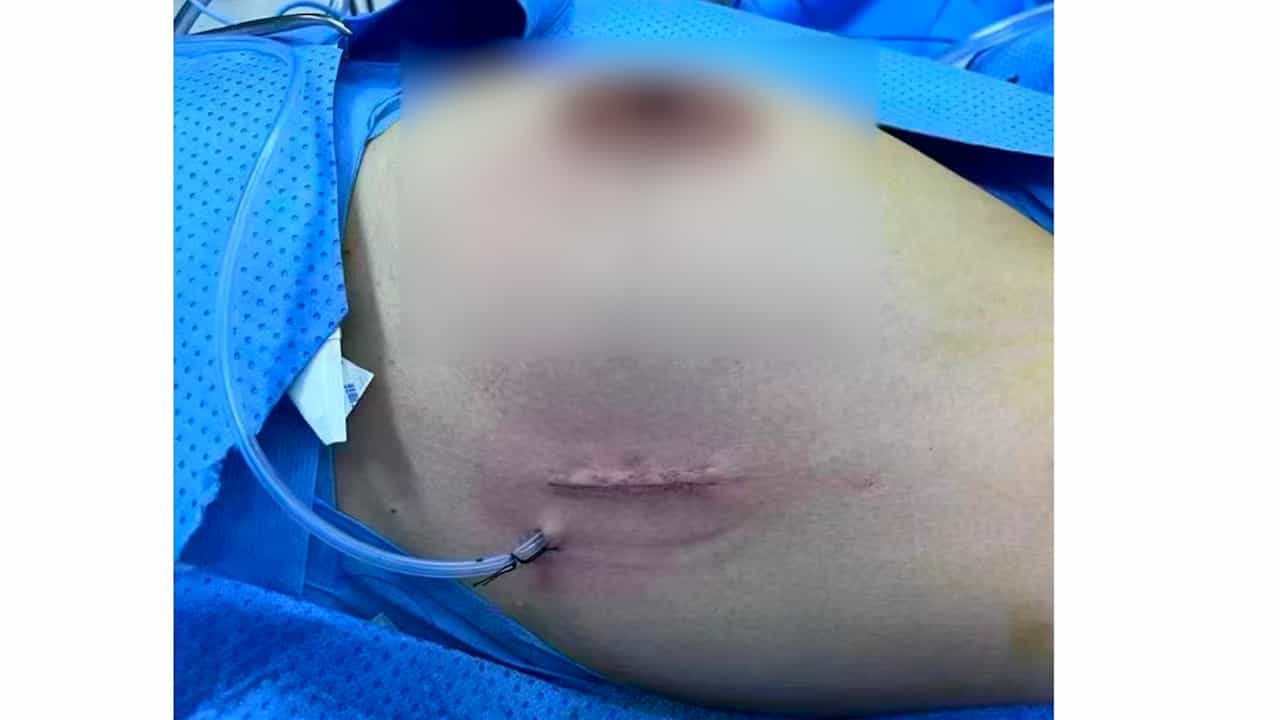

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Validity of using lobe-specific regional lymph node stations to assist navigation during lymph node dissection in
Shinichiro Miyoshi1, Kazuhiko Shien, Shinichi Toyooka
1Department of General Thoracic Surgery, Okayama University Graduate School of Medicine, Dentistry and Pharmaceutical Sciences, 2-5-1 Shikata-cho, Kita-ku, Okayama, 700-8558, Japan, smiyoshi@md.okayama-u.ac.jp.

Purpose:
The validity of our proposed lobe-specific regional lymph node stations (LSRLNS) was evaluated as a method for navigation during lymphadenectomy in patients with early stage non-small cell lung cancer (NSCLC).
Methods:
A total of 725 NSCLC patients with c-T2N1M0 or less extensive disease who had undergone a curative operation with complete mediastinal lymph node dissection (MLND) were studied. The LSRLNS were #2, #3, #4 and #10 for the right upper lobe, #11i, #11s, #7 and #8 for the right lower lobe, #4, #5 and #6 for the left superior division, #11, #5 and #7 for the left lingular division and #11, #7 and #8 for the left lower lobe.
Results:
If the LSRLNS were used for pathological examinations during surgery, 599 p-N0 and 39 p-N1 patients diagnosed with no metastasis would have been subjected to a selective MLND, while 20 p-N1 and 65 p-N2 patients who had a diagnosis of metastasis would have been navigated to a complete MLND. Two p-N2 patients with a diagnosis of no metastasis would have inappropriately undergone a selective MLND, resulting in the false negative rate at 0.3 %.
Conclusion:
Intra-operative pathological examination using our LSRLNS may accurately reveal the status of metastasis, and appropriately lead to a selective or complete MLND in patients with c-T2N1M0 or less extensive disease.