Related Experiment Video
Updated: Aug 2, 2026


Hyperinsulinemic-euglycemic Clamps in Conscious, Unrestrained Mice
Published on: November 16, 2011
Aprotinin induced lipohypertrophy and glomerulonephritis in an insulin dependent diabetic

In an insulin dependent diabetic who was hyperglycaemic and ketotic despite 3,000 u of insulin injected subcutaneously in 2 divided doses daily, 50 u of intravenous insulin infused over 24 hr restored normal glucose homeostasis. A combination of insulin (800 u) and aprotinin (10,000 u) given twice daily also produced adequate glucose homeostasis for a period of 12 months. The patient then developed local hypertrophy of subcutaneous tissue at the injection site and her diabetic control deteriorated. Non-selective proteinuria followed and she developed nephrotic syndrome. Renal biopsy revealed a membraneous glomerulonephritis with subepithelial immune complexes, appearances consistent with a drug-induced glomerulonephritis. Withdrawal of aprotinin led to a gradual remission of nephrotic syndrome and proteinuria over several months. During this period, her diabetes was well controlled with continuous subcutaneous infusion of insulin at a dose of 500 u/24 hr. This case report demonstrates: the effective use of aprotinin for prolonged periods in insulin dependent diabetics with abnormal absorption of subcutaneously injected insulin; aprotinin induced lipohypertrophy which was not observed when insulin was injected alone; aprotinin-associated glomerulonephritis and nephrotic syndrome; the effective use of CSII--at higher insulin doses--in such patients with subcutaneous malabsorption of insulin.
In an insulin dependent diabetic who was hyperglycaemic and ketotic despite 3,000 u of insulin injected subcutaneously in 2 divided doses daily, 50 u of intravenous insulin infused over 24 hr restored normal glucose homeostasis. A combination of insulin (800 u) and aprotinin (10,000 u) given twice daily also produced adequate glucose homeostasis for a period of 12 months. The patient then developed local hypertrophy of subcutaneous tissue at the injection site and her diabetic control deteriorated. Non-selective proteinuria followed and she developed nephrotic syndrome. Renal biopsy revealed a membraneous glomerulonephritis with subepithelial immune complexes, appearances consistent with a drug-induced glomerulonephritis. Withdrawal of aprotinin led to a gradual remission of nephrotic syndrome and proteinuria over several months. During this period, her diabetes was well controlled with continuous subcutaneous infusion of insulin at a dose of 500 u/24 hr. This case report demonstrates: the effective use of aprotinin for prolonged periods in insulin dependent diabetics with abnormal absorption of subcutaneously injected insulin; aprotinin induced lipohypertrophy which was not observed when insulin was injected alone; aprotinin-associated glomerulonephritis and nephrotic syndrome; the effective use of CSII--at higher insulin doses--in such patients with subcutaneous malabsorption of insulin.


Related Concept Videos
 01:25
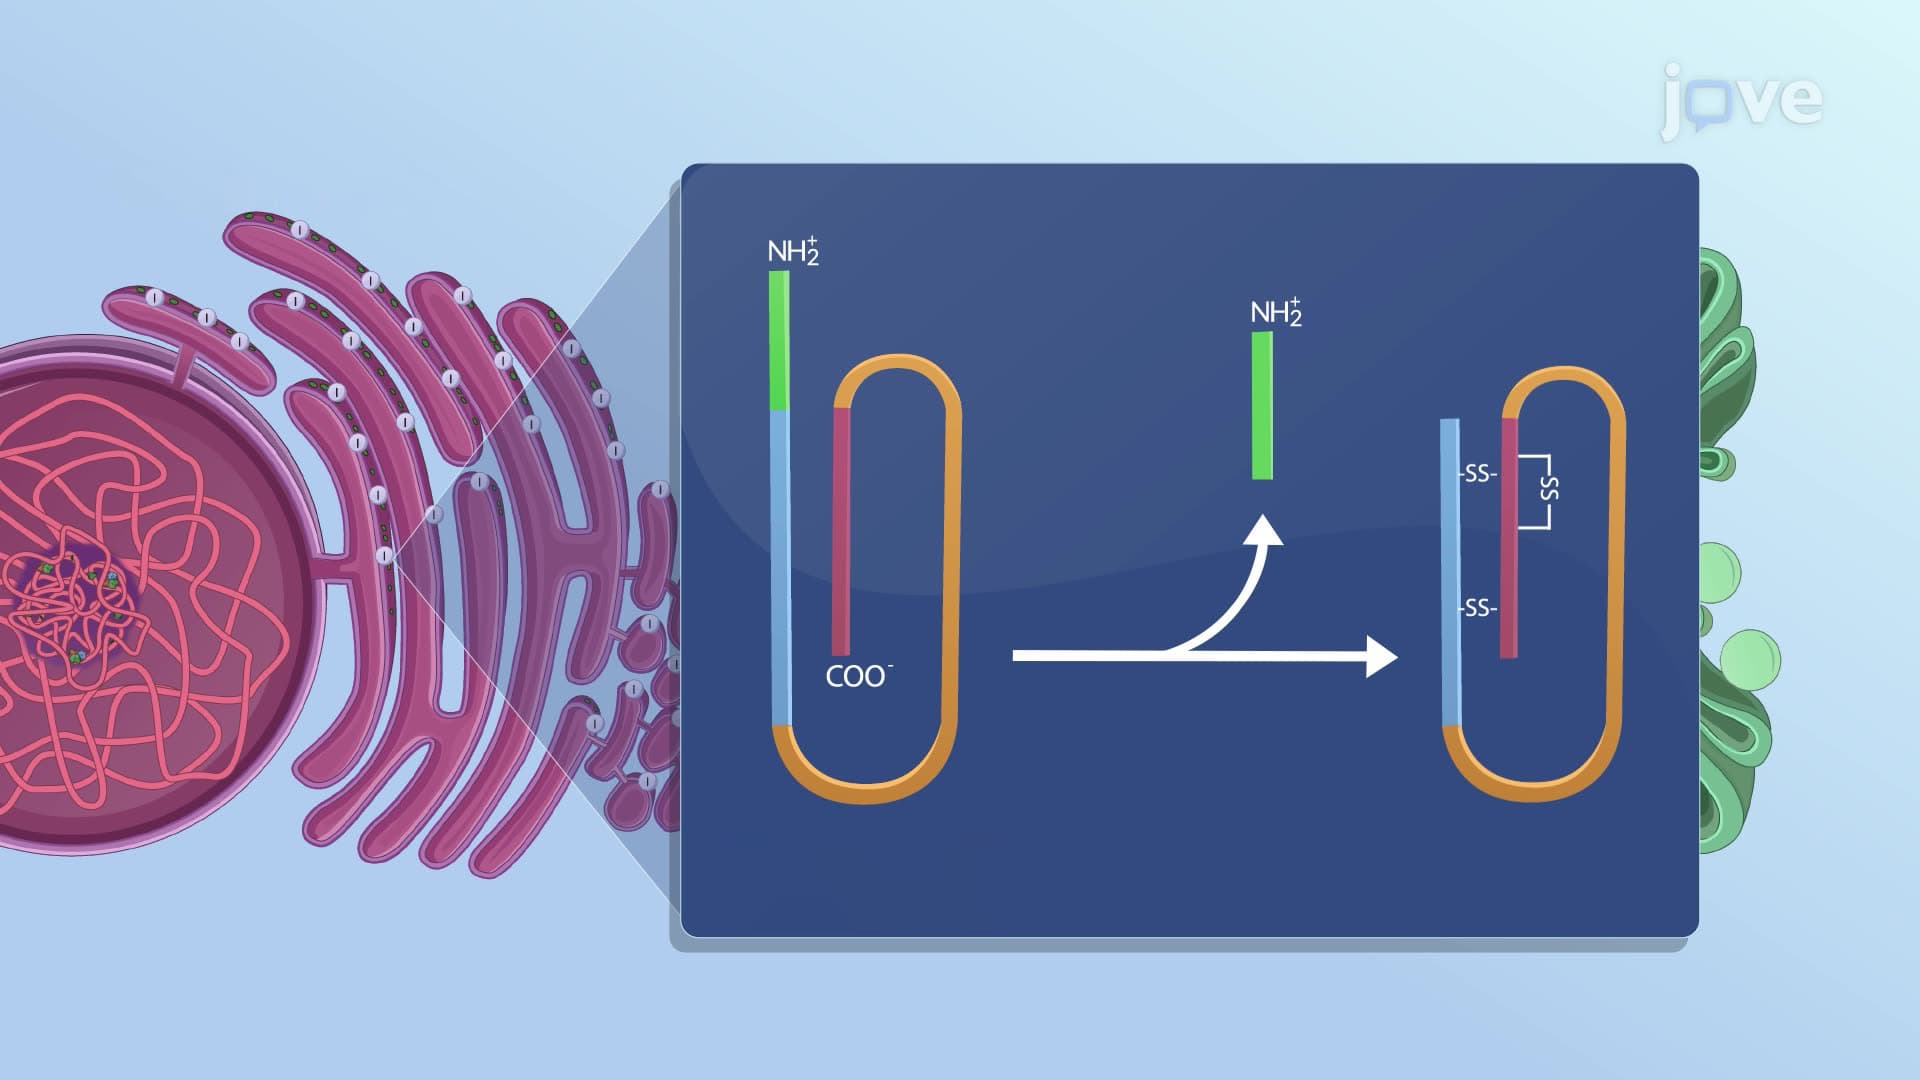
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:26
Type I Diabetes II: Pathophysiology
 01:24
Type II Diabetes II: Pathophysiology
 01:28
Diabetic Nephropathy