Related Experiment Video
Updated: May 6, 2026


Real-Time, Semi-Automated Fluorescent Measurement of the Airway Surface Liquid pH of Primary Human Airway Epithelial Cells
Published on: June 13, 2019
History of medical understanding and misunderstanding of Acid base balance
Christopher Geoffrey Alexander Aiken1
1MA MD MRCP FRACP, Neonatal Unit, Labcare Pathology, Pharmacy and Medical Records, Taranaki Base Hospital, New Plymouth, New Zealand.

Abstract:
To establish how controversies in understanding acid base balance arose, the literature on acid base balance was reviewed from 1909, when Henderson described how the neutral reaction of blood is determined by carbonic and organic acids being in equilibrium with an excess of mineral bases over mineral acids. From 1914 to 1930, Van Slyke and others established our acid base principles. They recognised that carbonic acid converts into bicarbonate all non-volatile mineral bases not bound by mineral acids and determined therefore that bicarbonate represents the alkaline reserve of the body and should be a physiological constant. They showed that standard bicarbonate is a good measure of acidosis caused by increased production or decreased elimination of organic acids. However, they recognised that bicarbonate improved low plasma bicarbonate but not high urine acid excretion in diabetic ketoacidosis, and that increasing pCO2 caused chloride to shift into cells raising plasma titratable alkali. Both indicate that minerals influence pH. In 1945 Darrow showed that hyperchloraemic metabolic acidosis in preterm infants fed milk with 5.7 mmol of chloride and 2.0 mmol of sodium per 100 kcal was caused by retention of chloride in excess of sodium. Similar findings were made but not recognised in later studies of metabolic acidosis in preterm infants. Shohl in 1921 and Kildeberg in 1978 presented the theory that carbonic and organic acids are neutralised by mineral base, where mineral base is the excess of mineral cations over anions and organic acid is the difference between mineral base, bicarbonate and protein anion. The degree of metabolic acidosis measured as base excess is determined by deviation in both mineral base and organic acid from normal.


Related Concept Videos
 01:29
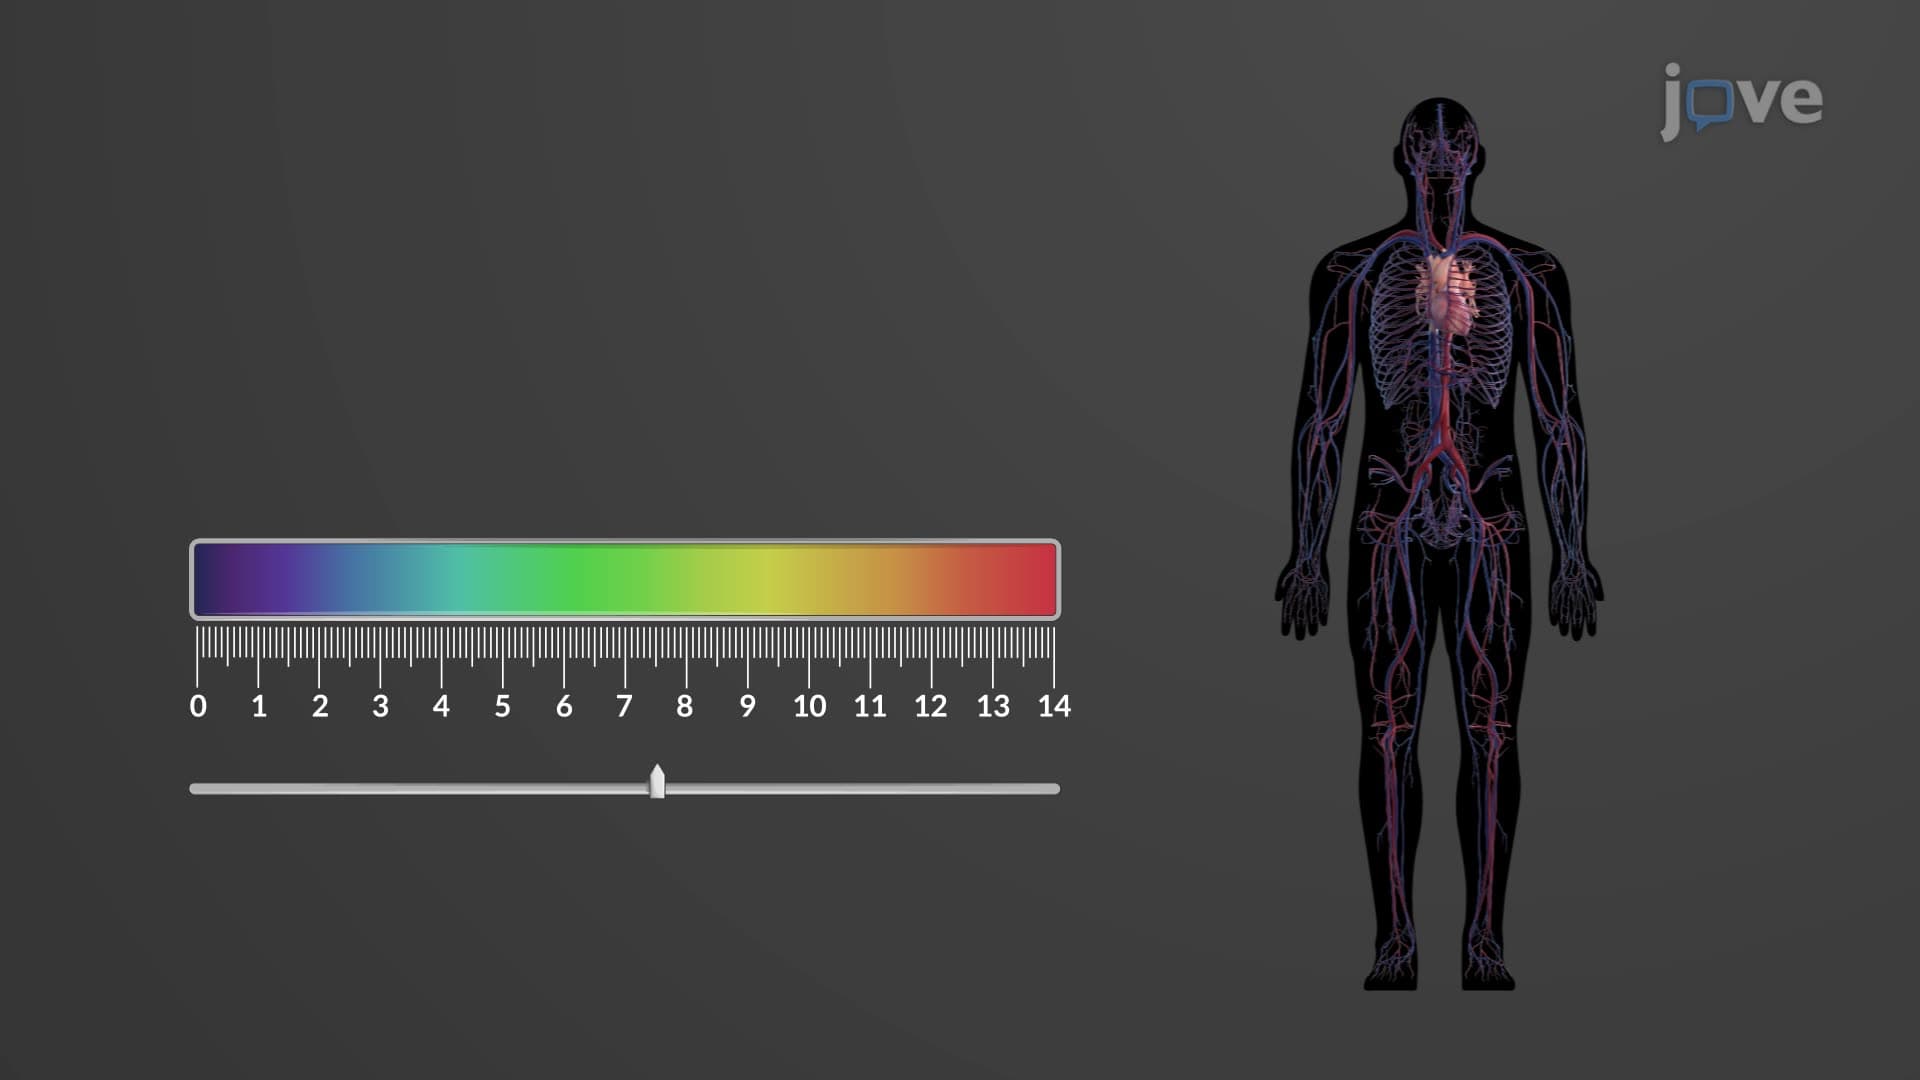
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 02:58
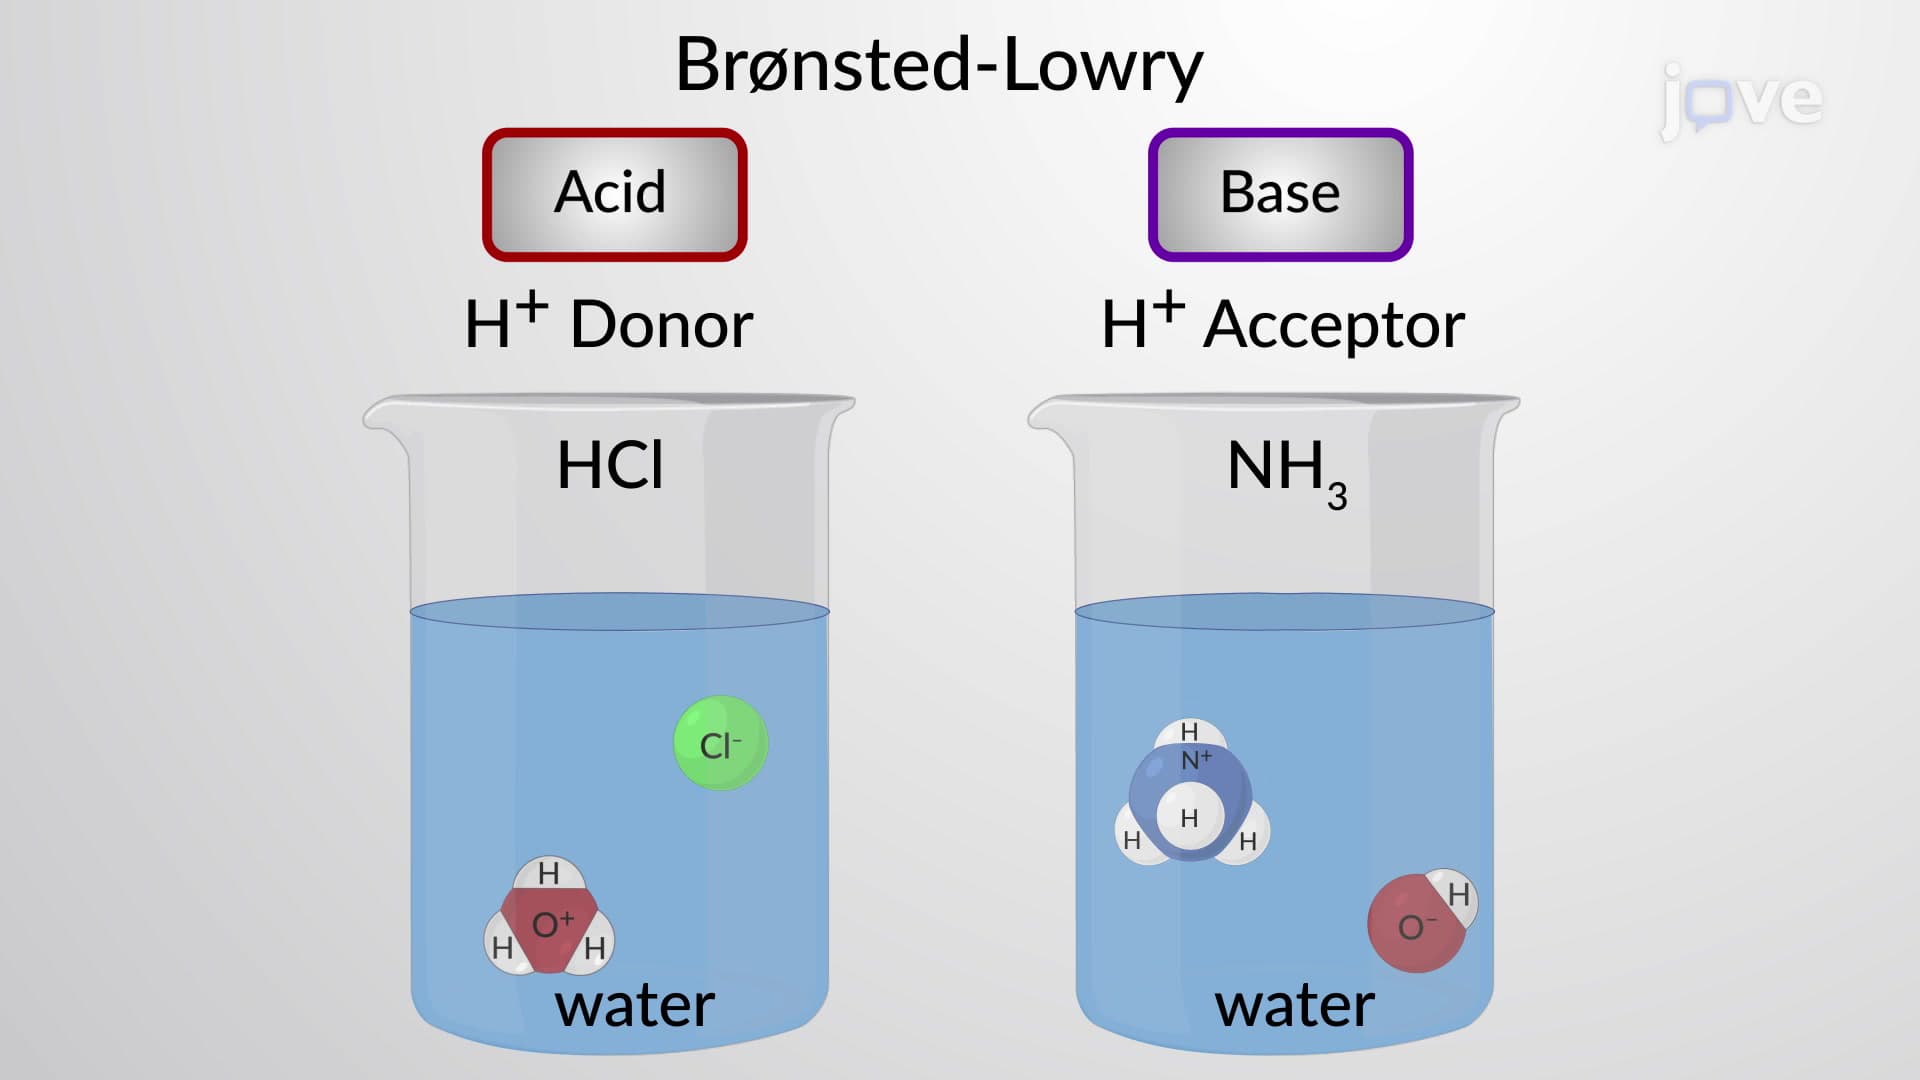
Bronsted-Lowry Acids and Bases
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are...
 01:28
Compensation Mechanisms
Respiratory Compensation
This mechanism addresses metabolic-induced pH imbalances by adjusting breathing rates. Respiratory compensation begins within minutes of detecting a pH...