Related Experiment Video
Updated: May 6, 2026
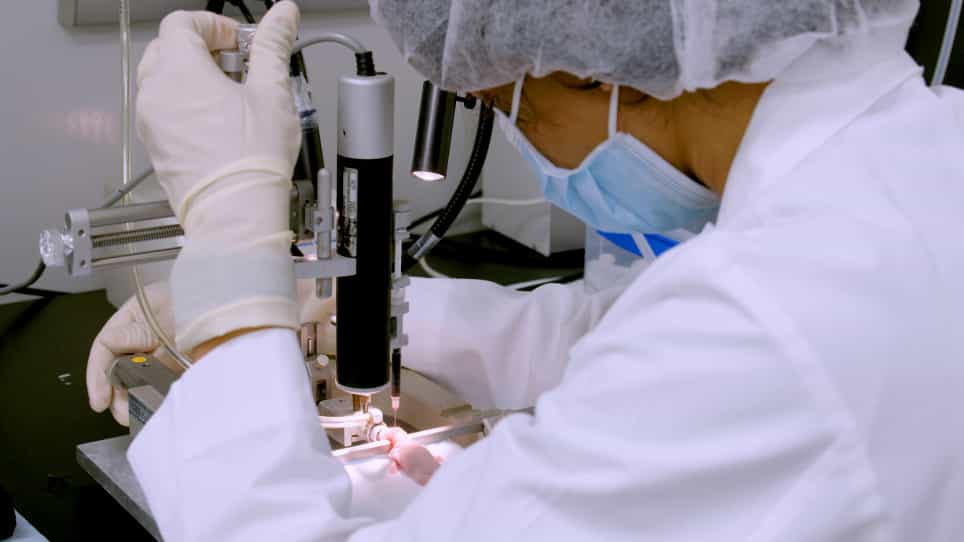

Modeling Neonatal Intraventricular Hemorrhage Through Intraventricular Injection of Hemoglobin
Published on: August 25, 2022
Changes in cardiac function and cerebral blood flow in relation to peri/intraventricular hemorrhage in extremely
Shahab Noori1, Michael McCoy2, Michael P Anderson3
1Division of Neonatology and the Center for Fetal and Neonatal Medicine, Department of Pediatrics, Children's Hospital Los Angeles and the LAC+USC Medical Center, Keck School of Medicine, University of Southern California, Los Angeles, CA.

Insights
Changes in cardiac function and cerebral blood flow (CBF) precede peri/intraventricular hemorrhage (P/IVH) in preterm infants. Monitoring these parameters may help identify high-risk neonates before bleeding occurs.
Area of Science:
- Neonatal physiology
- Cardiovascular research
- Neurology
Background:
- Peri/intraventricular hemorrhage (P/IVH) is a significant complication in extremely preterm infants.
- Early detection of risk factors for P/IVH is crucial for timely intervention.
Purpose of the Study:
- To determine if alterations in cardiac function and cerebral blood flow (CBF) precede P/IVH in extremely preterm neonates.
- To assess the potential of monitoring cardiac function and CBF for predicting P/IVH.
Main Methods:
- Prospective observational study of 22 preterm infants (23-27 weeks gestational age).
- Cardiac function, CBF, and P/IVH assessed via ultrasound every 12 hours.
- Continuous monitoring of cerebral regional oxygen saturation (rSO2) and cerebral fractional oxygen extraction.
Main Results:
- Infants who developed P/IVH showed decreased left ventricular output, stroke volume, and cerebral rSO2, with increased cerebral fractional oxygen extraction within the first 12 hours.
- These hemodynamic and CBF changes preceded the ultrasonographic detection of P/IVH.
- Myocardial performance index and middle cerebral artery flow velocity also differed between groups by 28 hours.
Conclusions:
- Cardiac function and CBF are stable in preterm neonates without P/IVH in the first 3 postnatal days.
- In neonates who develop P/IVH, reduced systemic perfusion and CBF, followed by an increase, precede hemorrhage.
- Monitoring cardiac function and cerebral rSO2 may identify infants at high risk for P/IVH development.
Objective:
To investigate whether changes in cardiac function and cerebral blood flow (CBF) precede the occurrence of peri/intraventricular hemorrhage (P/IVH) in extremely preterm infants.
Study Design:
In this prospective observational study, 22 preterm infants (gestational age 25.9 ± 1.2 weeks; range 23-27 weeks) were monitored between 4 and 76 hours after birth. Cardiac function and changes in CBF and P/IVH were assessed by ultrasound every 12 hours. Changes in CBF were also followed by continuous monitoring of cerebral regional oxygen saturation (rSO2) and by calculating cerebral fractional oxygen extraction.
Results:
Five patients developed P/IVH (1 patient grade II and 4 patients grade IV). Whereas measures of cardiac function and CBF remained unchanged in neonates without P/IVH, patients with P/IVH tended to have lower left ventricular output and had lower left ventricle stroke volume and cerebral rSO2 and higher cerebral fractional oxygen extraction during the first 12 hours of the study. By 28 hours, these variables were similar in the 2 groups and myocardial performance index was lower and middle cerebral artery mean flow velocity higher in the P/IVH group. P/IVH was detected after these changes occurred.
Conclusions:
Cardiac function and CBF remain stable in very preterm neonates who do not develop P/IVH during the first 3 postnatal days. In very preterm neonates developing P/IVH during this period, lower systemic perfusion and CBF followed by an increase in these variables precede the development of P/IVH. Monitoring cardiac function and cerebral rSO2 may identify infants at higher risk for developing P/IVH before the bleeding occurs.
More Related Videos


Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology