Related Experiment Video
Updated: May 6, 2026
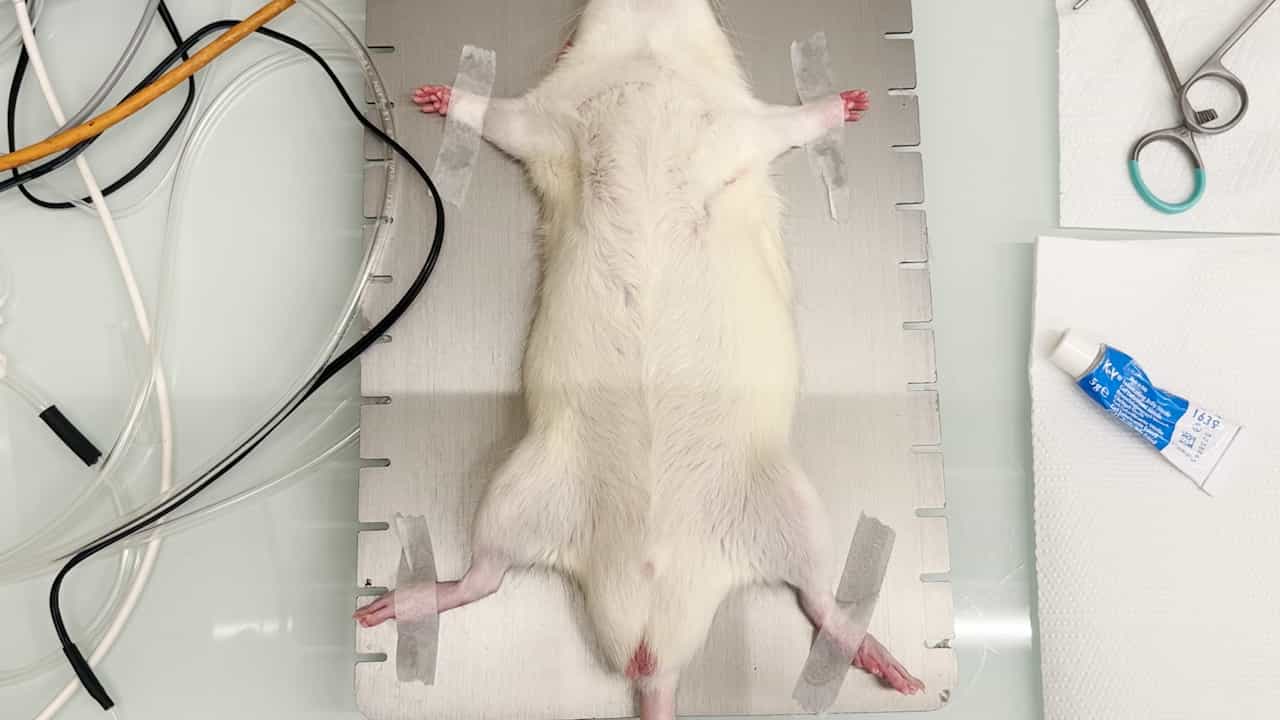
A Model of Acute Lung Injury Following Visceral Ischemia-Reperfusion by Supra-Coeliac Aortic Cross Clamping in Rats
Published on: August 15, 2025
Suprarenal fixation resulting in intestinal ischemia after endovascular aortic aneurysm repair
Robert A Pol1, Frederick Keus2, Ted R Prins3
1Division of Vascular Surgery, Department of Surgery, University Medical Center Groningen, University of Groningen, Groningen, The Netherlands.

Abstract:
Endovascular aneurysm repair (EVAR) may be associated with specific stent- and procedure-related complications. Hepatic artery anatomic variability may lead to dramatic consequences when unanticipated. A 64-year-old man presented with a 6-cm abdominal aortic aneurysm, suitable for an EVAR procedure. The EVAR procedure was uneventful and the patient was discharged after 2 days. After 2 weeks, he was readmitted for recurrent upper abdominal pain due to acute cholecystitis. The postoperative EVAR computed tomography scan was revisited and the suprarenal bare-metal stent of the Zenith device overlapped the highly calcified origin of both the superior mesenteric artery (SMA) and the celiac trunk. Moreover, the patient appeared to have a right replaced hepatic artery originating from the SMA. He developed diffuse, patchy ischemia of both the large and the entire small bowel, and quickly became unresponsive to vasopressor drugs. He died shortly thereafter. An EVAR procedure may result in a highly complicated course when hepatic artery anatomic variability is present. Fenestrated EVAR or proximal graft scallops should be considered for cases in which the proximal sealing zone is diseased and flow to visceral vessels is compromised.


Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Aneurysm I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology