Related Experiment Video
Updated: May 6, 2026
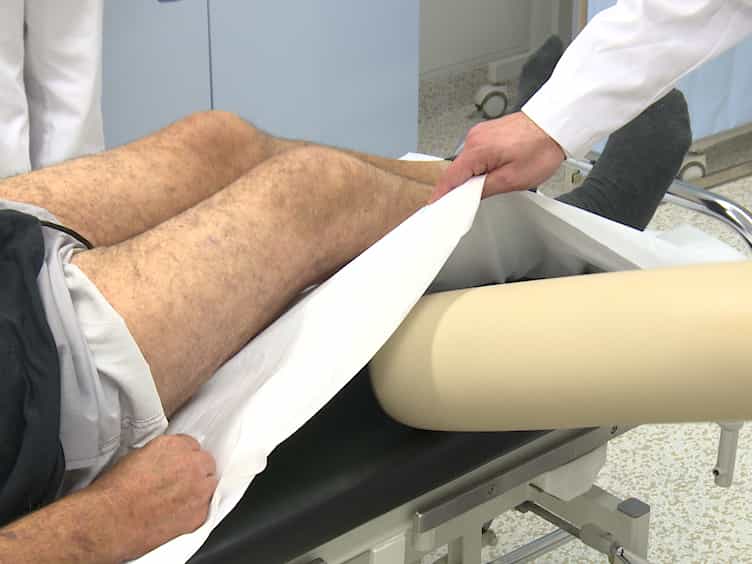

Novel Diagnostics in Revision Arthroplasty: Implant Sonication and Multiplex Polymerase Chain Reaction
Published on: December 3, 2017
Periprosthetic joint infections treated with two-stage revision over 14 years: an evolving microbiology profile
Benjamin T Bjerke-Kroll1, Alexander B Christ1, Alexander S McLawhorn1
1Hospital for Special Surgery, New York, New York.

Abstract:
Late periprosthetic joint infection (PJI) occurs in 0.3%-1.7% of total hip arthroplasties (THAs) and 0.8%-1.9% of total knee arthroplasties (TKAs). Surgical debridement, explant, and appropriate antibiotics are imperative for successful treatment. We analyzed organisms from PJIs at one institution for temporal trends over 14 years. Poisson regression model demonstrated a linear increase in infection rate for the following bacteria as the primary organism: MRSA (incidence rate ratio [IRR] = 1.11, P = 0.019), Streptococcus viridans (IRR = 1.18, P = 0.002), and Propionibacterium acnes (IRR = 1.21, P = 0.024). The increase in proportion of these organisms may warrant further discussion on pre-surgical MRSA screening and empiric therapy to include MRSA coverage, increased incubation time to detect P. acnes, and dental prophylaxis against S. viridans.
Insights
Late periprosthetic joint infections (PJI) are increasing, particularly those caused by MRSA, Streptococcus viridans, and Propionibacterium acnes. This trend necessitates updated screening and treatment strategies for joint replacement infections.
Area of Science:
- Orthopedic Surgery
- Infectious Diseases
- Microbiology
Background:
- Late periprosthetic joint infection (PJI) affects 0.3%-1.9% of total hip and knee arthroplasties.
- Effective PJI treatment requires surgical intervention and targeted antibiotics.
Purpose of the Study:
- To analyze temporal trends of causative organisms in PJI over 14 years at a single institution.
- To identify shifts in bacterial prevalence contributing to late PJI.
Main Methods:
- Retrospective analysis of PJI cases over a 14-year period.
- Statistical analysis using a Poisson regression model to assess infection rate trends.
- Identification and categorization of bacterial organisms responsible for PJI.
Main Results:
- A significant linear increase in PJI rates was observed for Methicillin-resistant Staphylococcus aureus (MRSA) (IRR=1.11, P=0.019).
- Incidence rate ratios also increased for Streptococcus viridans (IRR=1.18, P=0.002) and Propionibacterium acnes (IRR=1.21, P=0.024).
- These specific bacteria showed a concerning rise as primary causative agents in PJI.
Conclusions:
- The increasing prevalence of MRSA, S. viridans, and P. acnes in PJI warrants re-evaluation of current management protocols.
- Consideration should be given to pre-surgical MRSA screening and empiric antibiotic regimens covering MRSA.
- Extended incubation periods for bacterial culture and dental prophylaxis against S. viridans may be beneficial.

Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:28
Microbiota of the Urogenital Tract
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:29
Staphylococcal Skin Infections
 01:18
Endocarditis III: Medical Management