Related Experiment Video
Updated: May 6, 2026

Author Spotlight: A Reproductive Hysteroscopy Approach for Complete Endometrial Polyp Removal and Enhanced Endometrial Receptivity
Published on: August 2, 2024
[Prevention of the complications related to hysteroscopy: guidelines for clinical practice]
X Deffieux1, T Gauthier, N Ménager
1Service de gynécologie-obstétrique et médecine de la reproduction, hôpital Antoine-Béclère, 157, rue de la Porte-de-Trivaux, 92140 Clamart, France.

Objective:
To provide clinical practice guidelines (CPGs) from the French college of obstetrics and gynecology (CNGOF), based on the best evidence available, concerning the adverse events related to hysteroscopy.
Materials And Methods:
Review of literature using following Keywords: hysteroscopy; vaginoscopy; infection; perforation; intrauterine adhesions
Results:
Vaginoscopy should be the standard technique for outpatient hysteroscopy (grade A) using a miniature (≤ 3.5mm sheath) (grade A) rigid hysteroscope (grade C), using normal saline solution distension medium (grade C), without any anesthesia (conscious sedation should not be routinely used), without cervical preparation (grade B), without vaginal disinfection and without antibiotic prophylaxy (grade B). Misoprostol (grade A), vaginal estrogens (grade C), or GnRH agonist routine administration is not recommended before operative hysteroscopy. Before performing hysteroscopy, it is important to purge the air out of the system (grade A). The uterine cavity distention pressure should be maintained below the mean arterial pressure and below 120 mmHg. The maximum fluid deficit of 2000 mL is suggested when using normal saline solution and 1000 mL is suggested when using hypotonic solution. When uterine perforation is recognized during operative hysteroscopy using monopolar or bipolar loop, the procedure should be stopped and a laparoscopy should be performed in order to eliminate a bowel injury. Diagnostic or operative hysteroscopy is allowed when an endometrial cancer is suspected (grade B).
Conclusion:
Implementation of this guideline should decrease the prevalence of complications related to office and operative hysteroscopy.
More Related Videos
 05:21
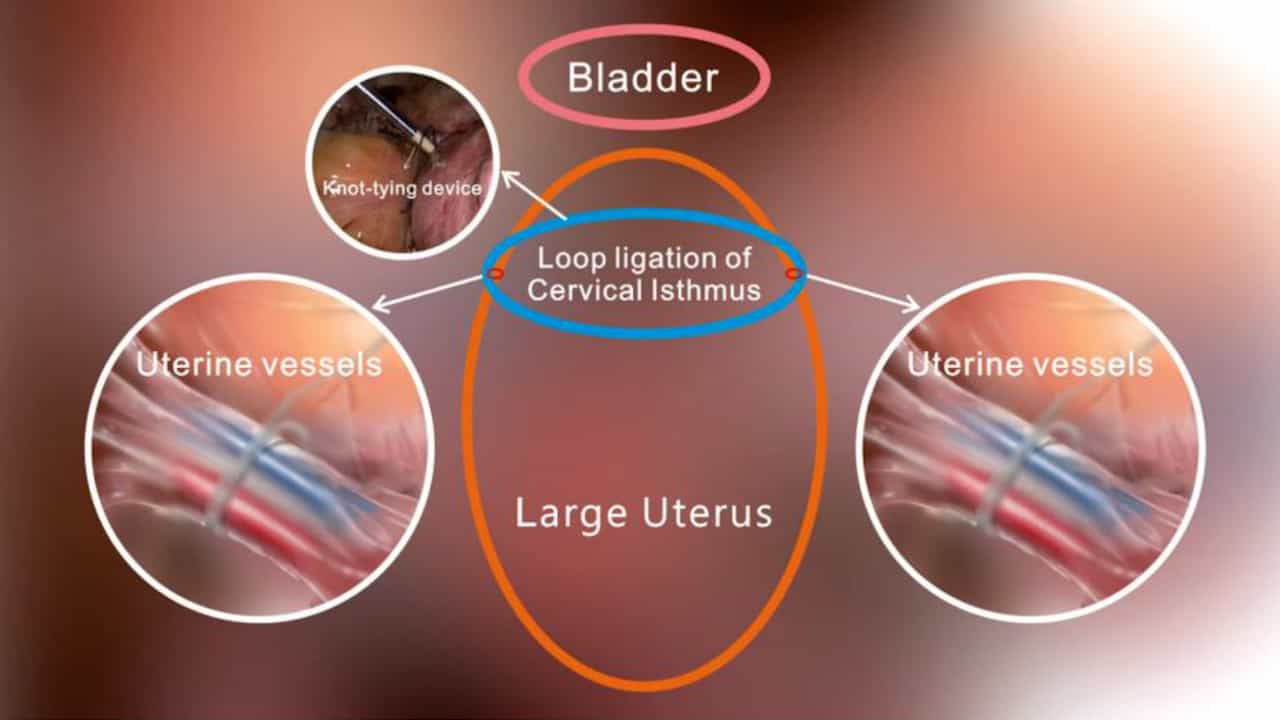
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
 11:29
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: