Related Experiment Video
Updated: May 6, 2026
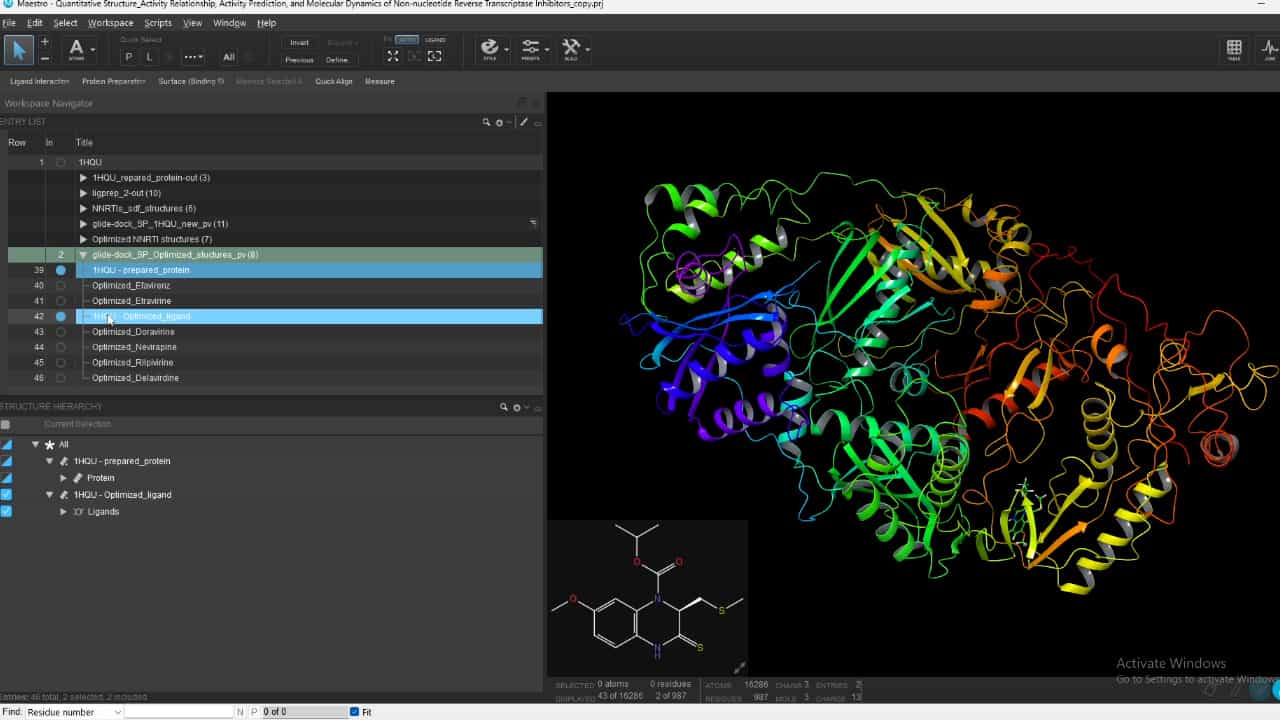
Quantitative Structure-Activity Relationship, Activity Prediction, and Molecular Dynamics of Non-nucleotide Reverse Transcriptase Inhibitors
Published on: May 9, 2025
Characterization of associations and development of atazanavir resistance after unplanned treatment interruptions
W Tinago1, J A O'Halloran, R M O'Halloran
1HIV Molecular Research Group, School of Medicine and Medical Science, University College Dublin, Dublin, Ireland; Department of Community Medicine, College of Health Sciences, University of Zimbabwe, Harare, Zimbabwe.

Objectives:
Although current guidelines recommend resistance testing prior to antiretroviral therapy (ART) reinitiation after treatment interruptions, virological failure of first-line ritonavir-boosted, protease-inhibitor (PI/r)-containing ART is associated with low emergent PI resistance. In patients experiencing unscheduled treatment interruptions (UTrIs) on ritonavir-boosted atazanavir (ATV/r) ART regimens, we hypothesized low emergence of PI mutations conferring resistance to ATV/r.
Methods:
In a retrospective assessment of HIV-infected patients initiating ATV/r-containing ART, using logistic regression we determined factors associated with UTrI, the prevalence of emergent resistance mutations and virological response after ART reinitiation.
Results:
A total of 202 patients [median age 33 years (interquartile range (IQR) 29-40 years); 52% female; median CD4 count 184 cells/μL (IQR 107-280 cells/μL); median HIV RNA 4.6 log10 HIV-1 RNA copies/mL (IQR 3.2-5.1 copies/mL)] initiated ATV/r between 2004 and 2009; 80 (43%) were ART naïve. One hundred and ten patients (55%) underwent 195 UTrIs after a median (IQR) 25 (10-52) weeks on ART, with a median (IQR) UTrI duration of 10 (3-31) weeks. Fifty-four of 110 patients (49%) underwent more than one UTrI. The commonest reasons for UTrI were nonadherence (52.7%) and drug intolerance (20%). Baseline HIV RNA > 100 000 copies\mL [odds ratio (OR) 3.6; 95% confidence interval (CI) 1.3-9.95] and being HCV positive, an injecting drug user or on methadone (OR 2.4; 95% CI 1.3-4.4) were independently associated with UTrI. In 39 patients with at least two resistance assays during UTrIs, 72 new mutations emerged; four nucleoside reverse transcriptase inhibitor (NRTI), two nonnucleoside reverse transcriptase inhibitor (NNRTI) and 66 protease inhibitor (PI) resistance mutations. All emergent PI resistance mutations were minor mutations. At least 65% of patients were re-suppressed on ATV/r reinitiation.
Conclusions:
In this PI-treated cohort, UTrIs are common. All emergent PI resistance mutations were minor and ATV/r retained activity and efficacy when reintroduced, even after several UTrIs, raising questions regarding the need for routine genotypic resistance assays in PI/r-treated patients prior to ART reinitiation after UTrI.

Related Concept Videos
 01:10
Retrovirus Life Cycles
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:30
Development of Antibiotic Resistance
 01:25
Clinical Significance of Antibiotic Resistance
 01:16
Drug toxicity: Idiosyncratic Reactions