Related Experiment Video
Updated: May 6, 2026
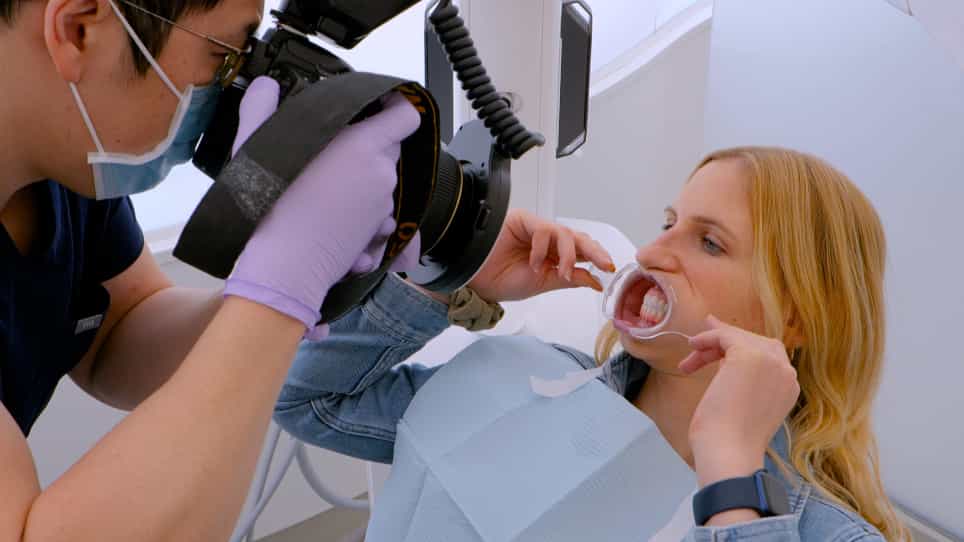
A Standardized Approach to Extra-Oral and Intra-Oral Digital Photography
Published on: July 22, 2022
Cultural differences in clinical leadership: a qualitative study comparing the attitudes of general dental
P Brocklehurst1, M Nomura, T Ozaki
1Dental Public Health, Department of Dental Public Health, University of Manchester, Manchester, UK.

Background And Aims:
Leadership has been argued to be a key component in the transformation of services in the United Kingdom and in Japan. In the UK, local professional networks have developed to provide clinician led care in dentistry; working to develop local plans to deliver improvements in the quality of care for patients. In Japan, the remuneration model for dental care has been revised with the aim to improve the service and tackle the current challenges of population health there. The aim of this study was to use semi-structured interviews and thematic analysis to explore general dental practitioners' (GDPs) understanding of the term 'leadership' and determine whether its meaning is culturally bound.
Methods:
Twelve participants were sampled purposively by the research team; identifying GDPs involved in leadership roles from across Greater Manchester and Tokyo. A set of open-ended questions was developed for semi-structured interviews a priori and the interviews continued until saturation. Interviews were recorded, transcribed verbatim and codes were developed into a coding frame for thematic analysis. Representative quotations are provided in the results.
Results:
Fourteen codes were identified according to the aims of the study and organised into five overarching themes. 'Leadership as the relationship' was more pronounced among Japanese GDPs, while 'leadership as the individual' was common in GDPs from Greater Manchester. Differences were also found in respect of education and training in leadership. Training was also considered to be important by the GDPs from Japan, while UK GDPs felt leaders were more likely to be influenced by innate qualities. The interdependence of leadership and entrepreneurship was raised by both sets of GDPs.
Conclusion:
The concept of leadership was considered to be important by GDPs from both Greater Manchester and Tokyo; leadership was seen as providing strategy and direction for a clinical team. However, cultural influences were evident in how this was conceptualised.
Related Concept Videos
 01:26
Self-Esteem and Culture
 01:08
Obedience
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...
 01:27
Levels of Communication II: Organizational, Public, and Group Dynamics
 01:27
Ethical Issues
Ethical Concerns in Healthcare:
 01:26
Cultural Influences on Personality