Related Experiment Video
Updated: May 5, 2026

Author Spotlight: Enhancing Graft Viability Assessment Through Quantitative Metrics and Innovative Reservoir Systems
Published on: August 2, 2024
The effect of the prone maximal restraint position with and without weight force on cardiac output and other
Davut J Savaser1, Colleen Campbell, Edward M Castillo
1Department of Emergency Medicine, University of California, San Diego School of Medicine, San Diego, CA, USA.

Background:
The prone maximal restraint (PMR) position has been used by law enforcement and emergency care personnel to restrain acutely combative or agitated individual. The position places the subject prone with wrists handcuffed behind the back and secured to the ankles. Prior work has indicated a reduction in inferior vena cava (IVC) diameter associated with this position when weight force is applied to the back. It is therefore possible that this position can negatively impact hemodynamic stability.
Objectives:
We sought to measure the impact of PMR with and without weight force on measures of cardiac function including vital signs, oxygenation, stroke volume (SV), IVC diameter, cardiac output (CO) and cardiac index (CI).
Methods:
We conducted a randomized prospective cross-over experimental study of 25 healthy male volunteers (22-43 years of age) placed in 5 different body positions: supine (SU), prone (PR), prone maximal restraint with no weight force (PMR-0), prone maximal restraint with 50 lbs added to the subject's back (PMR-50), and prone maximal restraint with 100 lbs added to the subject's back (PMR-100) for 3 min. Heart rate (HR), blood pressure (BP), and oxygenation saturation (O2 sat) were monitored. In addition, echocardiography was performed to measure left ventricular outflow tract diameter (LVOTD), and SV, CO, and CI were then calculated. Data were analyzed using repeated measures ANOVA with pair-wise comparisons when appropriate to evaluate changes with each variable with respective positioning.
Results:
Despite a small decrease in SV between SU and PMR positions, there were no statistically significant differences in CO between the 5 different positions. There were also no differences in CI between positions other than a small decrease when comparing SU and PMR-50 only (mean difference -0.39 L/stroke, p = 0.005). There was no evidence of hemodynamic compromise in any of the PMR positions when evaluating HR, MAP or O2 sat.
Conclusions:
PMR with and without weight force did not result in any changes in CO or other evidence of cardiovascular or hemodynamic compromise.

Related Concept Videos
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
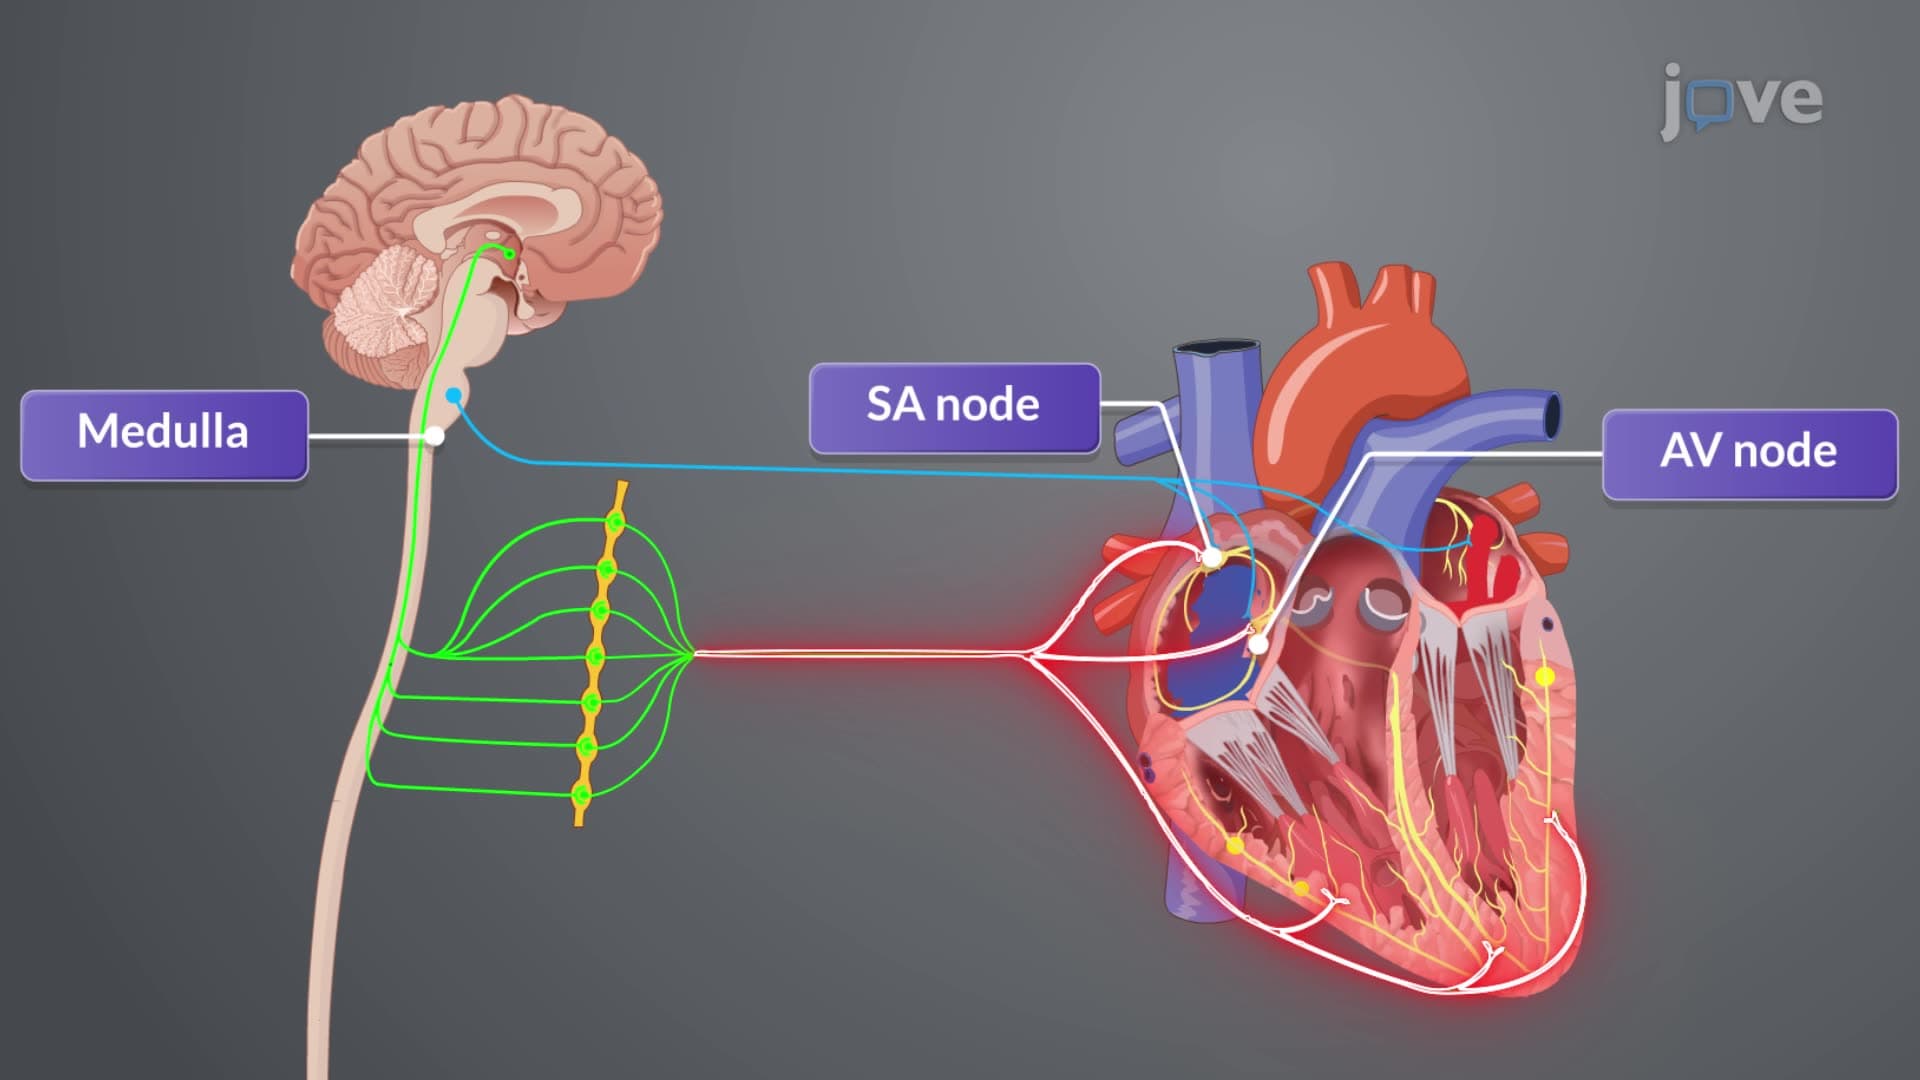
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:17
Measurement of Blood Pressure
 01:29
Pathophysiology of Cardiac Performance
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...